Related Experiment Video
Updated: May 23, 2026
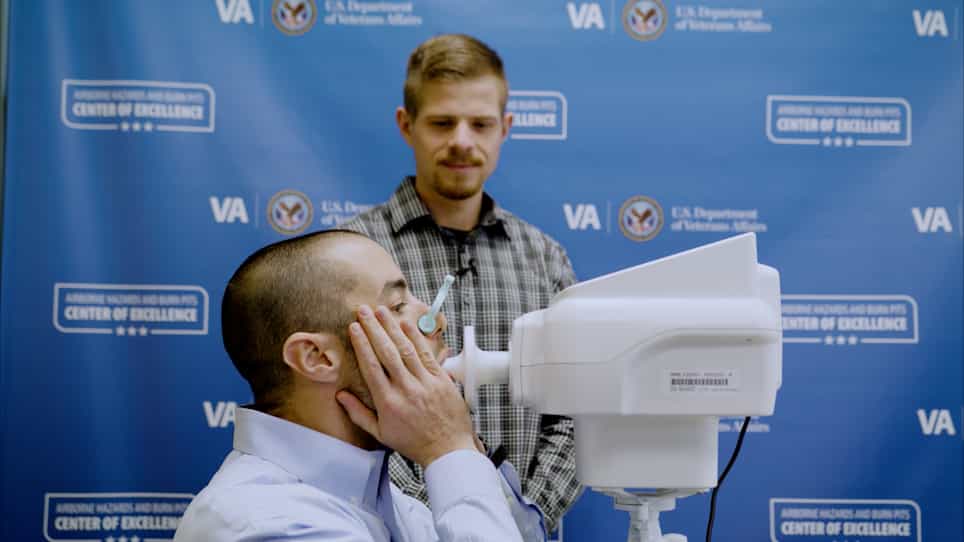
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Relative prolongation of inspiratory time predicts high versus low resistance categorization of hypopneas
Anne M Mooney1, Khader K Abounasr, David M Rapoport
1Division of Pulmonary, Critical Care, and Sleep Medicine, NYU School of Medicine, New York, NY 10016, USA. anne.mooney@nyu.edu

Study Objectives:
Sleep disordered breathing events conceptually separate into "obstructive" and "central" events. Esophageal manometry is the definitive but invasive means of classifying hypopneas. The purpose of this project was to identify noninvasive markers for discriminating high vs. low resistance hypopneas.
Methods:
Forty subjects with obstructive or central sleep apnea underwent diagnostic polysomnography with nasal cannula airflow and esophageal manometry; 200% resistance relative to reference breaths was used to define "high" resistance. Noninvasive parameters from 292 randomly selected hypopneas in 20 subjects were analyzed and correlated to resistance. The best parameter and cutoff for predicting high relative resistance was determined and tested prospectively in 2 test sets in the 20 remaining subjects. Test Set A: 15 randomly selected hypopneas in each subject; Test Set B: all hypopneas in 7 subjects.
Results:
In the development set, prolongation of inspiratory time during the 2 smallest breaths of a hypopnea (T(i)) relative to baseline had the best correlation to high relative resistance. In the Test Set A, relative T(i) > 110% classified obstructive events with sensitivity = 72%, specificity = 77%, PPV = 64%, NPV = 83%. Similar numbers were obtained for classification of hypopneas based on presence of flow limitation (FL) alone. When either relative T(i) or presence of FL were used to define high resistance, sensitivity = 84%, specificity = 74%, PPV = 65%, NPV = 89%. Similar results were obtained for Test Set B.
Conclusions:
Relative prolongation of T(i) is a good noninvasive predictor of high/low resistance in a dataset with both FL and NFL hypopneas. Combination of FL and relative T(i) improves this classification. The use of T(i) to separate obstructive and central hypopneas needs to be further tested for clinical utility (outcomes and treatment effects).
Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:25
Hyperpnea and Hyperventilation