Related Experiment Video
Updated: May 22, 2026
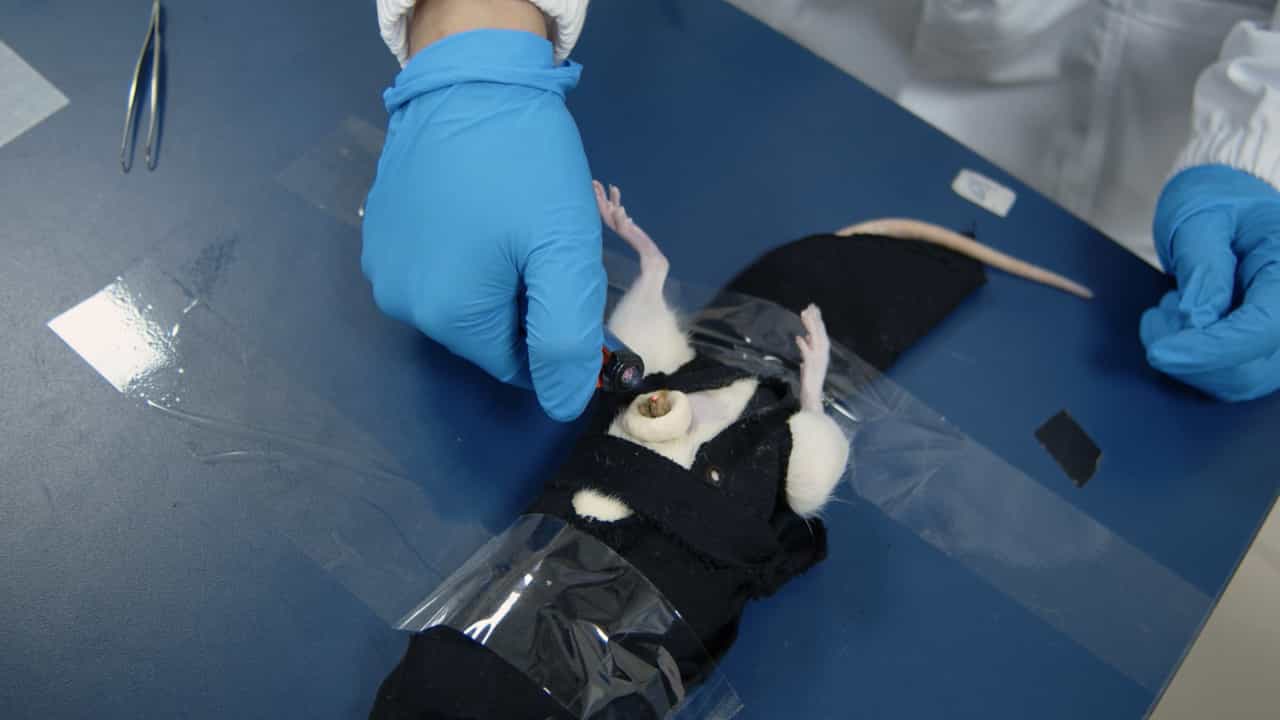

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Premenstrual syndrome (PMS): a peri-menopausal perspective
1University Hospital of North Staffordshire NHS Trust, Staffordshire ST4 6QG, UK. ljb234@doctors.org.uk

PMS (premenstrual syndrome) affects 30-40% of the reproductive female population and hence creates significant impairment amongst women of working age [1]. Having such an economical and financial impact makes it an important disorder to know more about in terms of diagnosis and treatment. In this article, as well as addressing diagnosis and treatments, we focus mainly on peri-menopausal women who are equally (if not more) affected by this disorder and who are subjected to PMS via a host of widely used hormonal treatments. We describe the vicious cycle that exists between exogenous progestogen stimulating PMS-like symptoms and the progestogen that is required for endometrial protection and ways of avoiding this. The treatment should address all concerns of the individual, namely contraceptive requirements, control of PMS and menopausal symptoms. The main theory behind treatment of PMS is to suppress ovulation along the hypothalamo-pituitary-ovarian axis, however neurotransmitters are also implicated in reducing sensitivity to progesterone via receptors, and therefore selective serotonin reuptake inhibitors are also useful. Surgical methods are strongly discouraged and are a last resort. With so many pitfalls, this article aims to tackle the issues commonly encountered with diagnosis and treatment of PMS in the peri-menopause.
PMS (premenstrual syndrome) affects 30-40% of the reproductive female population and hence creates significant impairment amongst women of working age [1]. Having such an economical and financial impact makes it an important disorder to know more about in terms of diagnosis and treatment. In this article, as well as addressing diagnosis and treatments, we focus mainly on peri-menopausal women who are equally (if not more) affected by this disorder and who are subjected to PMS via a host of widely used hormonal treatments. We describe the vicious cycle that exists between exogenous progestogen stimulating PMS-like symptoms and the progestogen that is required for endometrial protection and ways of avoiding this. The treatment should address all concerns of the individual, namely contraceptive requirements, control of PMS and menopausal symptoms. The main theory behind treatment of PMS is to suppress ovulation along the hypothalamo-pituitary-ovarian axis, however neurotransmitters are also implicated in reducing sensitivity to progesterone via receptors, and therefore selective serotonin reuptake inhibitors are also useful. Surgical methods are strongly discouraged and are a last resort. With so many pitfalls, this article aims to tackle the issues commonly encountered with diagnosis and treatment of PMS in the peri-menopause.

Related Concept Videos
 01:24
Disorders of the Female Reproductive System
 01:28
Menopause
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...