Related Experiment Video
Updated: May 22, 2026


The Antihypertensive Effects and Mechanisms of Huotan Jiedu Tongluo Decoction in Rats with H-Type Hypertension
Published on: May 17, 2024
Dietary acid load and risk of hypertension: the Rotterdam Study
Marielle F Engberink1, Stephan J L Bakker, Elizabeth J Brink
1Top Institute Food and Nutrition, Wageningen, Netherlands. marielle.engberink@wur.nl

Background:
Mild metabolic acidosis, which can be caused by diet, may result in elevated blood pressure (BP).
Design:
The analyses included 2241 participants aged ≥55 y who were free of hypertension at baseline (1990-1993) and who had complete dietary and BP data. Dietary data were obtained from a 170-item food-frequency questionnaire. We used 2 measures to characterize dietary acid load: (1) potential renal acid load (PRAL) by using an algorithm including protein, phosphorus, potassium, calcium, and magnesium, and (2) estimated net endogenous acid production (NEAP) based on protein and potassium. HRs for 6-y incidence of hypertension were obtained in tertiles of PRAL and NEAP with adjustment for age, sex, BMI, smoking, education, and intakes of alcohol, fiber, and total energy.
Results:
We identified 1113 incident cases of hypertension during 8707 person-years of follow-up. The median dietary acid load ranged from -14.6 to 19.9 mEq/d across categories of PRAL. Hypertension risk was not significantly associated with dietary acid load. The multivariate HRs (95% CIs) in consecutive tertiles of PRAL were 1.00 (reference), 1.01 (0.87, 1.17), and 1.02 (0.88, 1.18) (P trend = 0.83). The median dietary acid loads were 30.4, 36.7, and 43.7 mEq/d, respectively, in consecutive tertiles of NEAP. Corresponding HRs for NEAP were 1.00 (reference), 0.92 (0.80, 1.07), and 0.94 (0.81, 1.10) (P-trend = 0.46).
Conclusion:
The findings from this prospective cohort study provided no evidence of an association between dietary acid load and risk of hypertension in older adults.

Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Hypertension II: Pathophysiology
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:28
Hypertension I: Introduction
 01:29
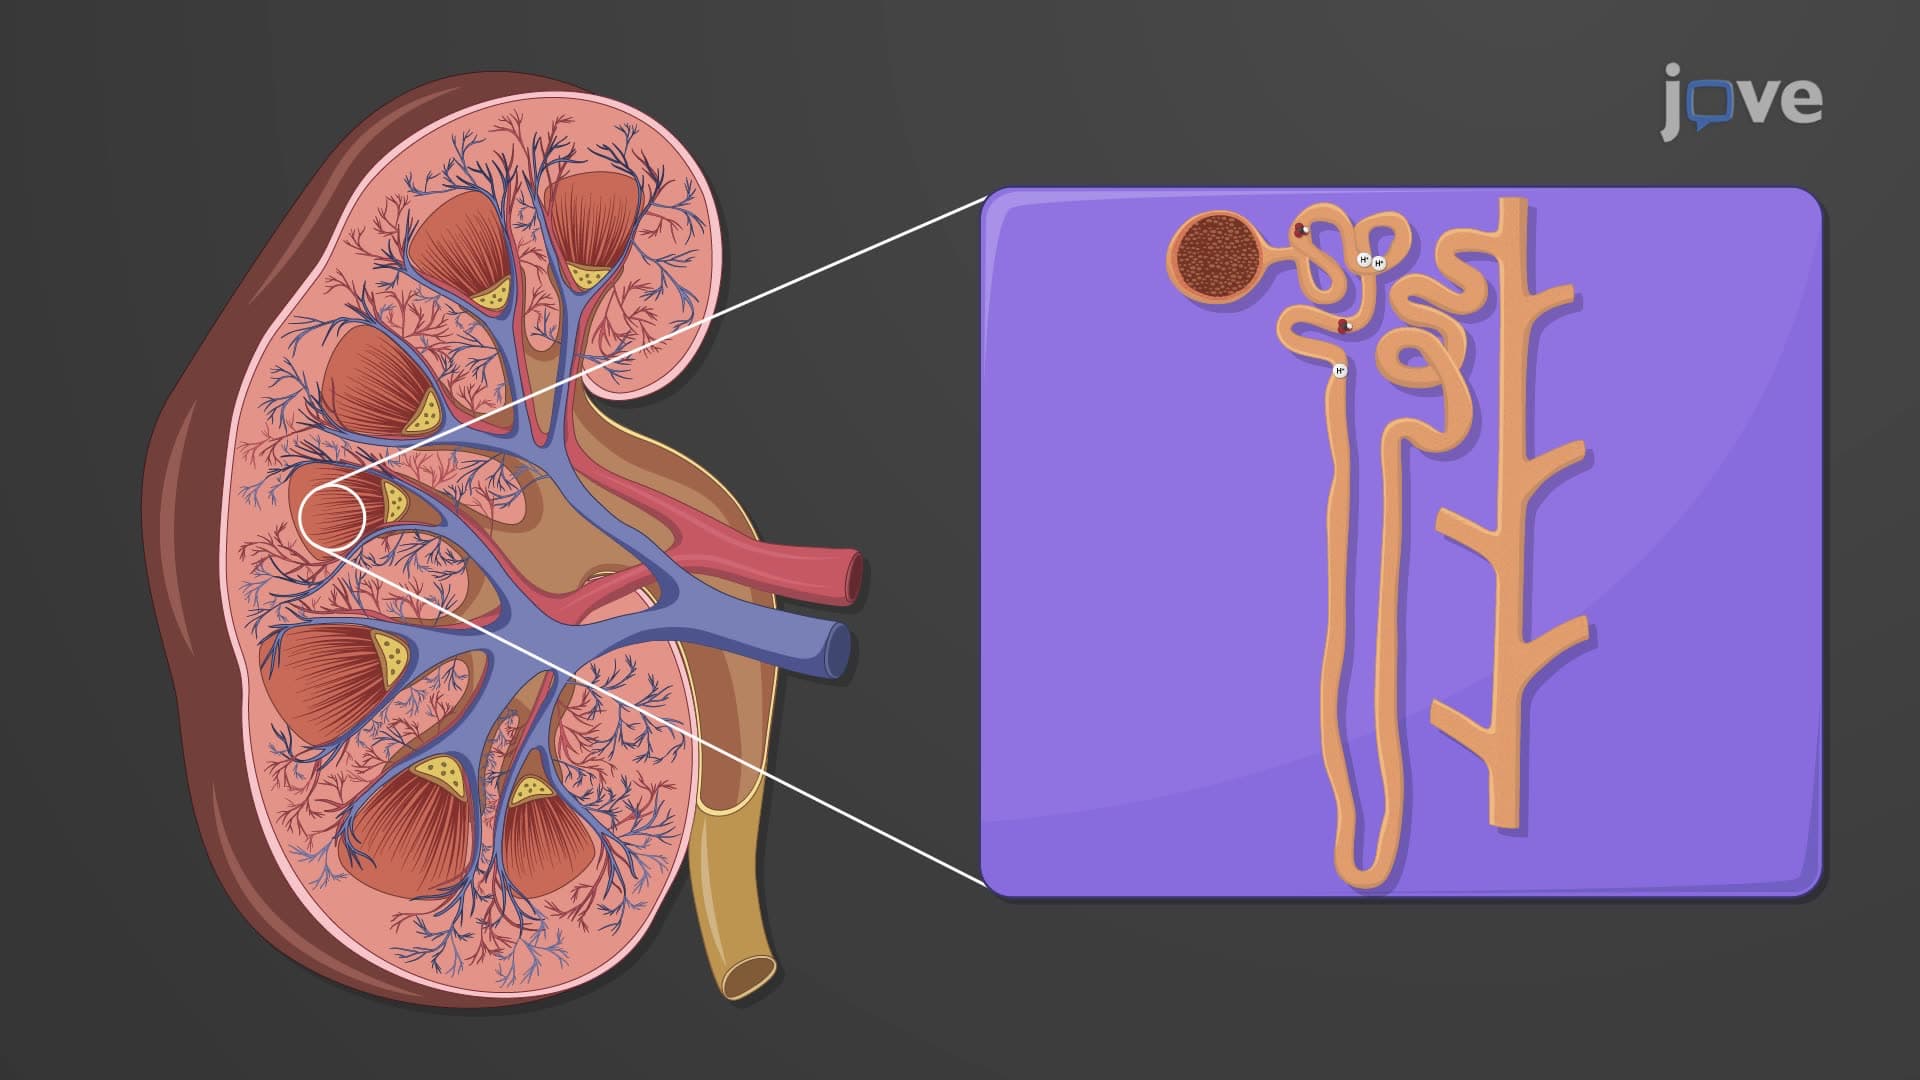
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...