Related Experiment Video
Updated: May 22, 2026


Dissection and Flat-mounting of the Threespine Stickleback Branchial Skeleton
Published on: May 7, 2016
The second branchial cleft fistula
John Maddalozzo1, Jeffrey C Rastatter, Heath F Dreyfuss
1Division of Pediatric Otolaryngology, Children's Memorial Hospital, 2300 Children's Plaza, Chicago, IL 60614, USA. jpmaddalozzo@childrensmemorial.org

Objective:
To review the surgical anatomy and histopathology of second branchial cleft fistulae.
Study Design:
Retrospective study of patients treated for second branchial cleft fistulae at a tertiary care pediatric hospital. The senior author noted anatomic and histologic features of second branchial cleft fistulae, not previously described.
Setting:
Tertiary care children's hospital.
Patients And Methods:
Retrospective examination of 28 patients was conducted who were operated upon for second branchial cleft fistula. Data collected included age at surgery, initial presentation, imaging characteristics prior to surgery, laterality of the fistula tract, pathology results and follow-up data.
Results:
Twenty-eight patients met the criteria for inclusion. Three patients (11%) had bilateral fistulae. 11 (39%) were male and 17 (61%) were female. 23 (74.2%) tracts were lined with ciliated columnar epithelium, 3 (9.7%) had cuboidal epithelium, and 5 (16.7%) had squamous epithelium. Nineteen (61.3%) tracts contained salivary tissue. Of the unilateral fistula tracts, 25 (100%) were on the right side. Of the 3 patients with bilateral lesions, 2 (66%) had associated branchio-oto-renal syndrome (BORS).
Conclusions:
Second branchial cleft fistulae are rare. They are usually right-sided. If bilateral fistulae are present, one should consider an underlying genetic disorder. The histology of the fistulae mostly demonstrates ciliated columnar epithelium with the majority of specimens showing salivary tissue. There is a clear association with the internal jugular vein (IJV). Dissection should continue until superior to the hyoid bone, ensuring near complete surgical dissection and less risk of recurrence.

Related Concept Videos
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:12
Arteries of the Upper Limbs
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:17
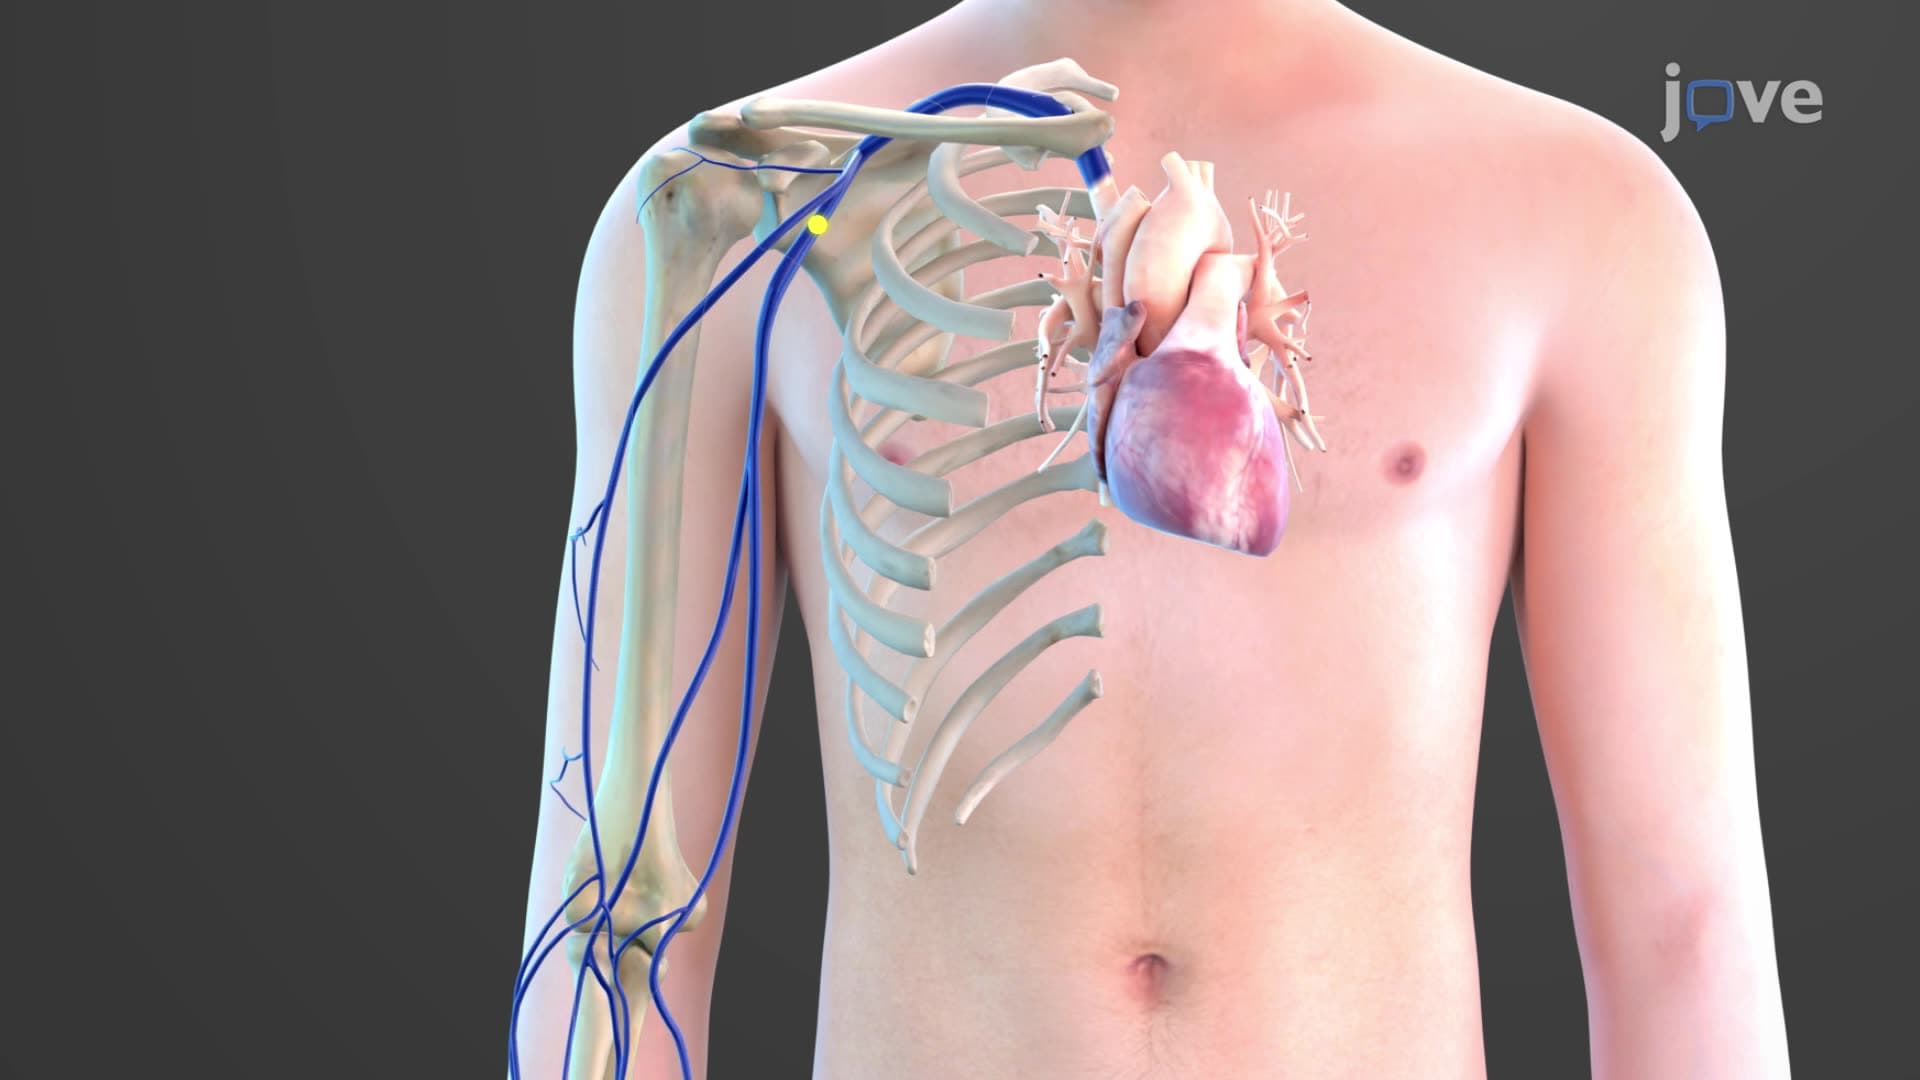
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...