Related Experiment Video
Updated: May 22, 2026

High-Resolution Three-Dimensional Imaging of the Footpad Vasculature in a Murine Hindlimb Gangrene Model
Published on: March 16, 2022
Femoral neuropathy and meralgia paresthetica secondary to an iliacus hematoma
Tae Im Yi1, Tae Hee Yoon, Joo Sup Kim
1Department of Rehabilitation Medicine, Daejin Medical Center Bundang Jesaeng General Hospital, Seongnam 463-774, Korea.

Abstract:
Compressive femoral and lateral femoral cutaneous neuropathies from an iliacus hematoma are unusual presentation. We report a case of a 16-year-old boy who developed right femoral and lateral femoral cutaneous neuropathies as a complication of traumatic ipsilateral iliacus hematoma formation. The patient complained of numbness in the right thigh and calf as well as right leg weakness, and pain in the right inguinal area. Nerve conduction study and needle electromyography identified the neuropathies. After the electrodiagnostic studies, the pelvic bone MRI revealed a large, 9×5×4.5 cm right iliacus hematoma. As a result, diagnosis of a right iliacus hematoma compressing the femoral and lateral femoral cutaneous nerves was made, and the patient underwent an operation to remove the hematoma. Symptoms and neurological signs showed notable improvement after surgical decompression. Subsequent follow-up electrodiagnostic studies after 11 weeks demonstrated regeneration evidence.
More Related Videos
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:20
Arteries of Lower Limbs
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:21
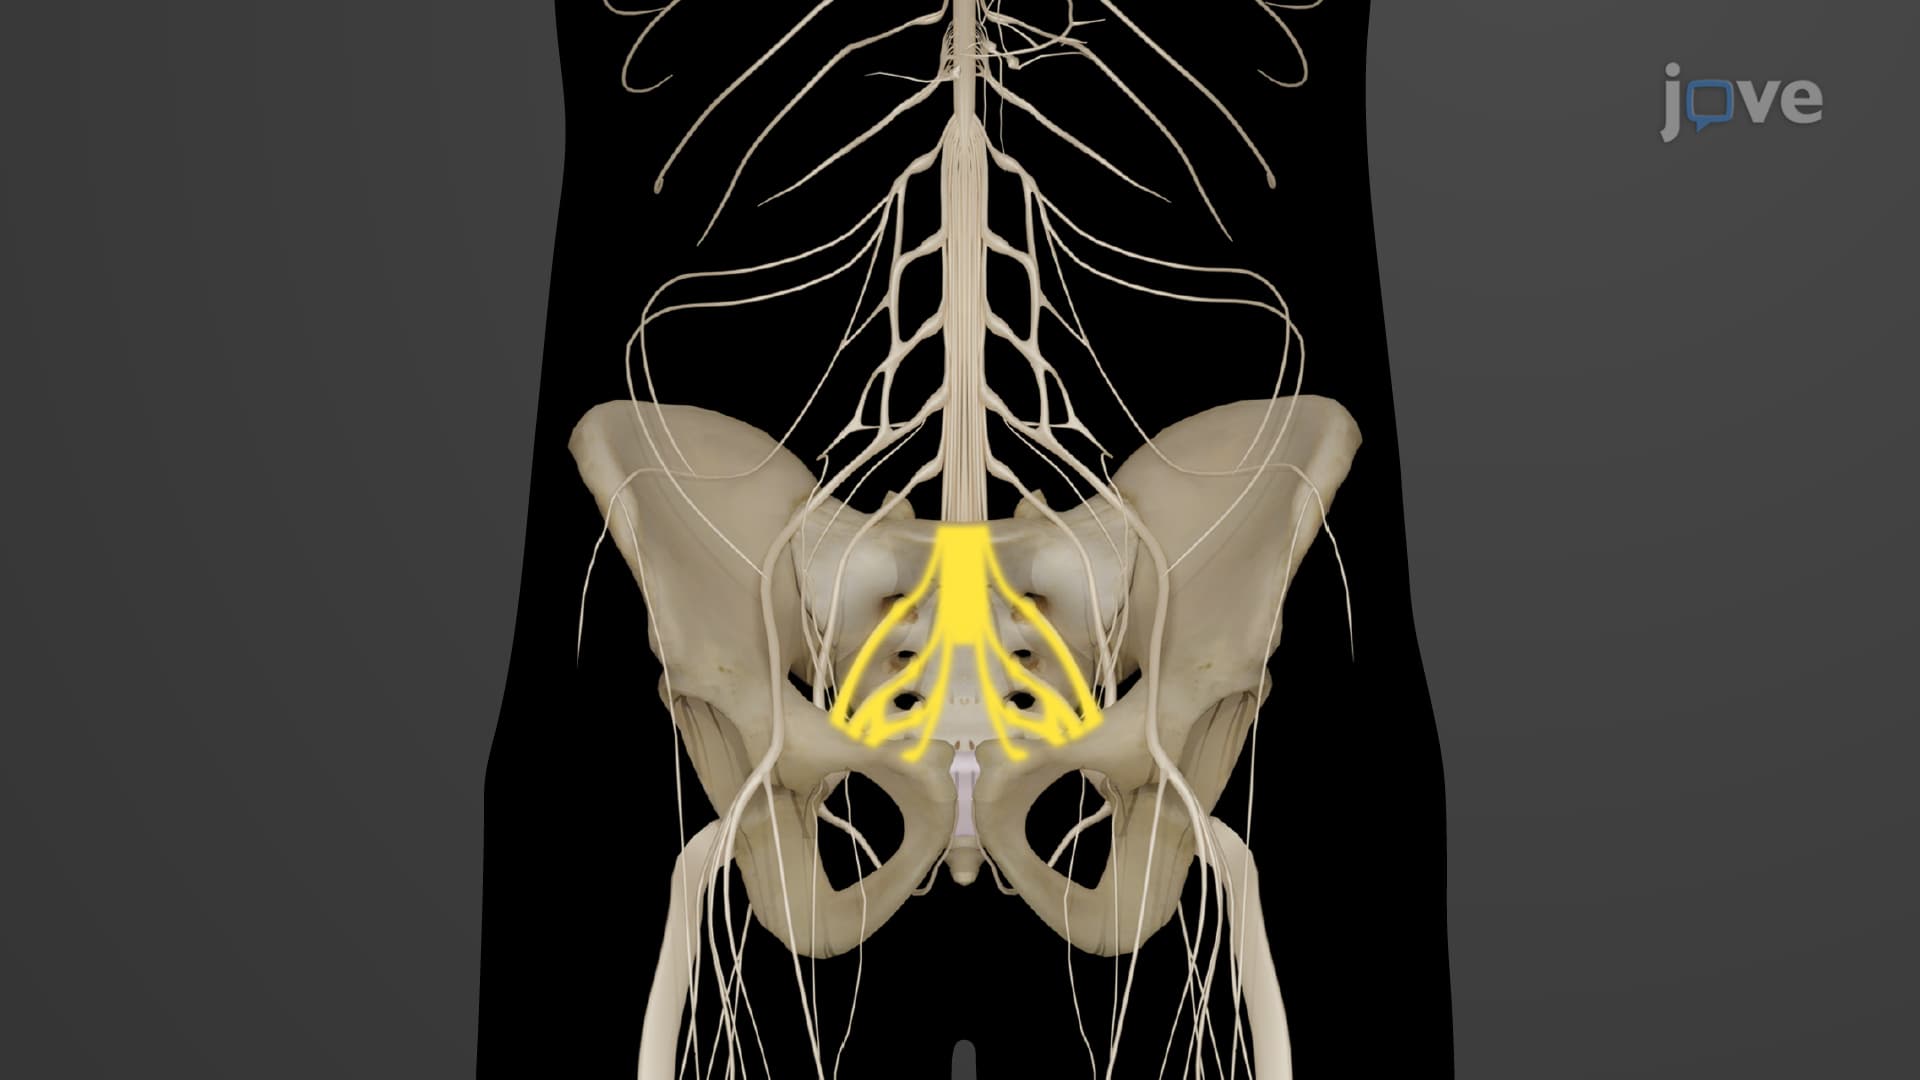
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:15
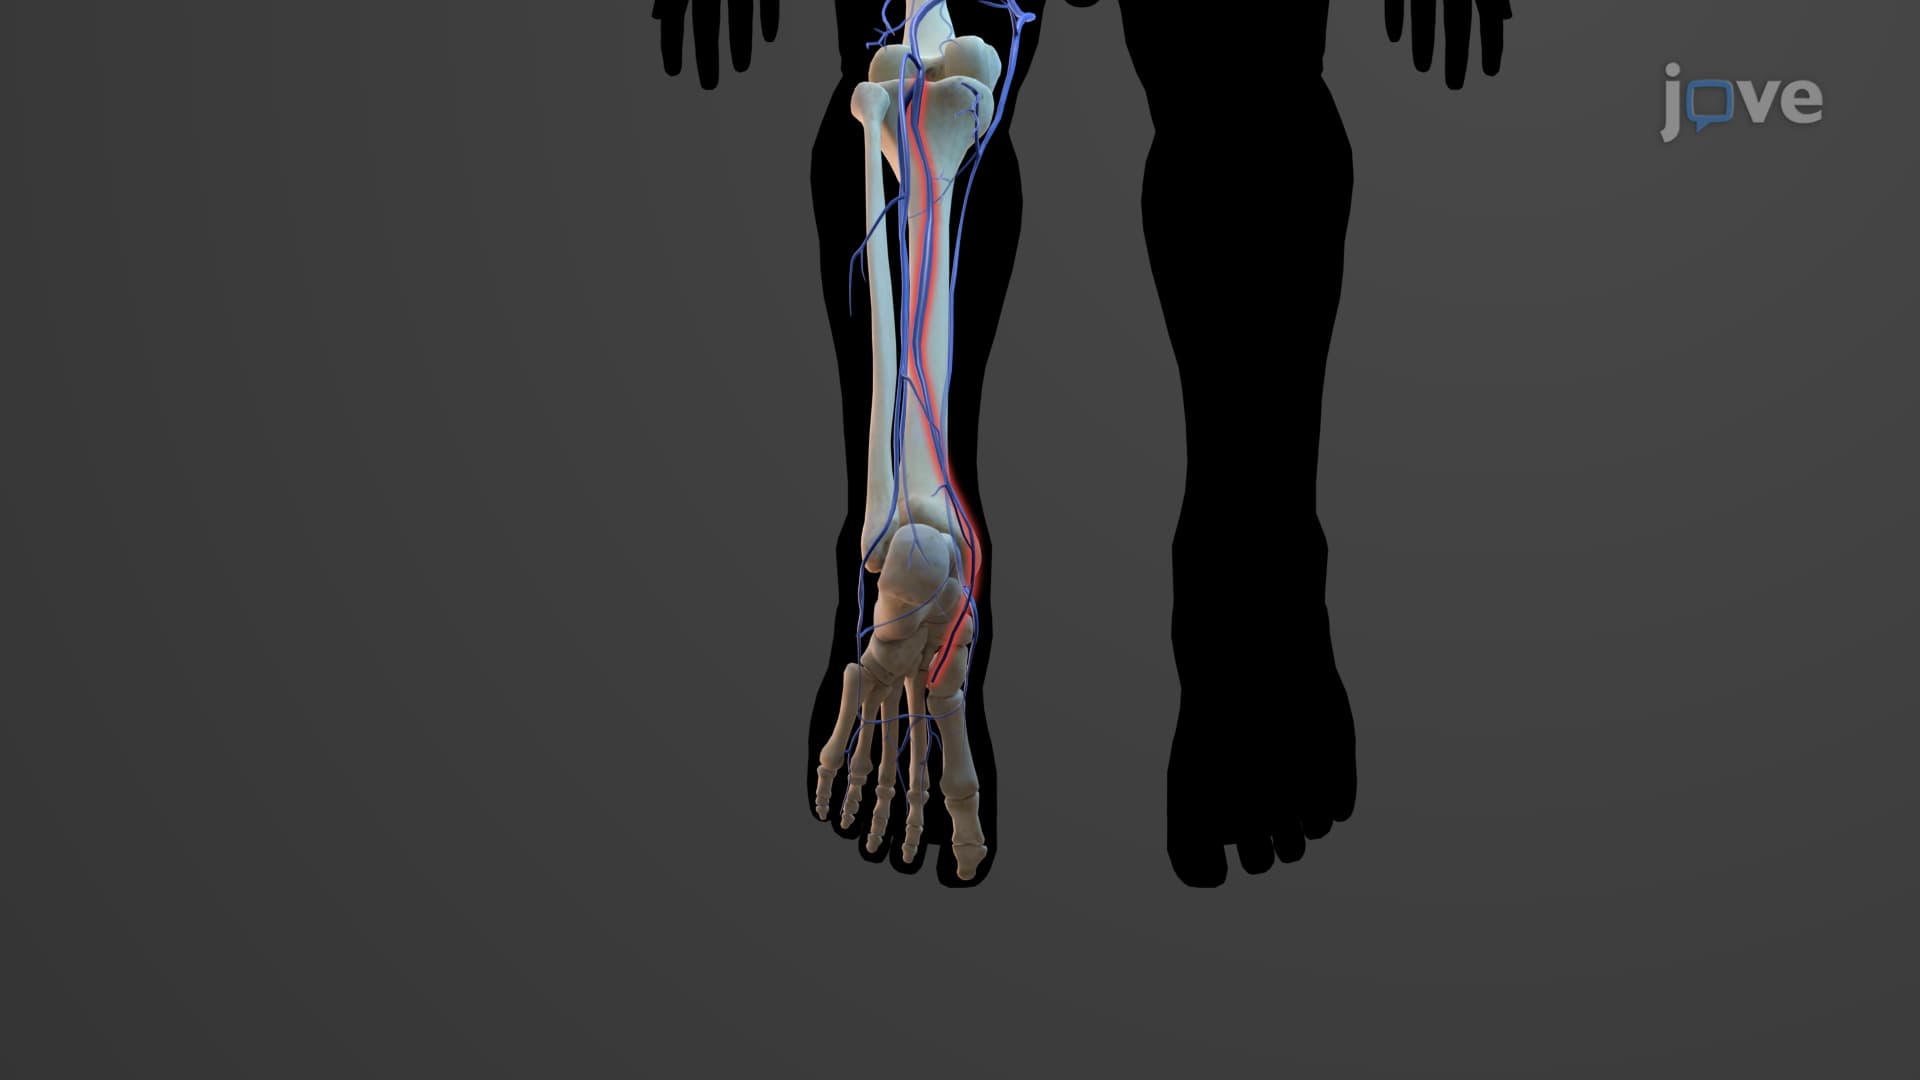
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...