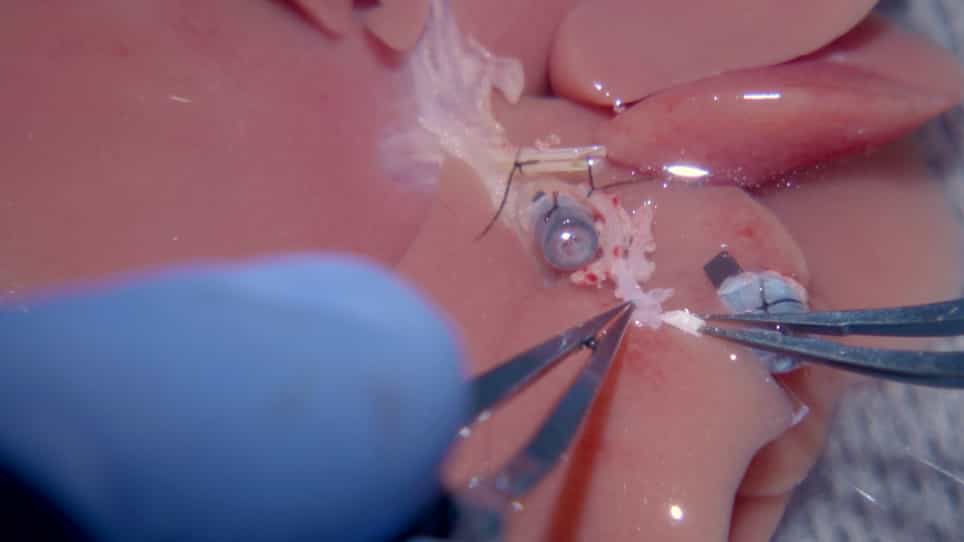
Related Experiment Video
Updated: May 21, 2026


New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Vascular complications in pediatric liver transplantation; single-center experience from Singapore
1Department of Paediatric Surgery, National University Hospital, Singapore.

Insights
Vascular complications after pediatric liver transplantation decreased with surgical innovations, particularly for portal vein reconstructions. Improved techniques and monitoring significantly reduced these risks in young patients.
Area of Science:
- Pediatric Surgery
- Transplantation Medicine
- Vascular Surgery
Background:
- Vascular complications (VC) are a significant cause of morbidity and mortality in pediatric liver transplantation (LT).
- Portal vein (PV) complications are a major concern in LT for small recipients.
Purpose of the Study:
- To analyze the evolution of vascular reconstructions in pediatric LT.
- To assess the impact of these changes on the incidence of VC, especially PV complications.
Main Methods:
- Retrospective review of 81 pediatric LT cases (1991-2010).
- Analysis of VC in portal vein (PV), hepatic artery (HA), and hepatic veins (HV).
- Comparison of two cohorts: initial 40 LT (group 1) and subsequent 41 LT (group 2), with group 2 featuring surgical innovations and routine Doppler ultrasound.
Main Results:
- Overall VC incidence was 19.7% (HA thrombosis 4.9%, PV thrombosis 12.3%).
- VC incidence decreased from 27.5% in group 1 to 12.1% in group 2 (p=0.08).
- PV complications significantly decreased from 17.5% to 7.3% (P=0.1) in group 2.
Conclusions:
- Pediatric LT vascular reconstructions present technical challenges and a learning curve.
- Surgical innovations, meticulous techniques, and postoperative monitoring reduce VC incidence.
- Improvements in PV reconstruction and monitoring are key to reducing complications in pediatric LT.
Aim:
Vascular complications (VC) are a major cause of significant morbidity and mortality in pediatric liver transplantation (LT). We reviewed our series to study the evolution of vascular reconstructions and its effect on the incidence of VC after LT, particularly with regard to the portal vein (PV).
Methods:
The medical records of 81 pediatric LT performed in 76 children (38 boys) from 1991 to 2010 in the National University Hospital, Singapore, were reviewed to identify VC pertaining to PV, hepatic artery (HA), and hepatic veins (HV) and to analyse the data for the entire series and in 2 consecutive cohorts: initial 40 LT (group 1) and subsequent 41 LT (group 2). Specific interventions in group 2 were characterized by surgical innovations for reconstruction of the difficult PV and routine use of Doppler ultrasound intraoperatively and postoperatively.
Results:
The overall incidence of VC was 19.7% (n = 16) and individually HA thrombosis 4.9% (n = 4), HA stenosis 1.2% (n = 1), PV thrombosis 12.3% (n = 9), PV stenosis 1.2% (n = 1), and HV thrombosis 1.2% (n = 1). The overall 1- and 5-year survival rates in our series were 89% and 85%, respectively. The 1- and 5-year survival rates in patients with and without VC were 81.25% and 68.75% and 90.8% and 89.2%, respectively. The incidence of VC decreased from 27.5% in group 1 to 12.1% in group 2 (p = .08). The major contribution to this appears to be a decrease in PV complications from 17.5% in group 1 to 7.3% in group 2 (P = .1). The incidence of HA (3 vs 2) and HV (1 vs 0) complications was similar between the 2 groups.
Conclusions:
Vascular reconstructions in small recipients are technically challenging and associated with a learning curve. Application of meticulous techniques in general, surgical innovations to the difficult PV in particular and attention to postoperative monitoring contribute toward a major reduction in VC.