Related Experiment Video
Updated: May 21, 2026

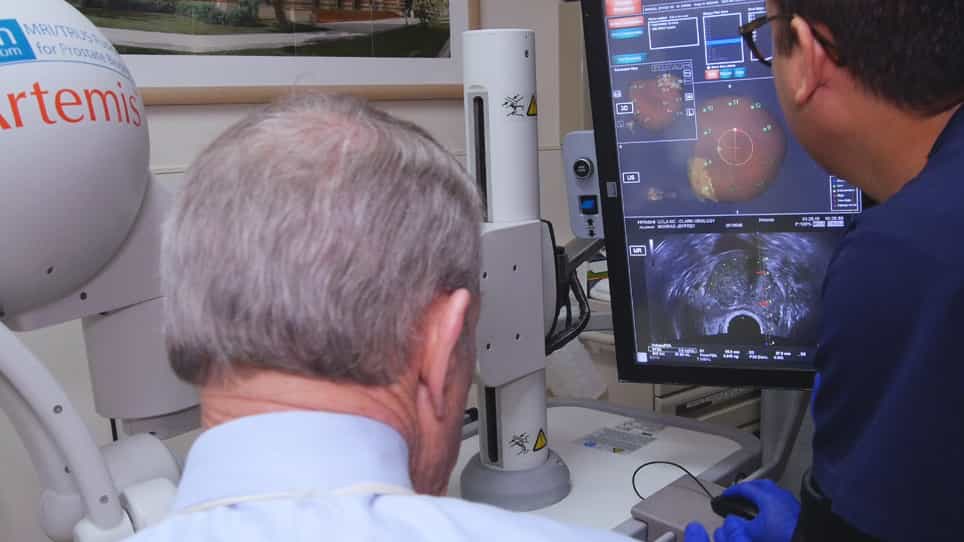
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Endorectal magnetic resonance imaging for predicting pathologic T3 disease in Gleason score 7 prostate cancer:
Thomas J Pugh1, Steven J Frank, Mary Achim
1Department of Radiation Oncology, The University of Texas MD Anderson Cancer Center, Houston, TX 77030, USA. tpugh@mdanderson.org

Purpose:
To determine the ability of endorectal magnetic resonance imaging (erMRI) and other pretreatment factors to predict the presence and extent of extraprostatic extension (EPE) in men with Gleason score (GS) 7 prostate cancer.
Methods And Materials:
We included patients with clinical stage T1c-T2c, GS=7 (3+4 or 4+3), and prostate-specific antigen (PSA) <10ng/mL who underwent pre-prostatectomy erMRI. We compared pathologic EPE findings with pretreatment factors.
Results:
One hundred seventy-one men were eligible for inclusion. Pretreatment characteristics were: median age=60 years (42-76); median PSA 4.9ng/mL (0.4-9.9); GS 3+4=61%; T1c=51%; T2a=25%; T2b=21%; T2c=3%; ≥50% positive cores=46%; EPE-positive (EPE+) erMRI=28%. Thirty-three percent had pathologic EPE. Increasing T-stage (p<0.0001) and EPE+ erMRI (p<0.0001) were significant predictors of pathologic EPE, whereas GS (4+3 vs. 3+4) (p=0.14), percentage of positive core biopsies (p=0.15), and pretreatment PSA (p=0.41) were not. Median EPE distance was 1.75mm (range, <1-15mm). The rates of EPE >5mm and EPE >3mm were 11% and 15%, respectively. The odds ratios for erMRI detection of any EPE and of EPE >5mm were 3.06 and 3.75, respectively.
Conclusions:
T-stage and EPE+ erMRI predict pathologic EPE in men with GS 7 prostate cancer. The ability of erMRI to detect EPE increases with increasing EPE distance. These findings may be useful in patient selection for prostate brachytherapy monotherapy.