Related Experiment Video
Updated: May 21, 2026


Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Staple line coverage with a polyglycolic acid sheet plus pleural abrasion by thoracoscopic surgery for primary
Shuji Haraguchi1, Kiyoshi Koizumi, Iwao Mikami
1Department of Biological Regulation and Regenerative Surgery, Graduate School of Medicine, Nippon Medical School, Bunkyo-ku, Tokyo, Japan. shuji@nms.ac.jp

Insights
This study shows that covering staple lines with a polyglycolic acid sheet and using pleural abrasion during thoracoscopic surgery effectively prevents recurrence of primary spontaneous pneumothorax in young patients.
Area of Science:
- Thoracic Surgery
- Pulmonary Medicine
Background:
- Primary spontaneous pneumothorax (PSP) often affects young individuals.
- Recurrence of PSP necessitates effective preventative surgical strategies.
Purpose of the Study:
- To evaluate the efficacy of staple line coverage with polyglycolic acid sheets plus pleural abrasion in thoracoscopic surgery for PSP.
- To assess short-term outcomes and long-term recurrence rates.
Main Methods:
- 47 patients (<40 years) underwent thoracoscopic bullectomy with stapling and pleural abrasion.
- Staple lines were covered with a 10x10 cm polyglycolic acid sheet; no fibrin glue was used.
- Outcomes included operative morbidity and postoperative pneumothorax recurrence.
Main Results:
- No operative mortality or significant morbidity (air leak, hemorrhage) was observed.
- Pneumothorax recurred in 3 cases (6.4%), with 2 requiring no intervention due to adhesions.
- The 4-year recurrence-free survival rate was 94%.
Conclusions:
- Polyglycolic acid sheet coverage combined with pleural abrasion is a safe and effective method.
- This technique significantly reduces the risk of postoperative pneumothorax recurrence.
- It represents a useful approach for managing primary spontaneous pneumothorax in young patients.
Purpose:
We investigated surgical results of staple line coverage with a polyglycolic acid sheet plus pleural abrasion by thoracoscopic surgery for treating primary spontaneous pneumothorax in young patients.
Methods:
Forty-seven patients younger than 40 years underwent 48 thoracoscopic surgical procedures for spontaneous pneumothorax at the Division of Thoracic Surgery, Department of Surgery, Nippon Medical School, from May 2007 through August 2010. All patients underwent thoracoscopic bullectomy with stapling devices and pleural abrasion performed with a gauze sponge held by forceps until the pleura became petechial. Finally, the staple line was covered with a polyglycolic acid sheet (10 × 10 cm). No fibrin glue was used. We investigated both short-time results after surgery and the postoperative recurrence of pneumothorax.
Results:
There was no operative mortality or morbidity, such as air leakage from staple lines or hemorrhage due to pleural abrasion. Pneumothorax recurred after surgery in 3 cases. In 2 cases, neither re-operation nor tube thoracostomy was necessary because intrapleural adhesions allowed only partial collapse of the lung. One patient underwent re-operation for an overlooked bulla facing the diaphragm in left lower lobe of the lung 2 days after the first operation. The rate of freedom from pneumothorax 4 years after surgery was 94%.
Conclusions:
Staple line coverage with a polyglycolic acid sheet plus pleural abrasion by thoracoscopic surgery is a useful method for preventing morbidity and the postoperative recurrence of pneumothorax.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
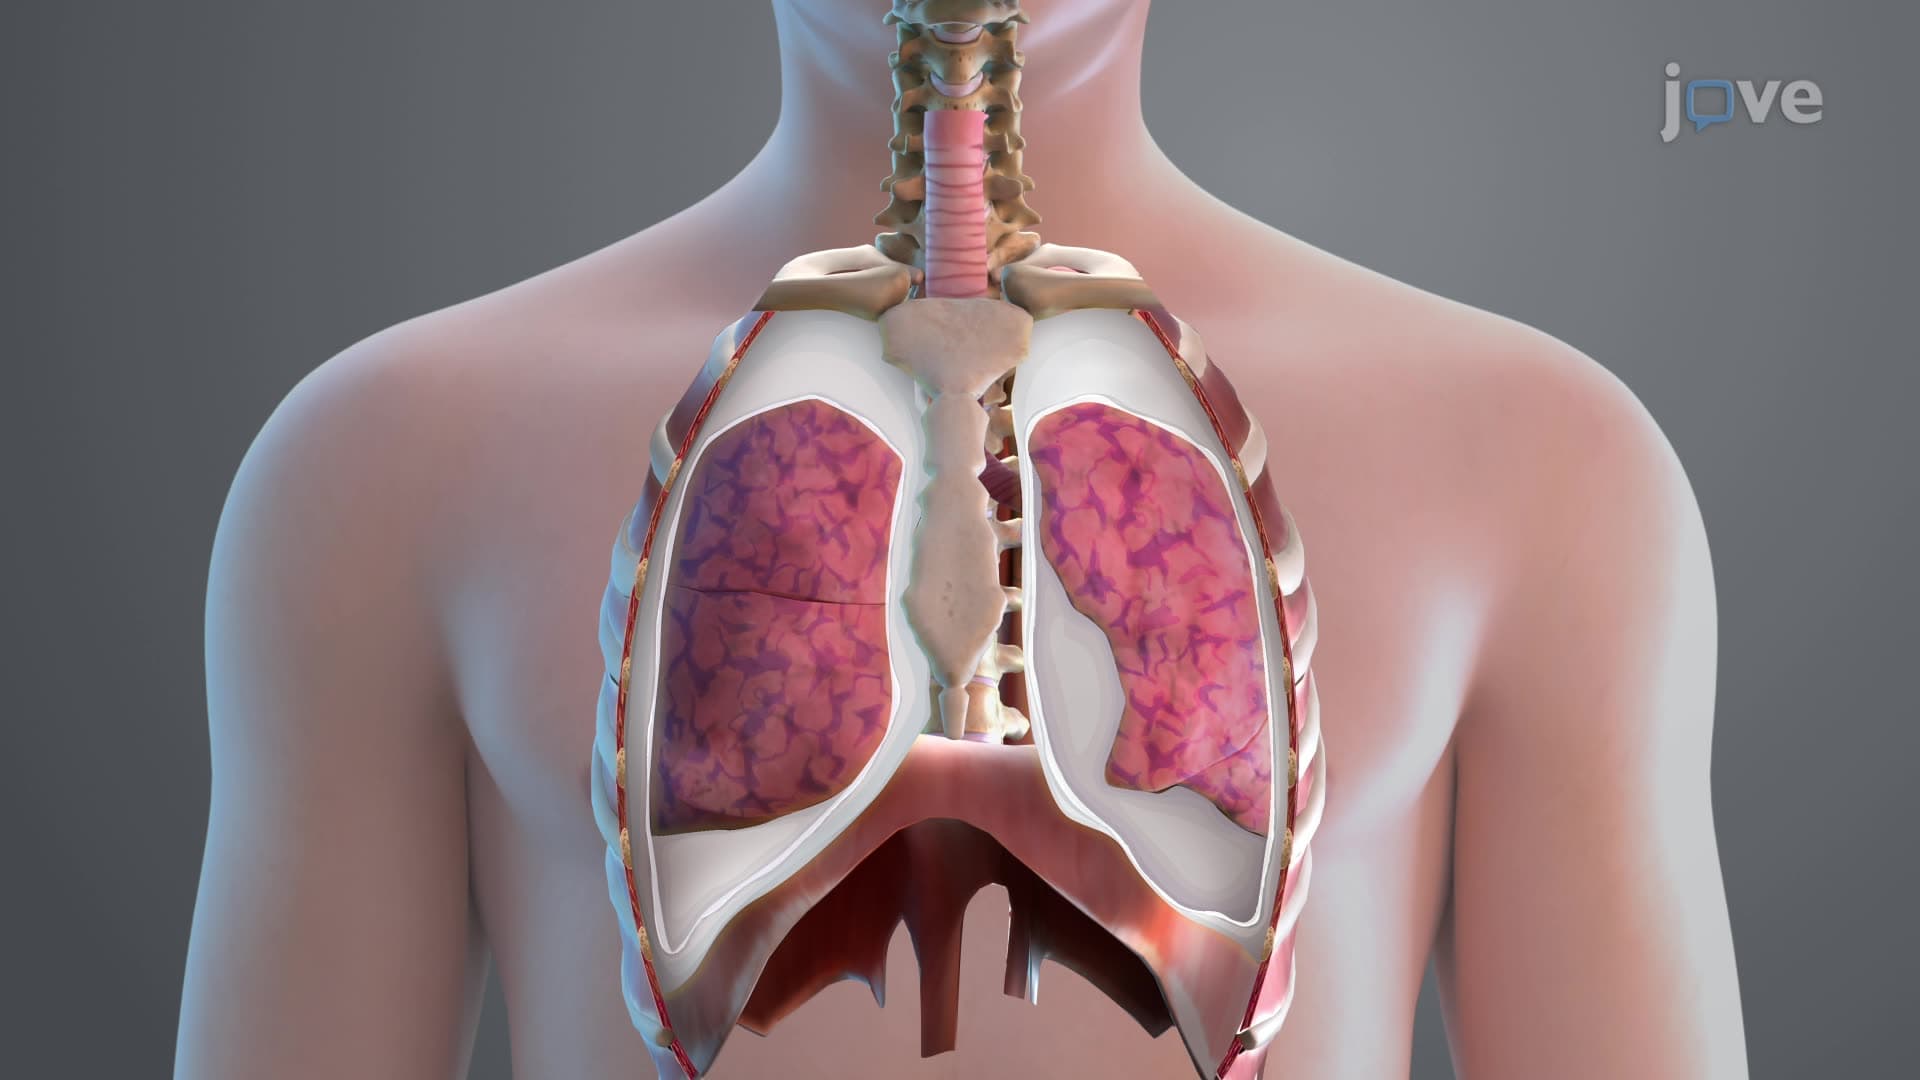
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:13
Pleura of the Lungs
 01:08
Pneumothorax II: Pathophysiology
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...