Related Experiment Video
Updated: May 19, 2026


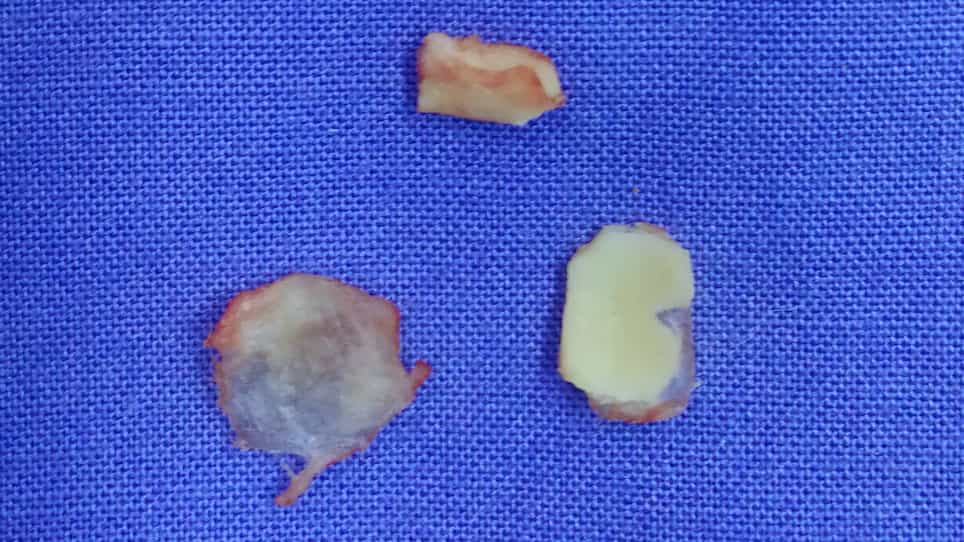
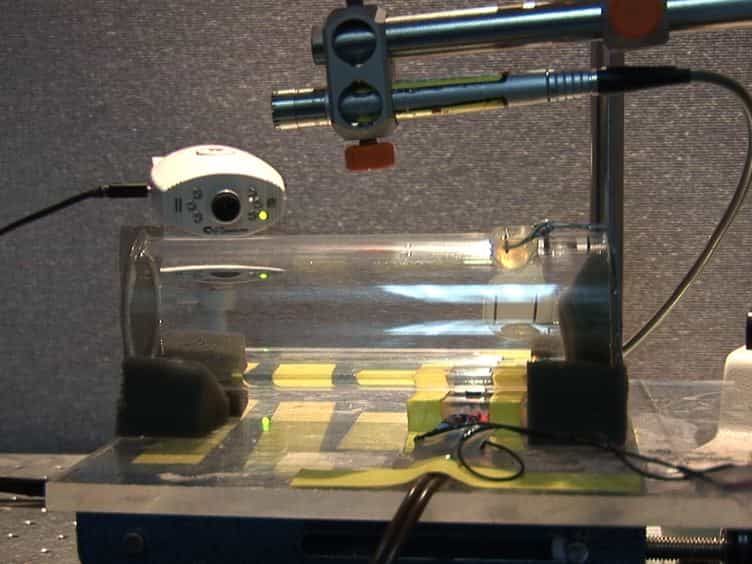
Simple Surgical Induction of Conductive Hearing Loss with Verification Using Otoscope Visualization and Behavioral Clap Startle Response in Rat
Published on: October 26, 2019
Traumatic tympanic membrane perforations: clinical and audiometric findings in 198 patients
John Martin Hempel1, Alexander Becker, Joachim Müller
1Department of Otorhinolaryngology, Head and Neck Surgery, Ludwig Maximilian University, Munich, Germany.

Objective:
To obtain clinical and audiometric findings in traumatic tympanic membrane perforations from a typical patient collective in a Western industrial nation because the appropriate data have an important relevance in medicolegal questions.
Study Design:
Retrospective data collection.
Setting:
Germany's largest university clinic for otorhinolaryngology, head and neck surgery.
Subject And Methods:
From the medical records of 198 patients with traumatic tympanic membrane perforations, the following data were collected: demographic data, date and mechanism of the trauma, otoscopic findings and collateral injuries, kind of therapy and its results, pure tone audiometry, and statement of tinnitus or vertigo in the course.
Results:
Most patients were young (mean age, 29.2 yr) and male (62%). Men and women are equally represented in perforations resulting from a physical blow to the ear (44.7% vs 46.7%); a collision was more often the cause in men (23.6% vs 14.7%), whereas an accidental perforation by insertion of a cotton bud was approximately 2 times more common on women (13.8% vs 25.3%). The left ear was more often affected than the right ear (58.5% vs 41.5%). Collateral damage was found in only 1% of the cases. In blows, collisions, barotraumas, and the insertion of sharp objects, the inferior parts of the tympanic membrane were most often affected; the most severe (subtotal) perforations were caused by explosions, weld beads, and insertion of cotton buds. For therapy, myringoplasty had an overall success rate of 88.9%; splinting with silicon foils, 51.6%; and "no therapy," 53.3%. Bone conduction thresholds for the affected ear were higher in low, middle, and high frequencies compared with the contralateral ear by trend, but a statistical difference was only found in the high frequencies. In follow-up examinations, the hearing thresholds in the high frequencies were no longer significantly different. A "c dip" or "fis dip" was found in 18.0% and 9.2%. Tinnitus and vertigo were reported in 30.8 and 8.1%, respectively, but only in 2.0% and 0% during follow-up.
Conclusion:
High-frequency hearing loss, tinnitus, and vertigo in traumatic tympanic membrane perforations have a good prognosis.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:14
Assessing Body Temperature - Tympanic membrane
Step 1: Begin by practicing good hand hygiene to prevent the transmission of microorganisms.
Step 2: Turn on the thermometer and wait until the ready sign appears on the screen to ensure accurate measurement.
Step 3: Slide the probe cover in place to prevent cross-contamination.
Step 4: Instruct the patient to tilt their head to the side for comfort and check for cerumen...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:21
Perceiving Loudness, Pitch, and Location
Place theory, or place coding, suggests that different pitches are heard because various sound waves activate specific locations along the cochlea's basilar membrane. The brain determines the pitch of a sound by identifying...