Related Experiment Video
Updated: May 19, 2026
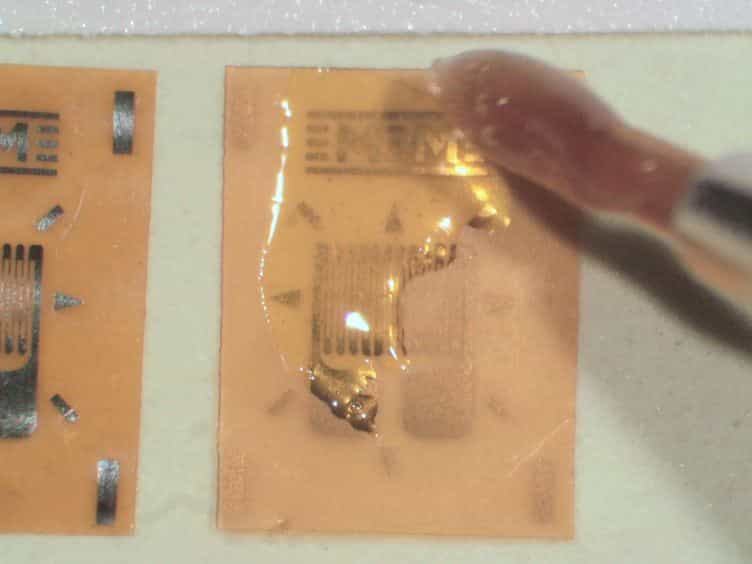

Fabrication and Implantation of Miniature Dual-element Strain Gages for Measuring In Vivo Gastrointestinal Contractions in Rodents.
Published on: September 18, 2014
Upper gastrointestinal dysmotility after spinal cord injury: is diminished vagal sensory processing one culprit?
1Neural and Behavioral Sciences, Penn State University College of Medicine Hershey, PA, USA.

Abstract:
Despite the widely recognized prevalence of gastric, colonic, and anorectal dysfunction after spinal cord injury (SCI), significant knowledge gaps persist regarding the mechanisms leading to post-SCI gastrointestinal (GI) impairments. Briefly, the regulation of GI function is governed by a mix of parasympathetic, sympathetic, and enteric neurocircuitry. Unlike the intestines, the stomach is dominated by parasympathetic (vagal) control whereby gastric sensory information is transmitted via the afferent vagus nerve to neurons of the nucleus tractus solitarius (NTS). The NTS integrates this sensory information with signals from throughout the central nervous system. Glutamatergic and GABAergic NTS neurons project to other nuclei, including the preganglionic parasympathetic neurons of the dorsal motor nucleus of the vagus (DMV). Finally, axons from the DMV project to gastric myenteric neurons, again, through the efferent vagus nerve. SCI interrupts descending input to the lumbosacral spinal cord neurons that modulate colonic motility and evacuation reflexes. In contrast, vagal neurocircuitry remains anatomically intact after injury. This review presents evidence that unlike the post-SCI loss of supraspinal control which leads to colonic and anorectal dysfunction, gastric dysmotility occurs as an indirect or secondary pathology following SCI. Specifically, emerging data points toward diminished sensitivity of vagal afferents to GI neuroactive peptides, neurotransmitters and, possibly, macronutrients. The neurophysiological properties of rat vagal afferent neurons are highly plastic and can be altered by injury or energy balance. A reduction of vagal afferent signaling to NTS neurons may ultimately bias NTS output toward unregulated GABAergic transmission onto gastric-projecting DMV neurons. The resulting gastroinhibitory signal may be one mechanism leading to upper GI dysmotility following SCI.

Related Concept Videos
 01:20
Gastrointestinal Motility Disorders
 01:37
Neural Regulation
 01:27
Esophageal Achalasia
 01:22
Pathophysiology of Vomiting
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:11
Enteric Nervous System: Regulation of GI Motor Activity
During periods of fasting, the ENS initiates the migrating myoelectric complex, a program...