
Surgical treatment of epilepsy associated with cortical dysplasia: 2012 update
Jason S Hauptman1, Gary W Mathern
1Department of Neurosurgery, Mattel Children's Hospital, David Geffen School of Medicine, University of California, Los Angeles, California, USA.

Insights
Cortical dysplasia, a common cause of epilepsy, presents challenges in diagnosis and treatment. Complete surgical resection offers the best seizure control, but identifying subtle cases and developing new therapies remain key future goals.
Area of Science:
- Neurology
- Neurosurgery
- Epileptology
Background:
- Cortical dysplasia is a leading cause of epilepsy in children and a significant factor in adult epilepsy surgery.
- The International League Against Epilepsy (ILAE) classifies cortical dysplasia into types I, II, and III, with distinct clinical and pathological features.
- Type II lesions are associated with earlier onset and more severe epilepsy than type I.
Purpose of the Study:
- To review the classification, diagnostic challenges, and surgical outcomes of cortical dysplasia in epilepsy.
- To highlight the effectiveness of surgical resection and identify areas for future research.
Main Methods:
- Review of current literature on cortical dysplasia classification and diagnosis.
- Analysis of presurgical evaluation techniques including EEG, MRI, and PET.
- Evaluation of surgical outcomes and factors influencing seizure freedom.
Main Results:
- Presurgical evaluation methods like EEG and MRI have limitations in accuracy for cortical dysplasia.
- FDG-PET offers higher accuracy but is not universally sensitive.
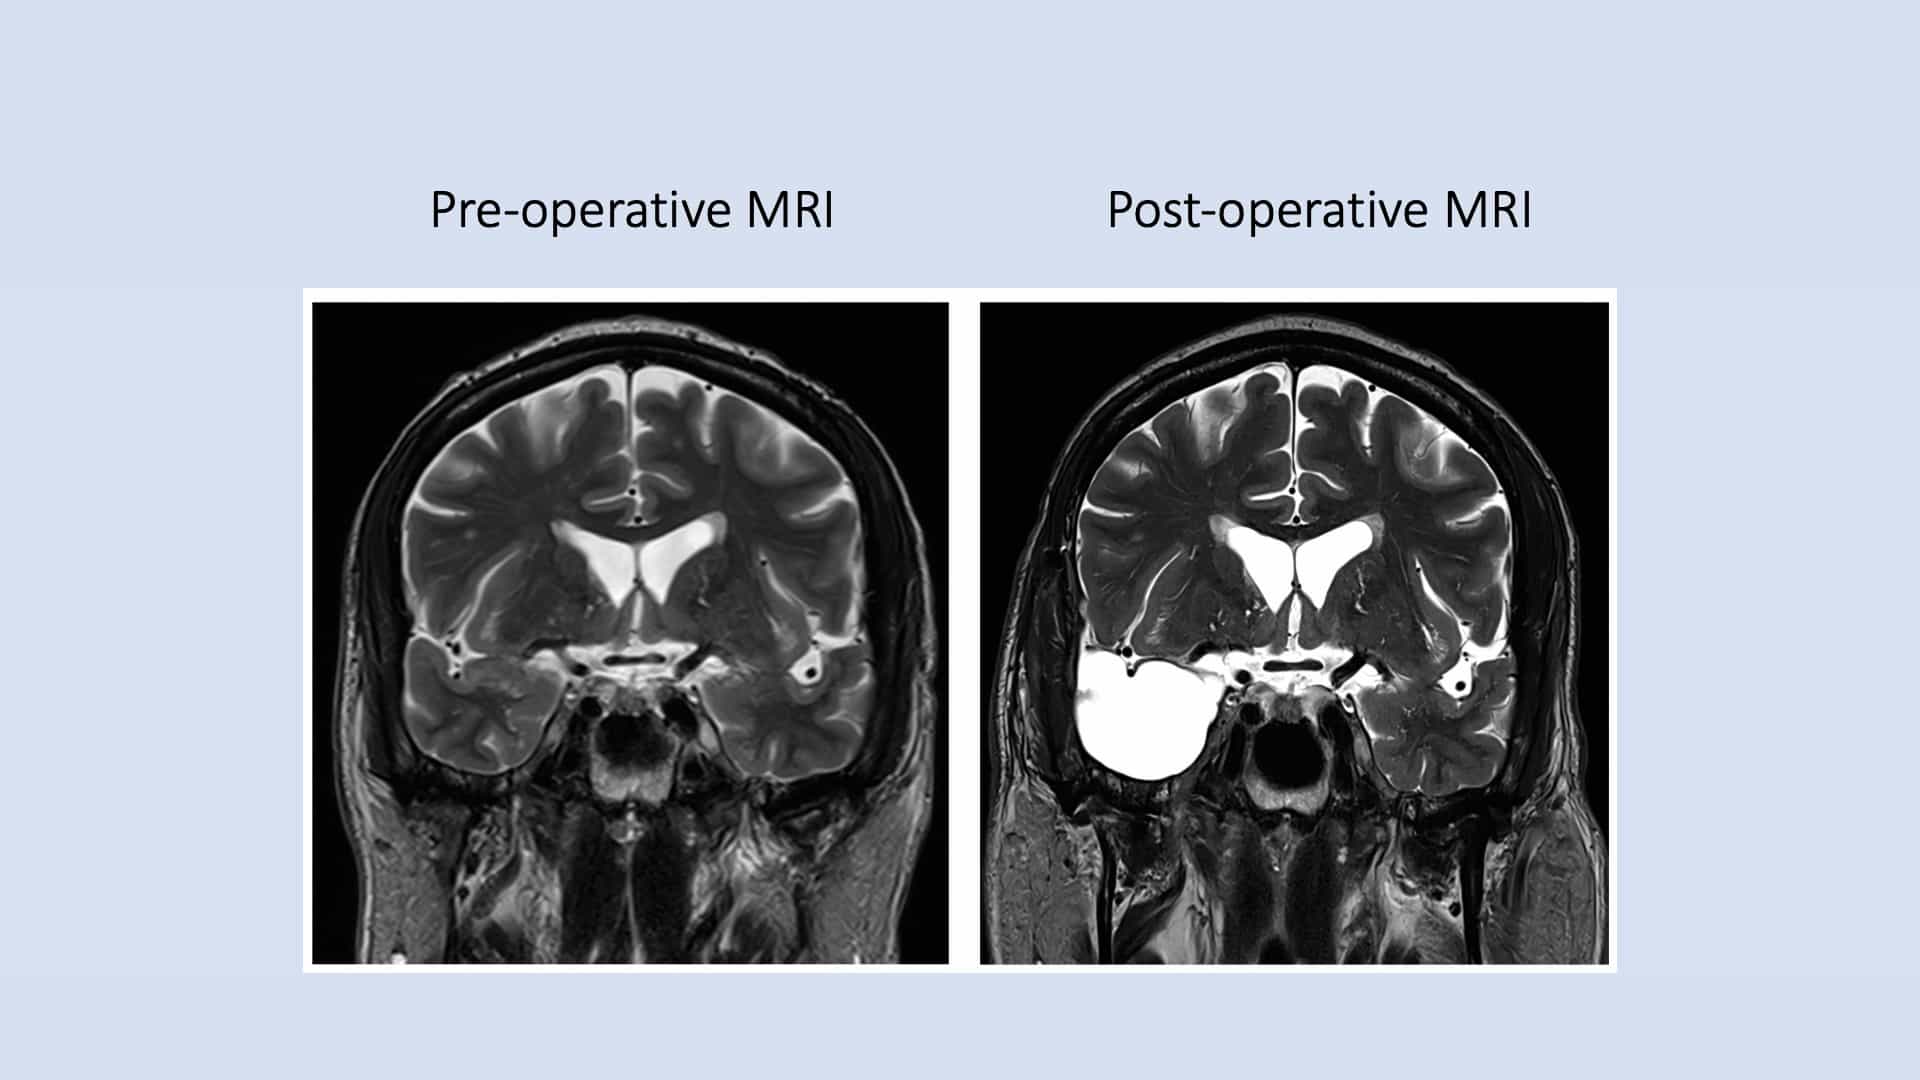
- Complete surgical resection achieves seizure freedom in 80% of cases, significantly higher than incomplete resections (20%).
Conclusions:
- Cortical dysplasia management requires accurate diagnosis and tailored surgical approaches.
- Complete resection is crucial for optimal seizure control in epilepsy surgery for cortical dysplasia.
- Further research is needed for subtle dysplasia detection and novel adjunctive treatments.
Abstract:
Cortical dysplasia is the most common etiology in children and the third most frequent finding in adults undergoing epilepsy neurosurgery. The new International League Against Epilepsy (ILAE) classification grades isolated cortical dysplasia into mild type I (cortical dyslamination), severe type II (dyslamination plus dysmorphic neurons and balloon cells), and dysplasia associated with other epileptogenic lesions (type III). Multilobar type II lesions present at an earlier age and with more severe epilepsy compared with focal type I abnormalities, often in the temporal lobe, and these findings are reflected in types and age of operations for cortical dysplasia. Presurgical evaluation of patients with epilepsy from cortical dysplasia can be challenging. Interictal and ictal scalp electroencephalography (EEG) accurately localizes cortical dysplasia with 50-66% accuracy. Structural magnetic resonance imaging (MRI) is negative in roughly 30% of cases, most often linked with mild type I cases. FDG-PET can be 80-90% accurate, but is not 100% sensitive. Chronic intracranial electrodes are used in about 50% of cases with cortical dysplasia, but often do not capture restricted ictal-onset zones. About 60% of patients with cortical dysplasia are seizure free after epilepsy neurosurgery, with much higher rates of becoming seizure free with complete (80%) compared with incomplete (20%) resections. The most common reason for incomplete resection is the risk of an unacceptable neurologic deficit. Future challenges include better tools in identifying subtle forms of type I cortical dysplasia, and development of adjunctive treatments from basic research for those undergoing incomplete resections.

Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:30
Electroconvulsive Therapy
 01:22
Epilepsy ll: Types
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...
 01:20
Seizures l: Introduction