Subaortic right ventricular characteristics and relationship to exercise capacity in congenitally corrected transposition of the great arteries
Related Experiment Video
Updated: May 18, 2026
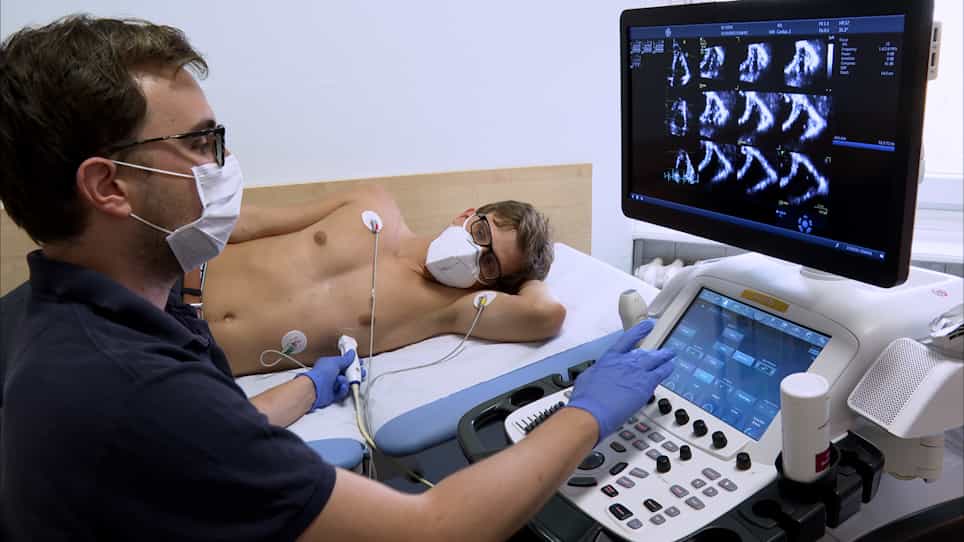
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Jasmine Grewal1, Andrew Crean, Patrick Garceau
1Division of Cardiology, University of British Columbia Pacific Adult Congenital Heart Disease Clinic, St. Paul's Hospital, Vancouver, British Columbia, Canada. grewaljasmine@hotmail.com

Insights
Congenitally corrected transposition of the great arteries (cc-TGA) often leads to systemic right ventricular (RV) dilation and dysfunction, impacting exercise capacity. Tricuspid regurgitation significantly contributes to these issues in cc-TGA patients.
Area of Science:
- Cardiology
- Congenital Heart Disease
- Cardiac Imaging
Background:
- Congenitally corrected transposition of the great arteries (cc-TGA) involves the right ventricle (RV) acting as the systemic ventricle.
- Progressive RV deterioration is a known complication in cc-TGA.
- Understanding factors contributing to RV dysfunction is crucial for patient management.
Purpose of the Study:
- To characterize the systemic RV in adults with cc-TGA.
- To identify factors associated with RV dilation and dysfunction.
- To explore the relationship between RV function and exercise capacity.
Main Methods:
- Prospective study of adult cc-TGA patients.
- Cardiopulmonary stress testing for exercise capacity assessment.
- Cardiac MRI for ventricular volume and fibrosis; Velocity Vector Imaging for strain echocardiography.
Main Results:
- Reduced exercise capacity in cc-TGA patients compared to controls (20.9 vs 30.8 mL/kg/min).
- Majority (61%) had RV ejection fraction ≤ 40%.
- Significant differences in RV diastolic volumes and strain parameters observed, linked to tricuspid regurgitation severity.
Conclusions:
- Systemic RV dilation, dysfunction, and exercise intolerance are common in cc-TGA.
- Significant tricuspid regurgitation is a major contributor to RV problems.
- Abnormal RV myocardial deformation suggests failure to adapt to systemic pressure; afterload-reducing therapies warrant investigation.
Background:
In congenitally corrected transposition of the great arteries (cc-TGA), the morphologic right ventricle acts as the subaortic (systemic) ventricle, and deterioration of the ventricle over time is a well-known complication. The objective of this study was to characterize the right ventricle and explore factors that may be contributing to ventricular dilation and dysfunction and the relationship with exercise capacity.
Methods:
This was a prospective study of adults with cc-TGA. All patients underwent cardiopulmonary stress testing, ventricular volume and fibrosis assessment by cardiac magnetic resonance imaging, and Velocity Vector Imaging strain echocardiography.
Results:
Twenty-six patients were included (mean age, 38 ± 16 years; 54% women). Exercise capacity was significantly reduced in patients with cc-TGA compared with normal subjects (20.9 ± 6.0 vs 30.8 ± 9.2 mL/kg/min, P = .001). The majority of patients (61%) had right ventricular (RV) ejection fractions ≤ 40%. There was no evidence of fibrosis on cardiac magnetic resonance imaging. There was a significant difference in diastolic volumes among those with RV ejection fractions > 40% versus ≤ 40% (173 ± 29mL vs 233 ± 65 mL, P = .02) and moderate or severe versus no or mild tricuspid regurgitation (240 ± 80mL vs 190 ± 38mL, P = .04). RV apical longitudinal and mid free wall circumferential strain was decreased compared with these values in controls.
Conclusions:
In this relatively "well" cc-TGA population, subaortic RV dilation, dysfunction, and exercise intolerance are a common problem. Significant systemic tricuspid atrioventricular valvular regurgitation is an important contributor to the problem. In this study, subaortic RV myocardial deformation parameters were found to be abnormal, suggesting that there is a failure of the ventricle to adapt to systemic pressures, and therapies to reduce afterload should be explored. Recurrent ischemia resulting in fibrosis likely does not contribute to RV dilation or dysfunction as demonstrated by the magnetic resonance imaging findings in this study.
More Related Videos

Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Mitral Stenosis I: Introduction
 01:15
Aortic Regurgitation I: Introduction