Related Experiment Video
Updated: May 18, 2026

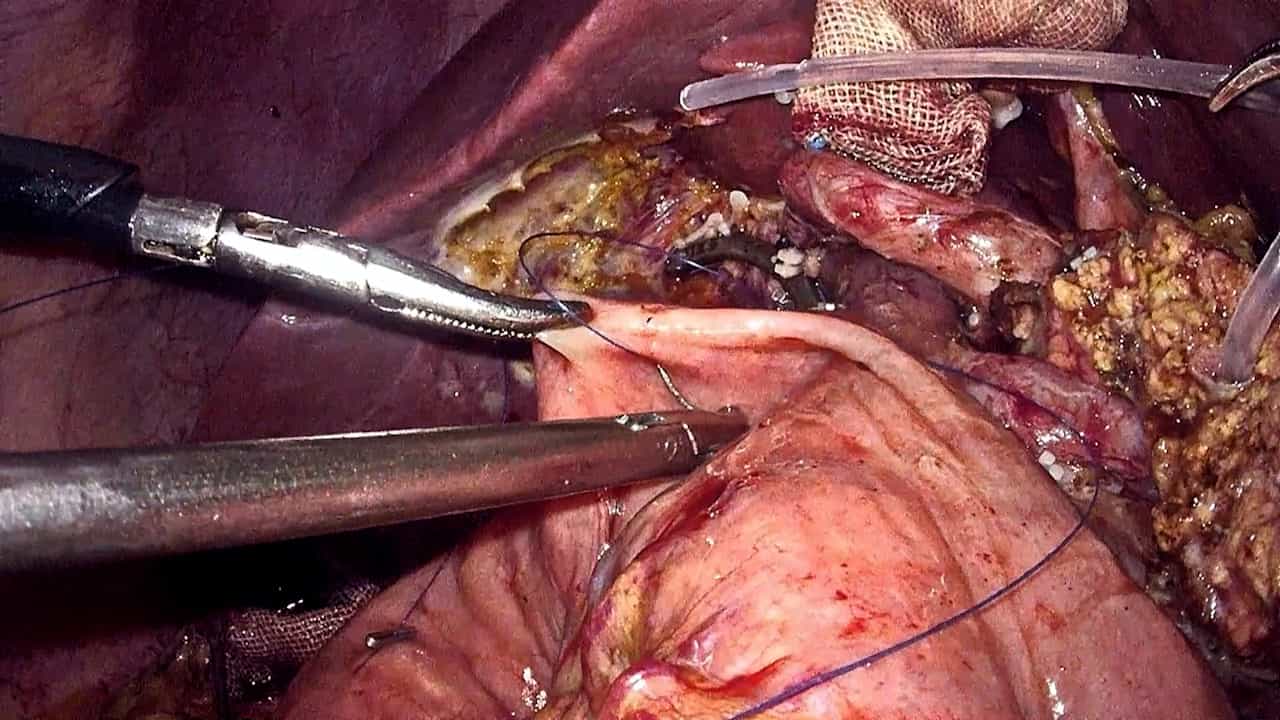
Retroperitoneal Laparoscopic Debridement and Drainage for Pancreatic Abscess
Published on: March 15, 2024
Bilateral pleural fluid caused by a pancreaticopleural fistula requiring surgical treatment
Shiro Sonoda1, Miki Taniguchi, Tomohide Sato
1Internal Medicine, Nakano General Hospital, Japan.

Abstract:
A 53-year-old man developed bilateral pleural effusion with respiratory failure. The amylase level in the pleural effusion was elevated. He had neither abdominal symptoms nor abdominal physical findings. Abdominal computed tomography (CT) also showed no abnormalities. Magnetic resonance cholangiopancreatography (MRCP) was non-diagnostic, but endoscopic retrograde cholangiopancreatography (ERCP) and subsequent CT showed a fistula connecting the pancreatic duct with the right pleural cavity. The pleural effusion was refractory to drug therapy, leading to the need for surgical intervention. The pathological findings revealed chronic pancreatitis without pseudocysts. The elevated pancreatic amylase in the pleural effusion offered an important clue to the correct diagnosis.
Related Concept Videos
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Pleural Disorders: Types and Brief Description
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...