Related Experiment Video
Updated: May 17, 2026


Electrophysiological Methods to Assess Peripheral Pain Block in an Anesthetized Rat
Published on: November 21, 2025
Prolonged nerve blockade delays the onset of neuropathic pain
Sahadev A Shankarappa1, Jonathan H Tsui, Kristine N Kim
1Laboratory for Biomaterials and Drug Delivery, Department of Anesthesiology, Division of Critical Care Medicine, Boston Children's Hospital, Harvard Medical School, Boston, MA 02115, USA.

Abstract:
Aberrant neuronal activity in injured peripheral nerves is believed to be an important factor in the development of neuropathic pain. Pharmacological blockade of that activity has been shown to mitigate the onset of associated molecular events in the nervous system. However, results in preventing onset of pain behaviors by providing prolonged nerve blockade have been mixed. Furthermore, the experimental techniques used to date to provide that blockade were limited in clinical potential in that they would require surgical implantation. To address these issues, we have used liposomes (SDLs) containing saxitoxin (STX), a site 1 sodium channel blocker, and the glucocorticoid agonist dexamethasone to provide nerve blocks lasting ~1 wk from a single injection. This formulation is easily injected percutaneously. Animals undergoing spared nerve injury (SNI) developed mechanical allodynia in 1 wk; nerve blockade with a single dose of SDLs (duration of block 6.9 ± 1.2 d) delayed the onset of allodynia by 2 d. Treatment with three sequential SDL injections resulting in a nerve block duration of 18.1 ± 3.4 d delayed the onset of allodynia by 1 mo. This very prolonged blockade decreased activation of astrocytes in the lumbar dorsal horn of the spinal cord due to SNI. Changes in expression of injury-related genes due to SNI in the dorsal root ganglia were not affected by SDLs. These findings suggest that formulations of this kind, which could be easy to apply clinically, can mitigate the development of neuropathic pain.

Related Concept Videos
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:44
Nociception
 01:17
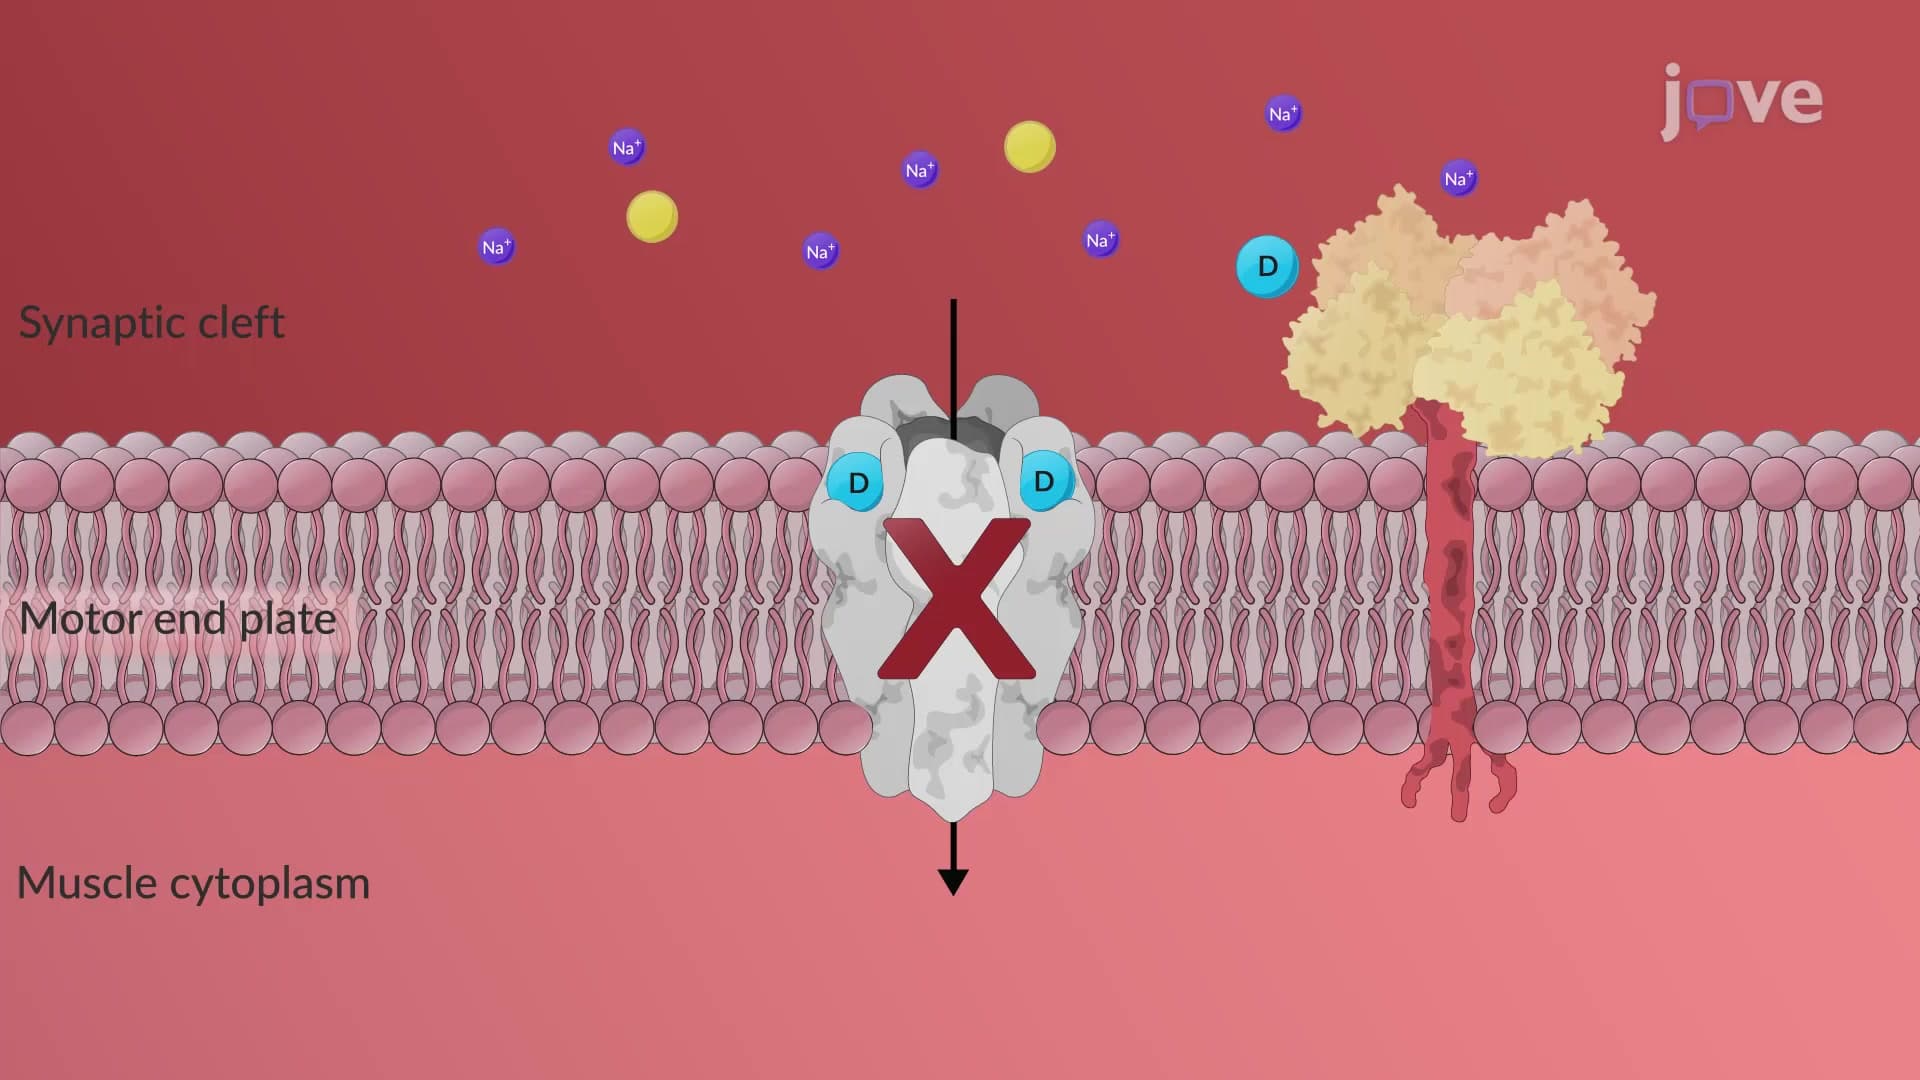
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:25
Analgesia and Pain Management