Related Experiment Video
Updated: May 17, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
A multimodal approach to acute biliary pancreatitis during pregnancy: a case series
Andreas Polydorou1, Konstantinos Karapanos, Antonios Vezakis
1University of Athens, Aretaieion Hospital, Athens, Greece.

The treatment of acute biliary pancreatitis during pregnancy remains controversial. We present our experience of treating 7 pregnant women with acute biliary pancreatitis and verified or suspected choledocholithiasis, by using magnetic resonance cholangiopancreatography (MRCP), endoscopic retrograde cholangiopancreatography (ERCP), and sphincterotomy followed by laparoscopic cholecystectomy. MRCP was performed in all patients to confirm the presence of common bile duct stones, their size and number. ERCP and sphincterotomy were performed without the use of radiation. The procedure was terminated only when all stones (the number clarified at MRCP), were retrieved into the duodenum. All patients underwent laparoscopic cholecystectomy the following day. Neither post-ERCP nor postoperative major complications were noted. All but one patient reached a healthy natural-term labor. One patient had a planned cesarean section on 35th week. The combination of MRCP, nonradiation ERCP, and immediate laparoscopic cholecystectomy provides definite treatment and seems to put both mother and fetus at lower risk than presumed.
The treatment of acute biliary pancreatitis during pregnancy remains controversial. We present our experience of treating 7 pregnant women with acute biliary pancreatitis and verified or suspected choledocholithiasis, by using magnetic resonance cholangiopancreatography (MRCP), endoscopic retrograde cholangiopancreatography (ERCP), and sphincterotomy followed by laparoscopic cholecystectomy. MRCP was performed in all patients to confirm the presence of common bile duct stones, their size and number. ERCP and sphincterotomy were performed without the use of radiation. The procedure was terminated only when all stones (the number clarified at MRCP), were retrieved into the duodenum. All patients underwent laparoscopic cholecystectomy the following day. Neither post-ERCP nor postoperative major complications were noted. All but one patient reached a healthy natural-term labor. One patient had a planned cesarean section on 35th week. The combination of MRCP, nonradiation ERCP, and immediate laparoscopic cholecystectomy provides definite treatment and seems to put both mother and fetus at lower risk than presumed.
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
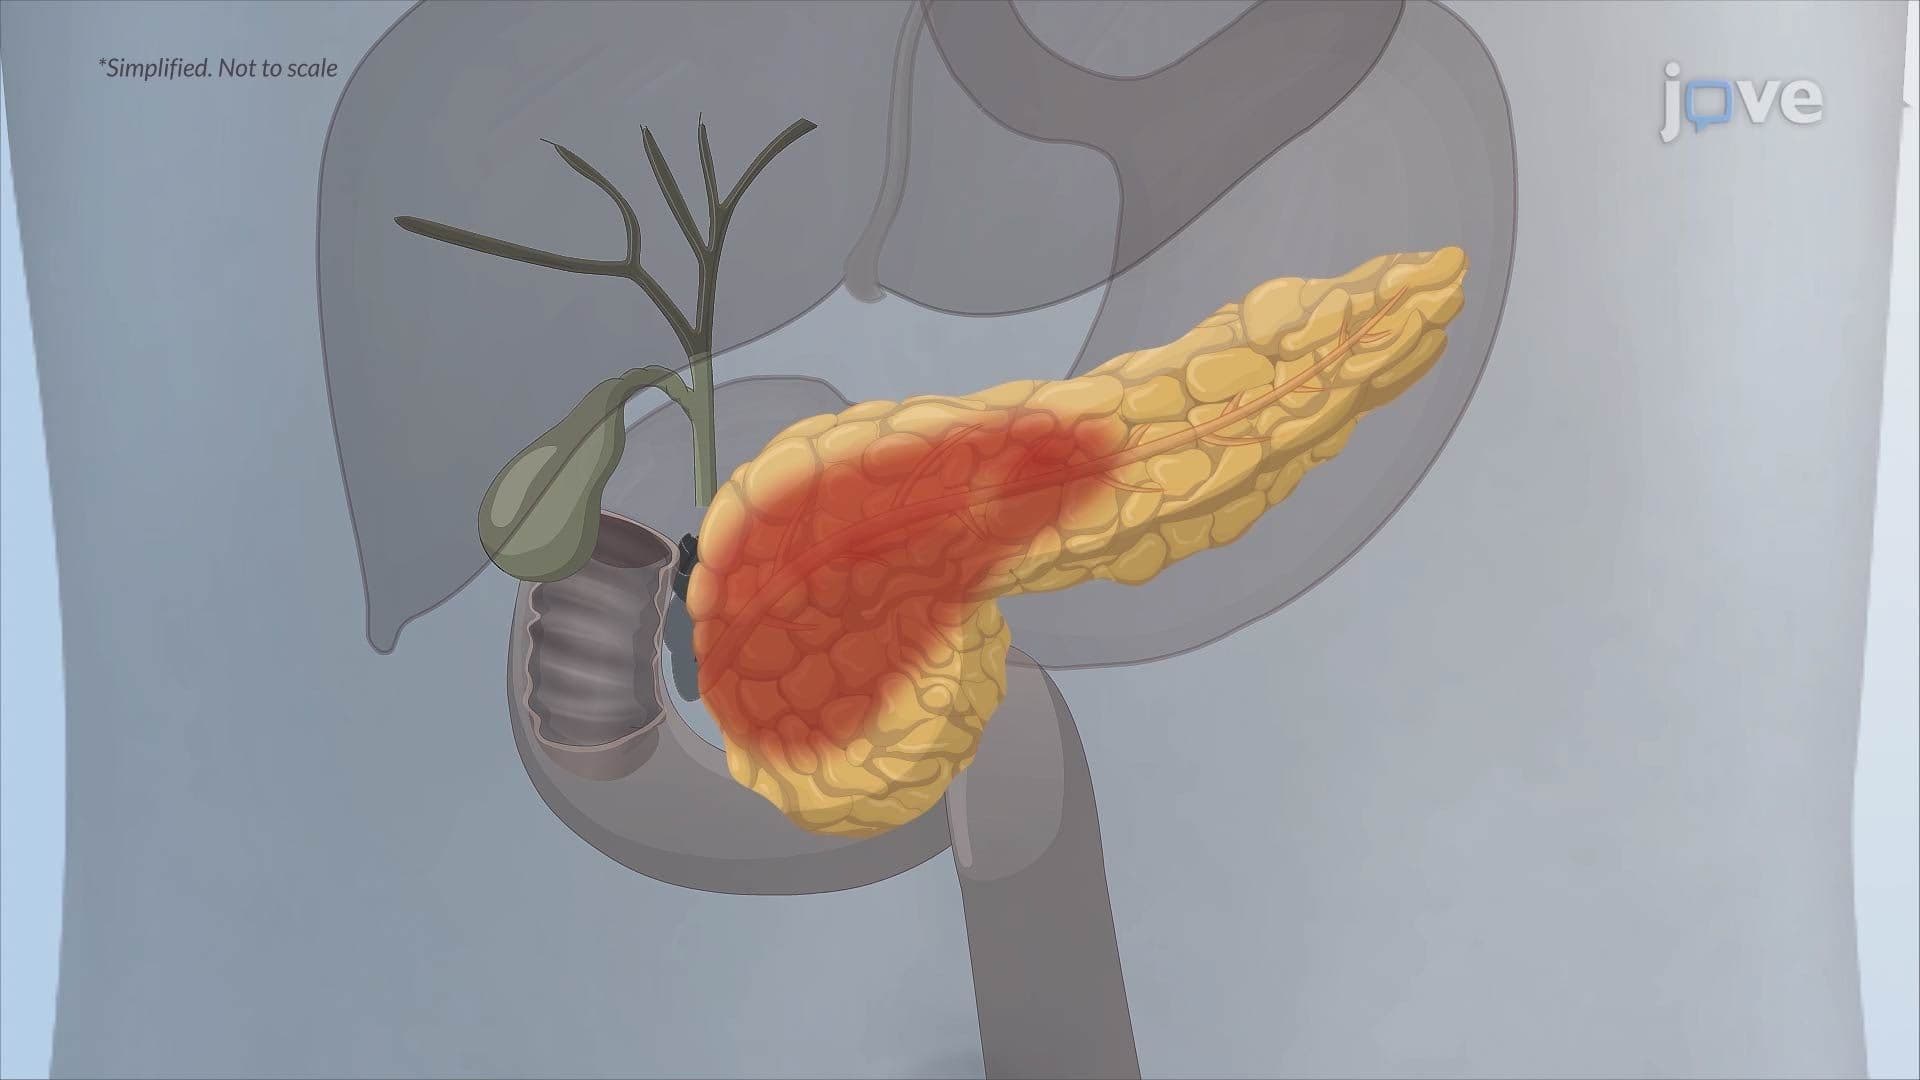
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction