

Prehospital electrocardiographic computer identification of ST-segment elevation myocardial infarction
Mary Colleen Bhalla1, Francis Mencl, Mikki Amber Gist
1Department of Emergency Medicine, Summa Health System, Akron, Ohio 44304, USA. mcmcquown@yahoo.com

Insights
Prehospital computer interpretation of electrocardiograms (ECGs) for ST-segment elevation myocardial infarctions (STEMIs) has 100% specificity but only 58% sensitivity. This tool should not solely activate cardiac catheterization labs due to missed STEMI cases.
Area of Science:
- Cardiology
- Emergency Medicine
- Medical Informatics
Background:
- Field identification of ST-segment elevation myocardial infarctions (STEMIs) is crucial for reducing door-to-balloon times.
- Paramedics utilize computer algorithms for interpreting prehospital electrocardiograms (ECGs).
- The accuracy of computer-aided STEMI identification in prehospital settings remains largely uninvestigated.
Purpose of the Study:
- To evaluate the sensitivity and specificity of prehospital ECG interpretation by a computer algorithm for identifying STEMI patients.
- To assess the diagnostic performance of automated ECG analysis in emergency medical services (EMS).
Main Methods:
- A retrospective cross-sectional study analyzed 200 prehospital ECGs from Lifepak 12 monitors across multiple EMS agencies.
- The study included 100 confirmed STEMI cases and 100 control cases without STEMI.
- Sensitivity and specificity were calculated, with computer interpretation of "acute MI suspected" considered accurate.
Main Results:
- The computer algorithm demonstrated 100% specificity (95% CI 0.96-1.0) for STEMI identification, with zero false positives.
- Sensitivity was 58% (95% CI 0.48-0.67), indicating 42 missed STEMI activations.
- Common misinterpretations included "data quality prohibits interpretation" and "abnormal ECG unconfirmed."
Conclusions:
- Prehospital computer ECG interpretation lacks sufficient sensitivity for reliable STEMI identification.
- The algorithm should not be used as a standalone method for activating cardiac catheterization laboratories.
- Its high specificity suggests potential utility as an adjunctive tool in STEMI diagnosis.
Background:
Identifying ST-segment elevation myocardial infarctions (STEMIs) in the field can decrease door-to-balloon times. Paramedics may use a computer algorithm to help them interpret prehospital electrocariograms (ECGs). It is unknown how accurately the computer can identify STEMIs.
Objectives:
To Determine the sensitivity and specificity of prehospital ECGs in identifying patients with STEMI.
Methods:
Retrospective cross-sectional study of 200 prehospital ECGs acquired using Lifepak 12 monitors and transmitted by one of more than 20 emergency medical services (EMS) agencies to the emergency department (ED) of a Summa Akron City Hospital, a level 1 trauma center between January 1, 2007, and February 18, 2010. The ED sees more than 73,000 adult patients and treats 120 STEMIs annually. The laboratory performs 3,400 catheterizations annually. The first 100 patients with a diagnosis of STEMI and cardiac catheterization laboratory activation from the ED were analyzed. For comparison, a control group of 100 other ECGs from patients without a STEMI were randomly selected from our Medtronic database using a random-number generator. For patients with STEMI, an accurate computer interpretation was "acute MI suspected." Other interpretations were counted as misses. Specificity and sensitivity were calculated with confidence intervals (CIs). The sample size was determined a priori for a 95% CI of ±10%.
Results:
Zero control patients were incorrectly labeled "acute MI suspected." The specificity was 100% (100/100; 95% CI 0.96-1.0), whereas the sensitivity was 58% (58/100; 95% CI 0.48-0.67). This would have resulted in 42 missed cardiac catheterization laboratory activations, but zero inappropriate activations. The most common incorrect interpretation of STEMI ECGs by the computer was "data quality prohibits interpretation," followed by "abnormal ECG unconfirmed."
Conclusions:
Prehospital computer interpretation is not sensitive for STEMI identification and should not be used as a single method for prehospital activation of the cardiac catheterizing laboratory. Because of its high specificity, it may serve as an adjunct to interpretation.

Related Concept Videos
 01:29
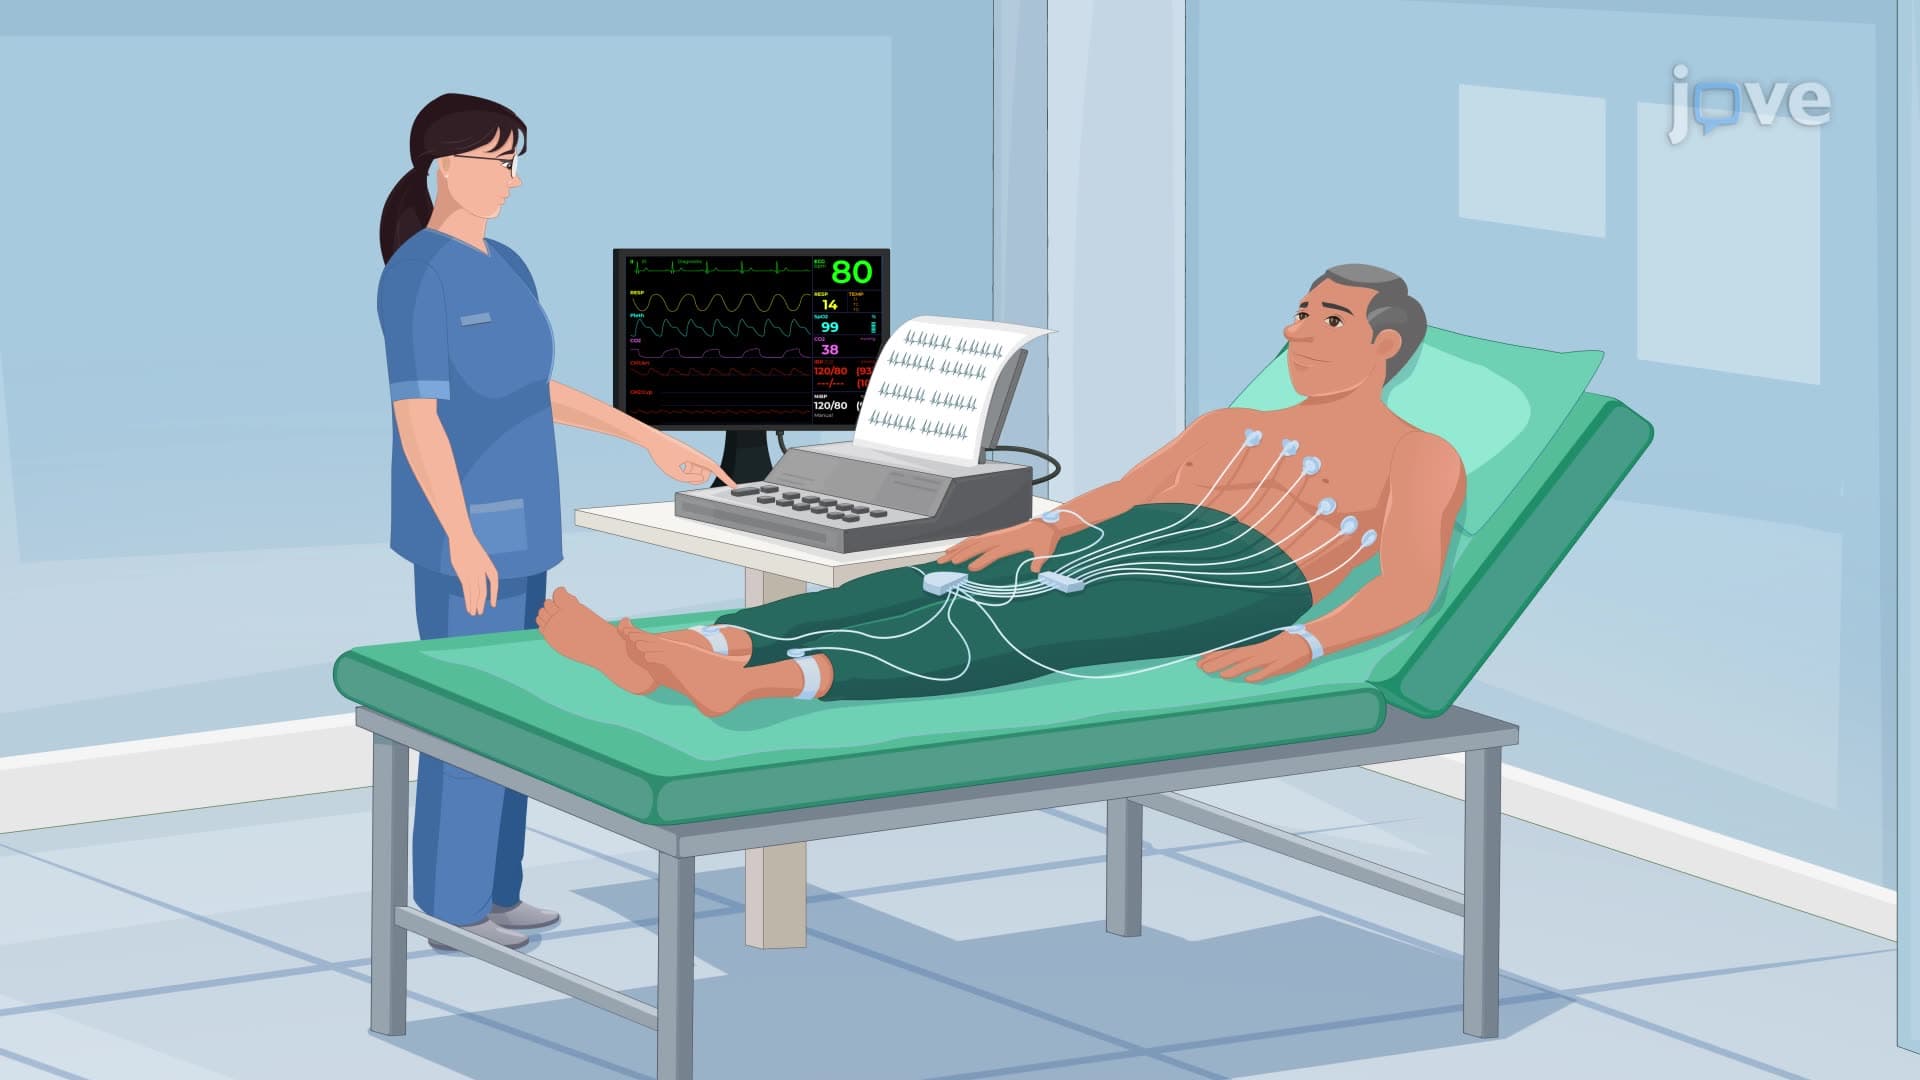
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage. When...
 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...