Related Experiment Video
Updated: May 17, 2026

Retroperitoneal Laparoscopic Debridement and Drainage for Pancreatic Abscess
Published on: March 15, 2024
Advantages of abandoning abdominal cavity irrigation and drainage in operations performed on children with perforated
Ibrahim Akkoyun1, Ayça Taş Tuna
1Department of Pediatric Surgery, Dr Faruk Sükan Maternity and Children Hospital, TR-42090 Konya, Turkey. ibrahimakkoyun@yahoo.com

Insights
Peritoneal irrigation and drainage are not necessary for perforated appendicitis in children. These procedures increase operative time without reducing postoperative complications.
Area of Science:
- Pediatric Surgery
- Surgical Outcomes
- Infectious Disease
Background:
- Perforated appendicitis is a common surgical emergency in children.
- The role of adjunctive peritoneal irrigation and drainage in managing perforated appendicitis remains debated.
- Optimizing surgical techniques to minimize postoperative morbidity is crucial.
Purpose of the Study:
- To evaluate the impact of peritoneal irrigation and drainage on postoperative morbidity in pediatric patients with perforated appendicitis.
- To compare complication rates, operative time, and hospital stay between patients who underwent irrigation and drainage versus those who did not.
Main Methods:
- Retrospective evaluation of 234 children undergoing open appendectomy for perforated appendicitis.
- Group DI (n=61) received peritoneal irrigation and drainage; Group NDI (n=173) did not.
- Comparison of postoperative complications, operative time, and length of hospital stay.
Main Results:
- No statistically significant differences in wound infection, wound dehiscence, intraabdominal abscess, or prolonged ileus between groups.
- Significantly longer operative times (39 vs. 31 minutes) and hospital stays (9.9 vs. 6.3 days) in the irrigation and drainage group (P < .001).
Conclusions:
- Peritoneal irrigation and drainage are not required for children with perforated appendicitis.
- These procedures are associated with increased operative time and hospital stay without improving infectious outcomes.
Purpose:
This study evaluates the effect of peritoneal irrigation and drainage on postoperative morbidity when used together for perforated appendicitis.
Material And Methods:
This study was conducted on children undergoing open appendectomy for perforated appendicitis. Sixty-one children with perforated appendicitis operated on with irrigation and drainage between July 1998 and September 2001 (group DI) and 173 children with perforated appendicitis who underwent surgery without irrigation and drainage (group NDI) between October 2001 and November 2011 were retrospectively evaluated (a total of 234 patients). All patients were treated and followed up by the same pediatric surgeon using the same protocol. Both groups were compared in respect to postoperative complications, including wound infection, wound dehiscence, intraabdominal abscess, prolonged ileus, the presence of small bowel obstruction requiring surgery, operative time, and length of postoperative hospital stay.
Results:
Of the total 234 patients, 151 were male and 83 were female with a mean age of 8.9 ± 3.7 years (range, 1.5-15 years). The wound infection rates were 4.9% in group DI and 1.7% in group NDI (P = .184). Wound dehiscence was seen in 1.6% vs 0%, prolonged ileus in 8% vs 2.3%, intraabdominal abscess in 4.9% vs 1.7%, and small bowel obstruction requiring surgery in 1.6% vs 0.6% of the patients (P = .261, P = .054, P = .184, and P = .454, respectively). No statistically significant difference in postoperative infectious complications was found between both groups. The length of postoperative hospital stay was 9.9 ± 4.1 days in group DI vs 6.3 ± 2.4 days in group NDI (P < .001). The operation times were 39 ± 8 and 31 ± 11 minutes, respectively (P < .001).
Conclusion:
This study demonstrates that peritoneal irrigation and drainage in children with perforated appendicitis is not required, and in fact, these procedures cause an increase in operative time.

Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
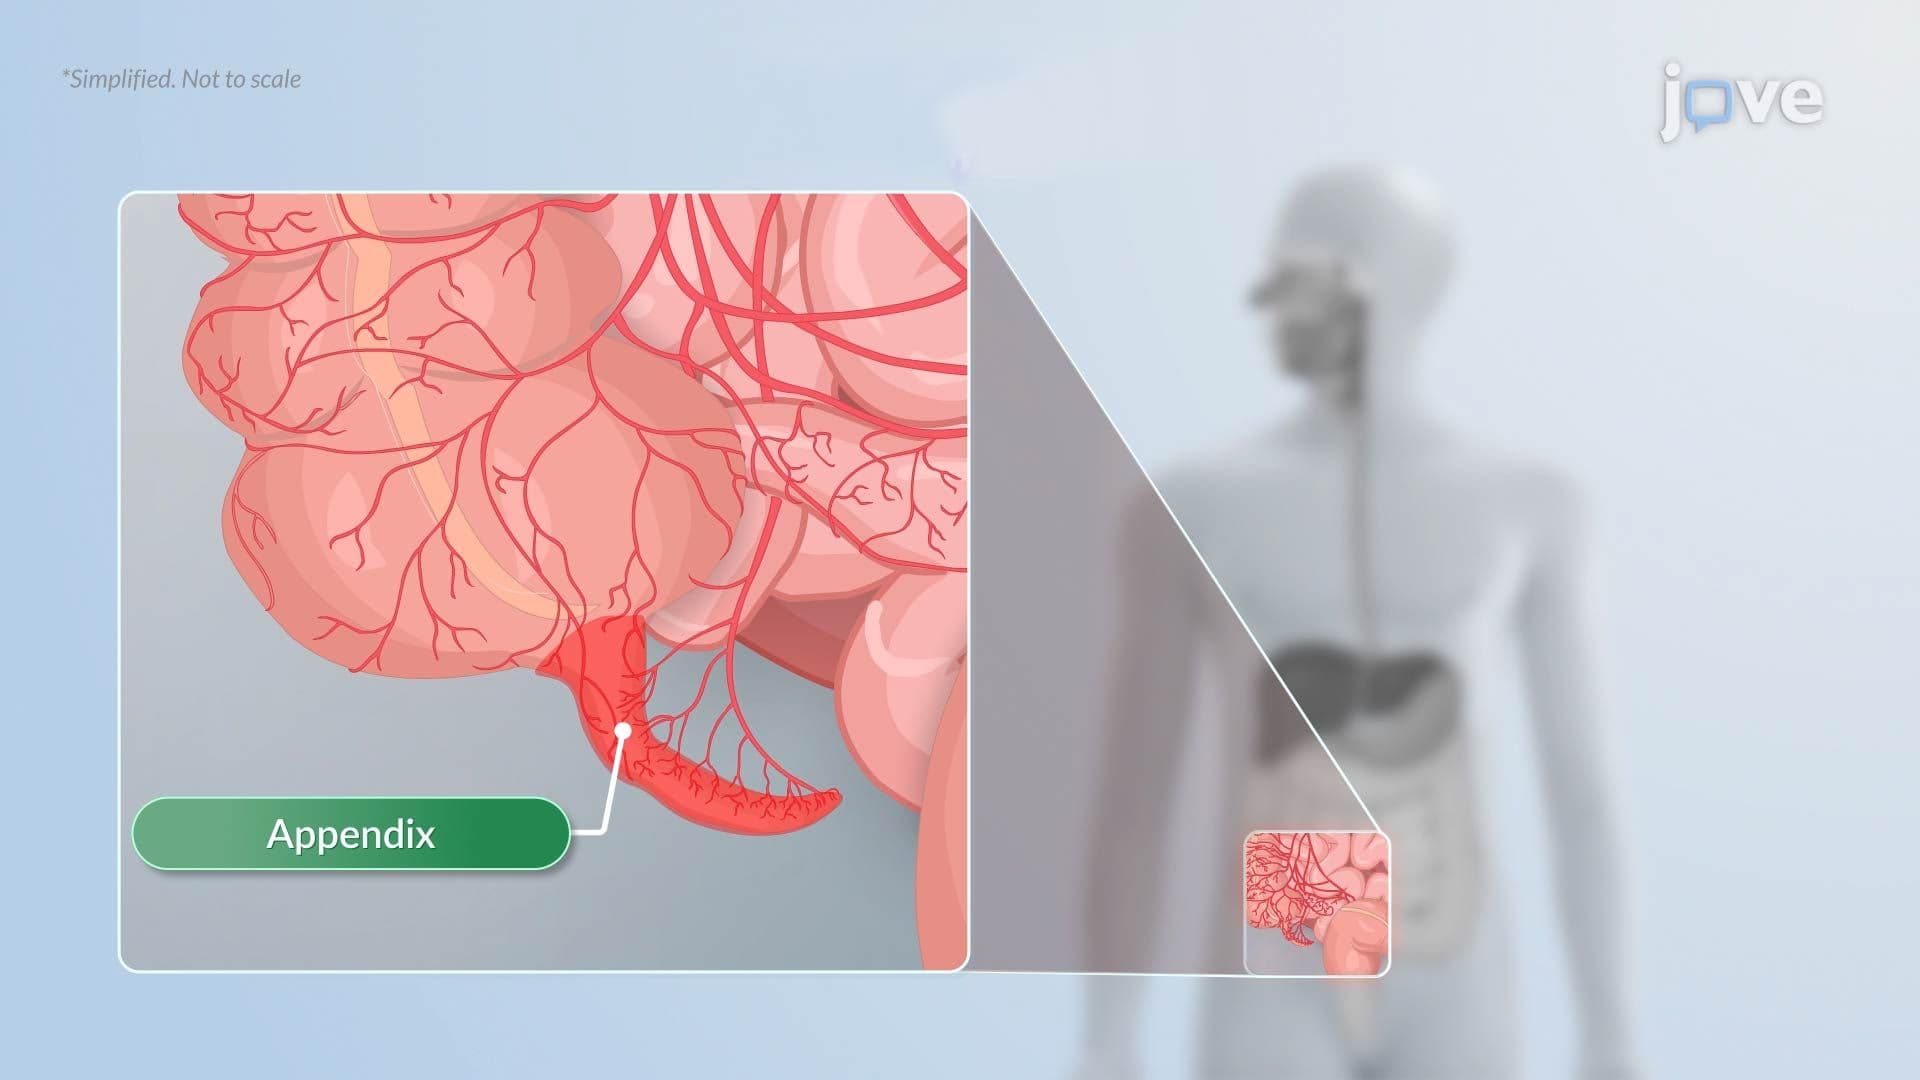 01:19
Appendicitis
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...