Related Experiment Video
Updated: May 17, 2026
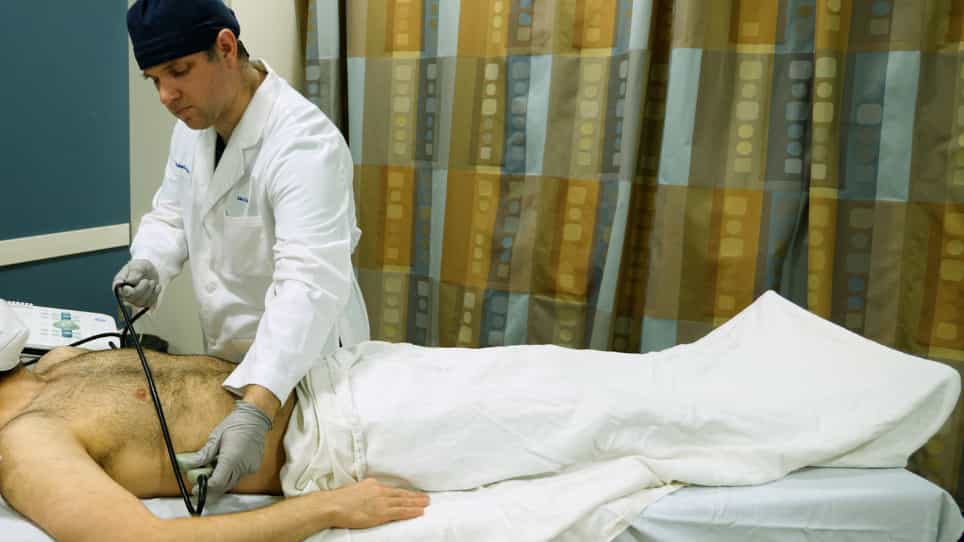
Focused Assessment with Sonography for Trauma (FAST) Exam: Image Acquisition
Published on: September 22, 2023
Screening for blunt cardiac injury: an Eastern Association for the Surgery of Trauma practice management guideline
Keith Clancy1, Catherine Velopulos, Jaroslaw W Bilaniuk
1Department of Surgery, York Hospital Trauma Program, York, Pennsylvania 17405, USA. kdclancy@yahoo.com

Insights
Diagnosing blunt cardiac injury (BCI) requires more than an electrocardiogram (ECG). Combining ECG with troponin I levels is crucial for ruling out BCI in at-risk patients.
Area of Science:
- Trauma Surgery
- Cardiology
- Emergency Medicine
Background:
- Blunt cardiac injury (BCI) diagnosis is challenging, particularly in hemodynamically stable patients.
- Current practices debate the necessity of higher-level care for patients with potential BCI.
- Definitive BCI exclusion is essential for safe patient discharge or non-monitored admission.
Purpose of the Study:
- To update practice management guidelines for diagnosing blunt cardiac injury.
- To provide evidence-based recommendations for ruling out BCI in at-risk patients.
- To clarify diagnostic criteria and patient management strategies for suspected BCI.
Main Methods:
- Systematic review of English-language literature on BCI diagnosis from March 1997 to December 2011.
- Utilized PubMed Entrez for citation searching, identifying and selecting relevant prospective and retrospective studies.
- Consensus-based recommendations developed by the EAST BCI Practice Management Guideline workgroup.
Main Results:
- Analysis of 35 institutional studies on adult BCI diagnosis.
- The updated guideline includes 10 recommendations, with several Level 2 updates and new recommendations.
- Identified specific diagnostic criteria and imaging modalities for BCI evaluation.
Conclusions:
- Electrocardiogram (ECG) alone is insufficient to rule out BCI.
- Admission ECG and troponin I are recommended for all suspected BCI cases; normal results for both rule out BCI.
- Echocardiogram is reserved for specific indications; sternal fracture alone does not predict BCI.
Background:
Diagnosing blunt cardiac injury (BCI) can be difficult. Many patients with mechanism for BCI are admitted to the critical care setting based on associated injuries; however, debate surrounds those patients who are hemodynamically stable and do not otherwise require a higher level of care. To allow safe discharge home or admission to a nonmonitored setting, BCI should be definitively ruled out in those at risk.
Methods:
This Eastern Association for the Surgery of Trauma (EAST) practice management guideline (PMG) updates the original from 1998. English-language citations were queried for BCI from March 1997 through December 2011, using the PubMed Entrez interface. Of 599 articles identified, prospective or retrospective studies examining BCI were selected. Each article was reviewed by two members of the EAST BCI PMG workgroup. Data were collated, and a consensus was obtained for the recommendations.
Results:
We identified 35 institutional studies evaluating the diagnosis of adult patients with suspected BCI. This PMG has 10 total recommendations, including two Level 2 updates, two upgrades from Level 3 to Level 2, and three new recommendations.
Conclusion:
Electrocardiogram (ECG) alone is not sufficient to rule out BCI. Based on four studies showing that the addition of troponin I to ECG improved the negative predictive value to 100%, we recommend obtaining an admission ECG and troponin I from all patients in whom BCI is suspected. BCI can be ruled out only if both ECG result and troponin I level are normal, a significant change from the previous guideline. Patients with new ECG changes and/or elevated troponin I should be admitted for monitoring. Echocardiogram is not beneficial as a screening tool for BCI and should be reserved for patients with hypotension and/or arrhythmias. The presence of a sternal fracture alone does not predict BCI. Cardiac computed tomography or magnetic resonance imaging can be used to differentiate acute myocardial infarction from BCI in trauma patients.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:22
Aneurysm IV: Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Acute Coronary Syndrome I: Introduction
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management