Related Experiment Video
Updated: May 16, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Bilateral and unilateral adrenal incidentalomas: biochemical and clinical characteristics
V Morelli1, S Palmieri, A S Salcuni
1Endocrinology and Diabetology Unit, Department of Clinical Sciences and Community Health, University of Milan, Fondazione IRCCS Cà Granda - Ospedale Maggiore Policlinico, Padiglione Granelli, Via Francesco Sforza 35, 20122 Milan, Italy. morellivale@yahoo.it

Objective:
The possible different prevalence of arterial hypertension (AH), type 2 diabetes mellitus (T2DM), dyslipidaemia (DL) and vertebral fractures (FX) between patients with bilateral and unilateral adrenal incidentalomas (BAI and UAI, respectively) with and without subclinical hypercortisolism (SH) is unknown. In this study we compared the prevalence of AH, T2DM, DL and FX in BAI and UAI patients in relation to SH.
Design:
Prospective study.
Methods:
In 175 UAI and 38 BAI patients, we evaluated BMI, spinal and femoral bone mineral density (LS and FN BMD, respectively) and the presence of AH, T2DM, DL and FX. SH was diagnosed in the presence of 2 of the following: urinary free cortisol levels >193 nmol/24 h, serum cortisol levels after 1 mg dexamethasone suppression test >83 nmol/l or ACTH levels <2.2 pmol/l.
Results:
Age, BMI and cortisol secretion were comparable, while FN BMD was lower in BAI than in UAI patients (-0.45±0.86 vs 0.09±1.07, P=0.004). The prevalence of SH, AH, T2DM, and DL was comparable, while the prevalence of FX was higher in BAI than in UAI (52.6 vs 28%, P=0.007). The presence of FX was associated with BAI (odds ratio (OR) 2.6, 95% confidence interval (95% CI) 1.2-5.6, P=0.016), after adjusting for SH (OR 1.77, 95% CI 0.85-3.7, P=0.12), BMI (OR 1.06, 95% CI 0.98-1.13, P=0.1), age (OR 1.07, 95% CI 1.04-1.11, P=0.0001) and LS BMD (OR 1.31, 95% CI 1.03-1.67, P=0.03).
Conclusion:
BAI patients have an increased FX risk than UAI ones. Further studies should investigate the causes of bone involvement in BAI patients.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:26
Cushing Syndrome I: Introduction
 01:17
Anatomy of the Adrenal Glands
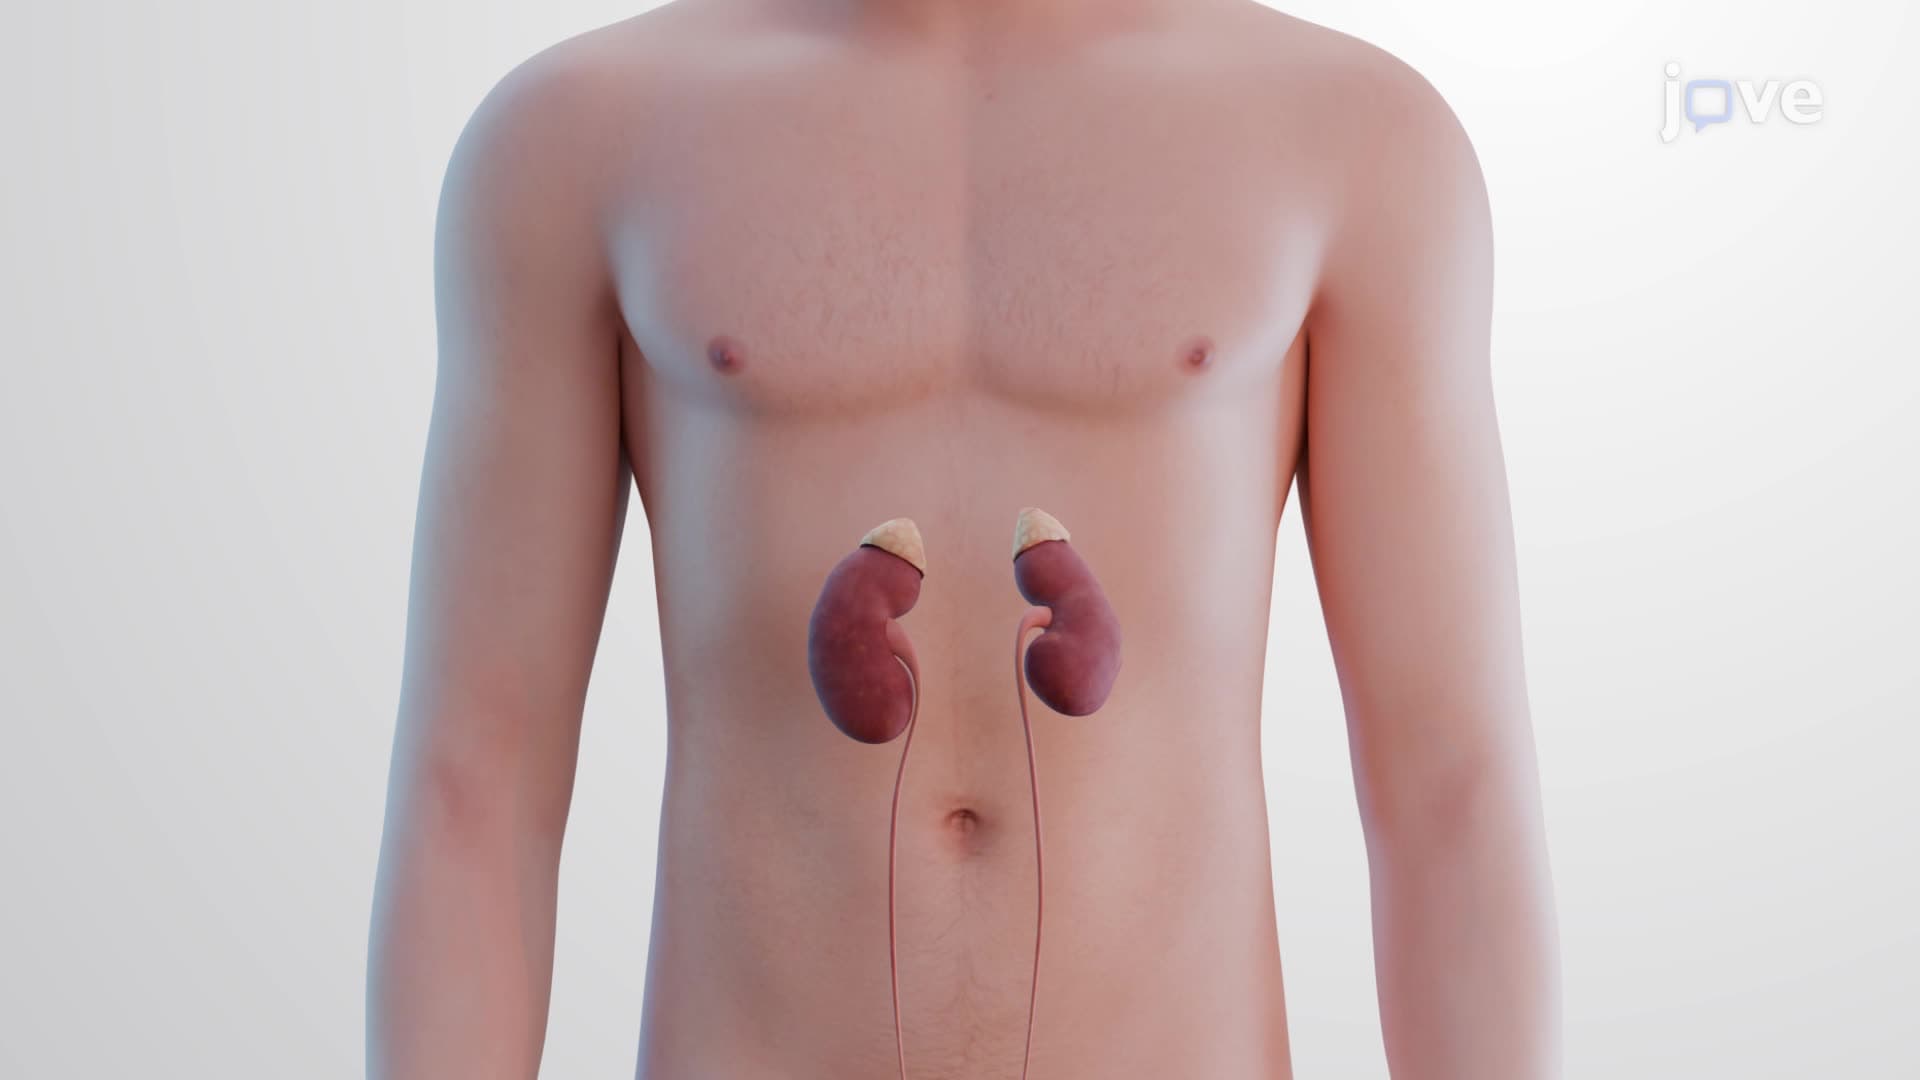
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:19
Cushing Syndrome II: Pathophysiology
 01:31
Hormones of the Adrenal Glands
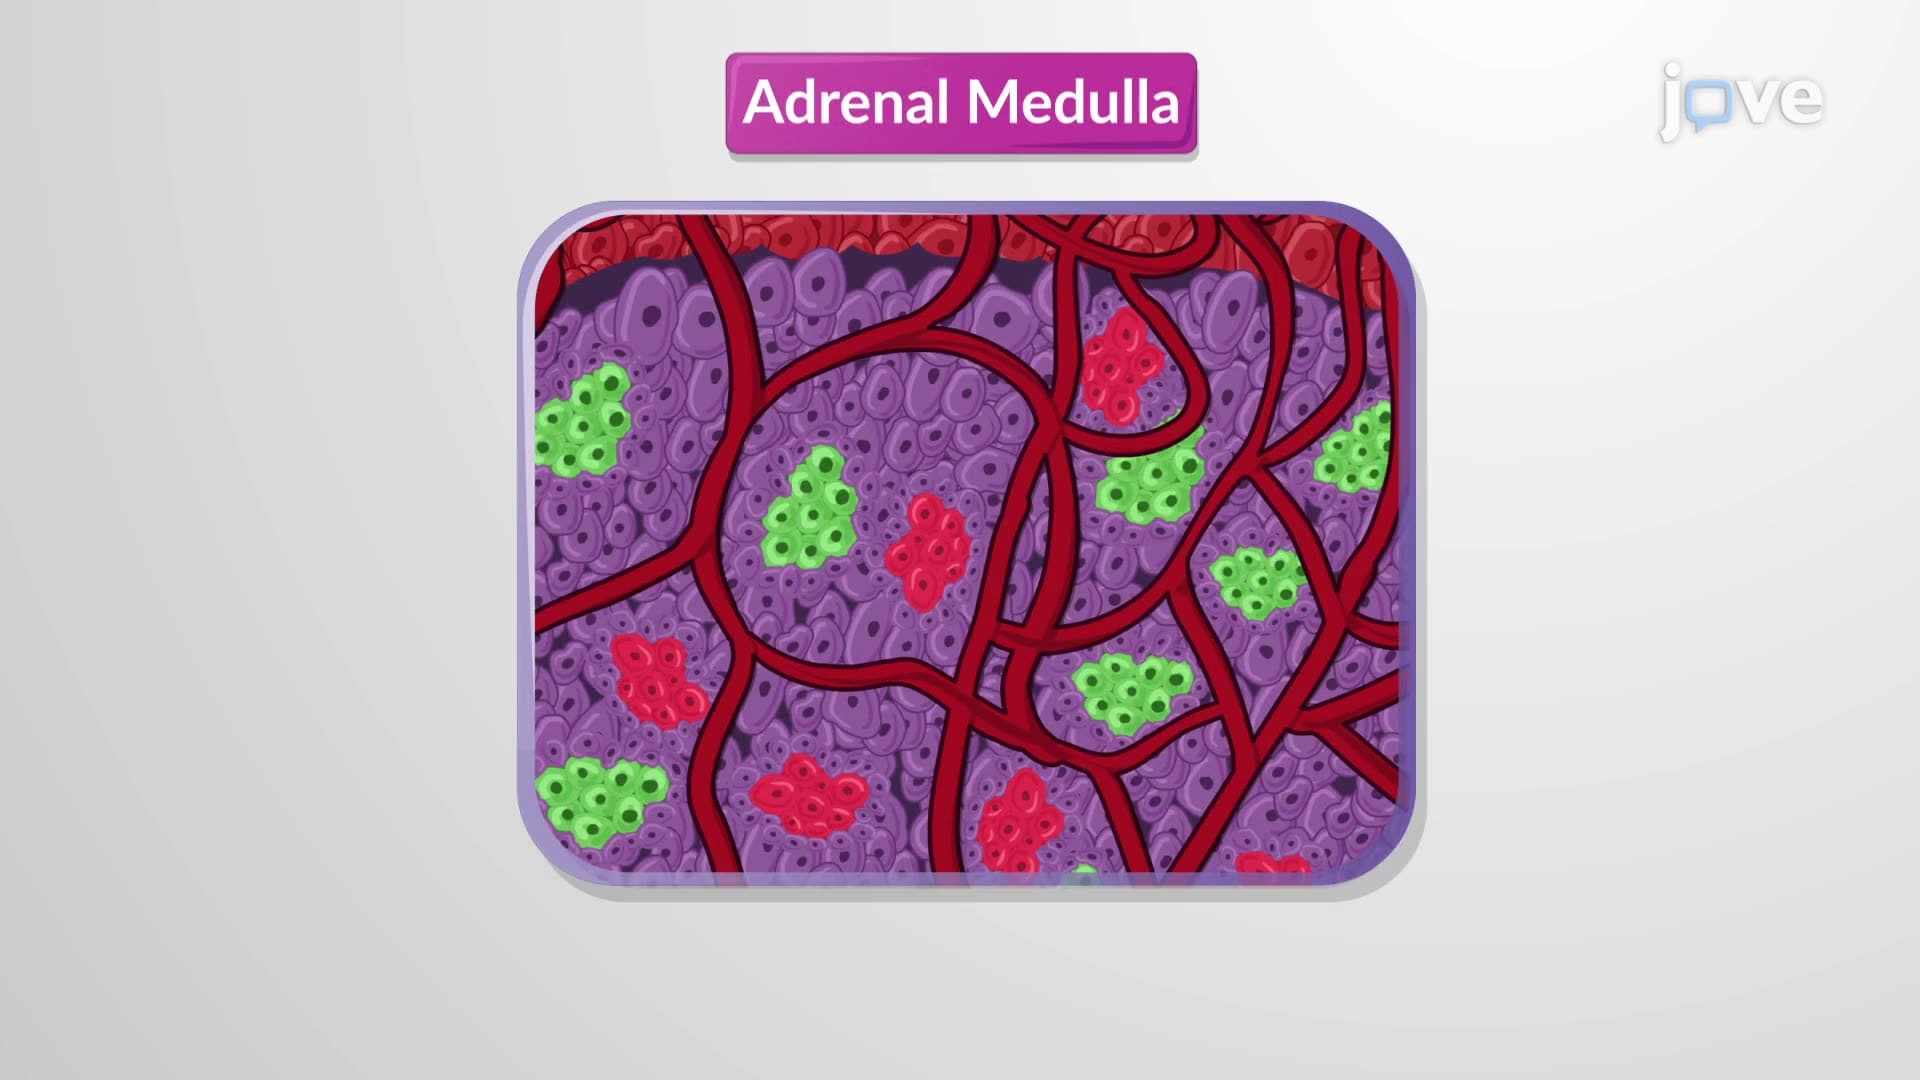
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:27
Sympathetic Pathways: Collateral Ganglia and Adrenal Medulla
Collateral Ganglia
Sympathetic preganglionic axons reach the collateral ganglia along the route of splanchnic nerves. These nerves bypass the sympathetic trunk and communicate with sympathetic postganglionic neurons housed in the prevertebral ganglia. These ganglia supply the organs of the abdominopelvic cavity.
The greater splanchnic nerve, formed by the...