Single-access laparoscopic adjustable gastric band removal: technique and initial experience
Related Experiment Video
Updated: May 16, 2026
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Giovanni Dapri1, Haicam El Mourad, Perrine Mathonet
1Department of Gastrointestinal Surgery, European School of Laparoscopic Surgery, Saint-Pierre University Hospital, 322, Rue Haute, 1000, Brussels, Belgium. giovanni@dapri.net

Background:
Single-access laparoscopy (SAL) has gained significant interest in recent years. Potential benefits, beyond cosmetic outcomes, could be reduction of abdominal trauma, decreased risk of incisional hernia and diminished postoperative pain. Technique and initial experience in patients submitted to laparoscopic adjustable gastric band removal (LAGBR) through SAL is reported here.
Methods:
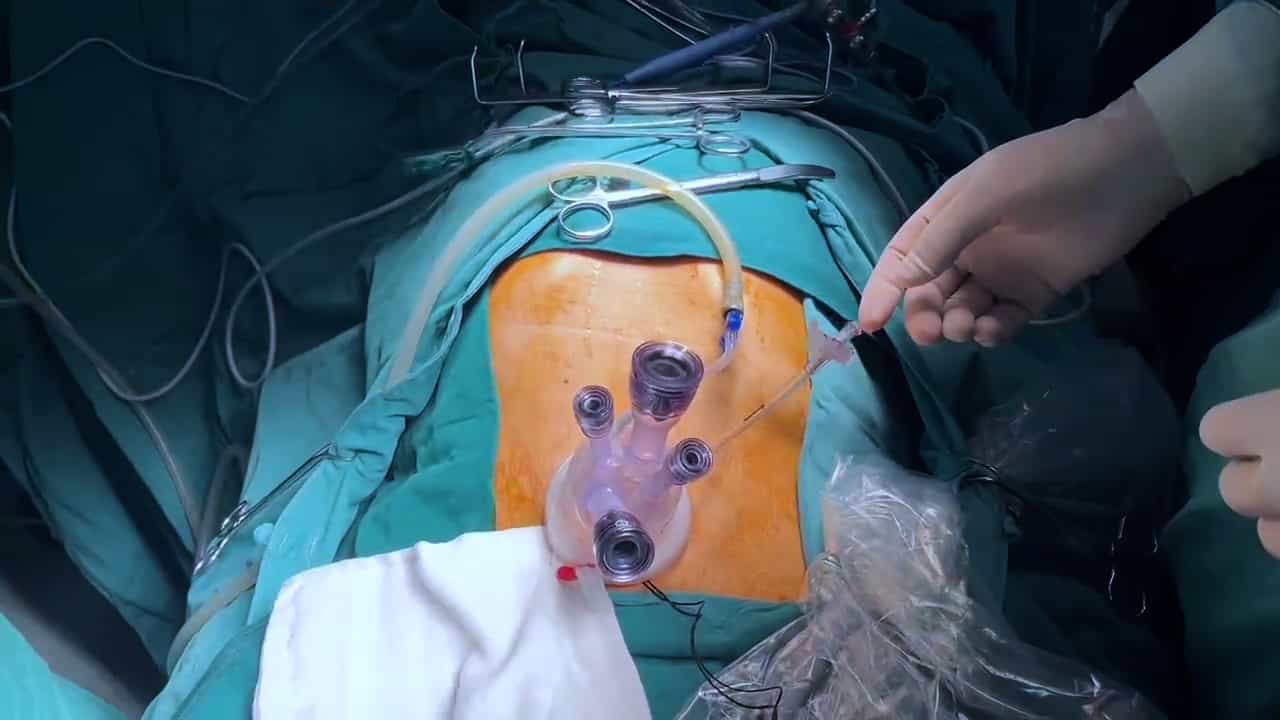
Between December 2009 and March 2012, 14 patients (9 females, 5 males) underwent LAGBR through SAL. Indications for operation were band intolerance (11), pouch dilatation (2) and insufficient weight loss (1). The mean age was 40.3 ± 9.1 years (range 26-57), and the mean interval time between LAGB placement and removal was 94.7 ± 41.9 months (range 37-157). The mean weight and the mean body mass index at the time of LAGBR were 89.3 ± 17.6 kg (range 65-119) and 30.6 ± 4.5 kg/m(2) (range 25.3-36.7), respectively. Technically, the previous port site scar was used as the single-access site to the abdominal cavity. An 11-mm reusable trocar was adopted for a 10-mm regular scope, besides curved reusable instruments.
Results:
No patients required conversion to open surgery and none necessitated additional trocars. The mean laparoscopic time was 24.6 ± 7.9 min (range 13-37), and the mean final scar length was 3.6 ± 0.3 cm (range 3-4). Two patients experienced early postoperative complications. The mean hospital stay was 1.3 ± 1.1 days (range 1-5). The mean follow-up time was of 18 ± 9.8 months (range 3-30), and there were no late complications.
Conclusions:
LAGBR can be safely performed through SAL. Thanks to this technique, the laparoscopic working triangulation is established as well as the ergonomic positions of the surgeon. Due the use of only reusable material, the cost of this SAL remains similar to multiport laparoscopy.
