Related Experiment Video
Updated: May 15, 2026


Surgical Approach and Complications of Stand-alone Lateral Trans-Psoas Interbody Fusion
Published on: February 14, 2025
Analysis of lumbar plexopathies and nerve injury after lateral retroperitoneal transpsoas approach: diagnostic
Amir Ahmadian1, Armen R Deukmedjian, Naomi Abel
1Department of Neurosurgery, University of South Florida, Tampa, FL 33606, USA.

Object:
The minimally invasive lateral transpsoas approach has become an increasingly popular means of fusion. The most frequent complication is related to lumbar plexus nerve injuries; these can be diagnosed based on distribution of neurological deficit following the motor and/or sensory nerve injury. However, the literature has failed to provide a clinically relevant description of these complications. With accurate clinical diagnosis, spine practitioners can provide more precise prognostic and management recommendations to include observation, nerve blocks, neurodestructive procedures, medications, or surgical repair strategies. The purpose of this study was to standardize the clinical findings of lumbar plexopathies and nerve injuries associated with minimally invasive lateral retroperitoneal transpsoas lumbar fusion.
Methods:
A thorough literature search of the MEDLINE database up to June 2012 was performed to identify studies that reported lumbar plexus and nerve injuries after the minimally invasive lateral retroperitoneal transpsoas approach. Included studies were assessed for described neurological deficits postoperatively. Studies that did attempt to describe nerve-related complications clinically were excluded. A clinically relevant assessment of lumbar plexus nerve injury was derived to standardize early diagnosis and outline prognostic implications.
Results:
A total of 18 studies were selected with a total of 2310 patients; 304 patients were reported to have possible plexus-related complications. The incidence of documented nerve and/or root injury and abdominal paresis ranged from 0% to 3.4% and 4.2%, respectively. Motor weakness ranged from 0.7% to 33.6%. Sensory complications ranged from 0% to 75%. A lack of consistency in the descriptions of the lumbar plexopathies and/or nerve injuries as well as a lack of diagnostic paradigms was noted across studies reviewed. Sensory dermal zones were established and a standardized approach was proposed.
Conclusions:
There is underreporting of postoperative lumbar plexus nerve injury and a lack of standardization of clinical findings of neural complications related to the minimally invasive lateral retroperitoneal transpsoas approach. The authors provide a diagnostic paradigm that allows for an efficient and accurate classification of postoperative lumbar plexopathies and nerve injuries.

Related Concept Videos
 01:21
Spinal Nerves: Plexus II
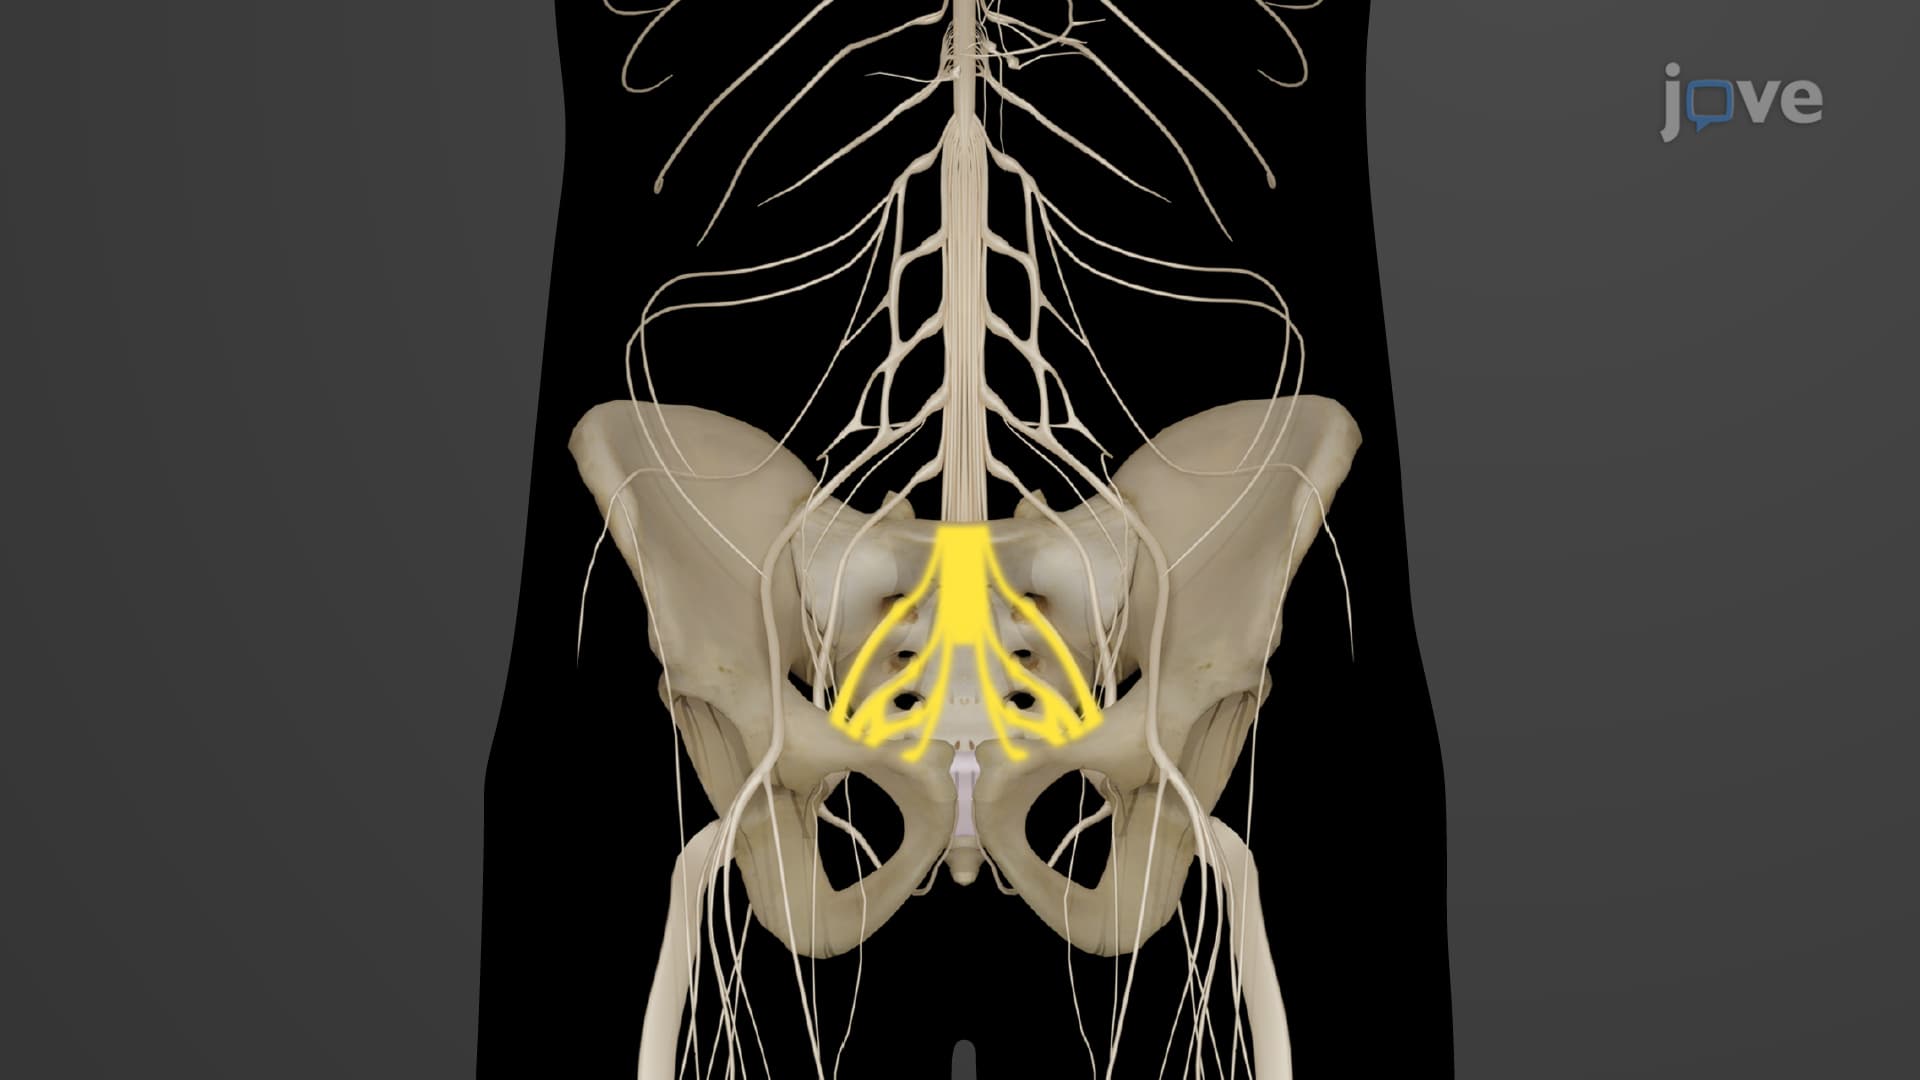
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...