Related Experiment Video
Updated: May 15, 2026

LDL Cholesterol Uptake Assay Using Live Cell Imaging Analysis with Cell Health Monitoring
Published on: November 17, 2018
Effective hypolipidaemic therapy with beclobrate in haemodialysis patients: interference with L-carnitine
1Department of Medicine, Division of Nephrology, University of Freiburg, FRG.

The lipid-reducing effects of a new fibric acid derivative (beclobrate, 100 mg/day), L-carnitine (15 mg/ kg b.w. thrice weekly i.v.), and the administration of both drugs were investigated in hyperlipidaemic haemodialysis patients. Beclobrate significantly decreased serum triglycerides, cholesterol and phospholipids. This was predominantly due to reducing the VLDL fraction. Plasma values of beclobric acid remained within the therapeutic range throughout the study. Carnitine administration did not influence plasma beclobric acid values. On the other hand, beclobrate caused a significant decrease of serum values of short-chain and long-chain carnitine esters in patients treated with both drugs. Carnitine therapy showed a tendency to affect total triglycerides, cholesterol, or phospholipids. However, carnitine antagonised the VLDL-reducing effect of beclobrate when both drugs were combined. Our data demonstrate a potent lipid-reducing effect of the new fibric acid derivative (beclobrate) in haemodialysis patients. Single-dose drug administration resulted in therapeutic beclobric acid plasma values and did not give evidence for drug accumulation. Careful monitoring of serum lipids is recommended for haemodialysis patients on carnitine therapy treated with lipid-reducing substances of the 'fibrate' group.
The lipid-reducing effects of a new fibric acid derivative (beclobrate, 100 mg/day), L-carnitine (15 mg/ kg b.w. thrice weekly i.v.), and the administration of both drugs were investigated in hyperlipidaemic haemodialysis patients. Beclobrate significantly decreased serum triglycerides, cholesterol and phospholipids. This was predominantly due to reducing the VLDL fraction. Plasma values of beclobric acid remained within the therapeutic range throughout the study. Carnitine administration did not influence plasma beclobric acid values. On the other hand, beclobrate caused a significant decrease of serum values of short-chain and long-chain carnitine esters in patients treated with both drugs. Carnitine therapy showed a tendency to affect total triglycerides, cholesterol, or phospholipids. However, carnitine antagonised the VLDL-reducing effect of beclobrate when both drugs were combined. Our data demonstrate a potent lipid-reducing effect of the new fibric acid derivative (beclobrate) in haemodialysis patients. Single-dose drug administration resulted in therapeutic beclobric acid plasma values and did not give evidence for drug accumulation. Careful monitoring of serum lipids is recommended for haemodialysis patients on carnitine therapy treated with lipid-reducing substances of the 'fibrate' group.
Related Concept Videos
 01:20
Lipid-Lowering Drugs: Statins and Miscellaneous Agents
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:09
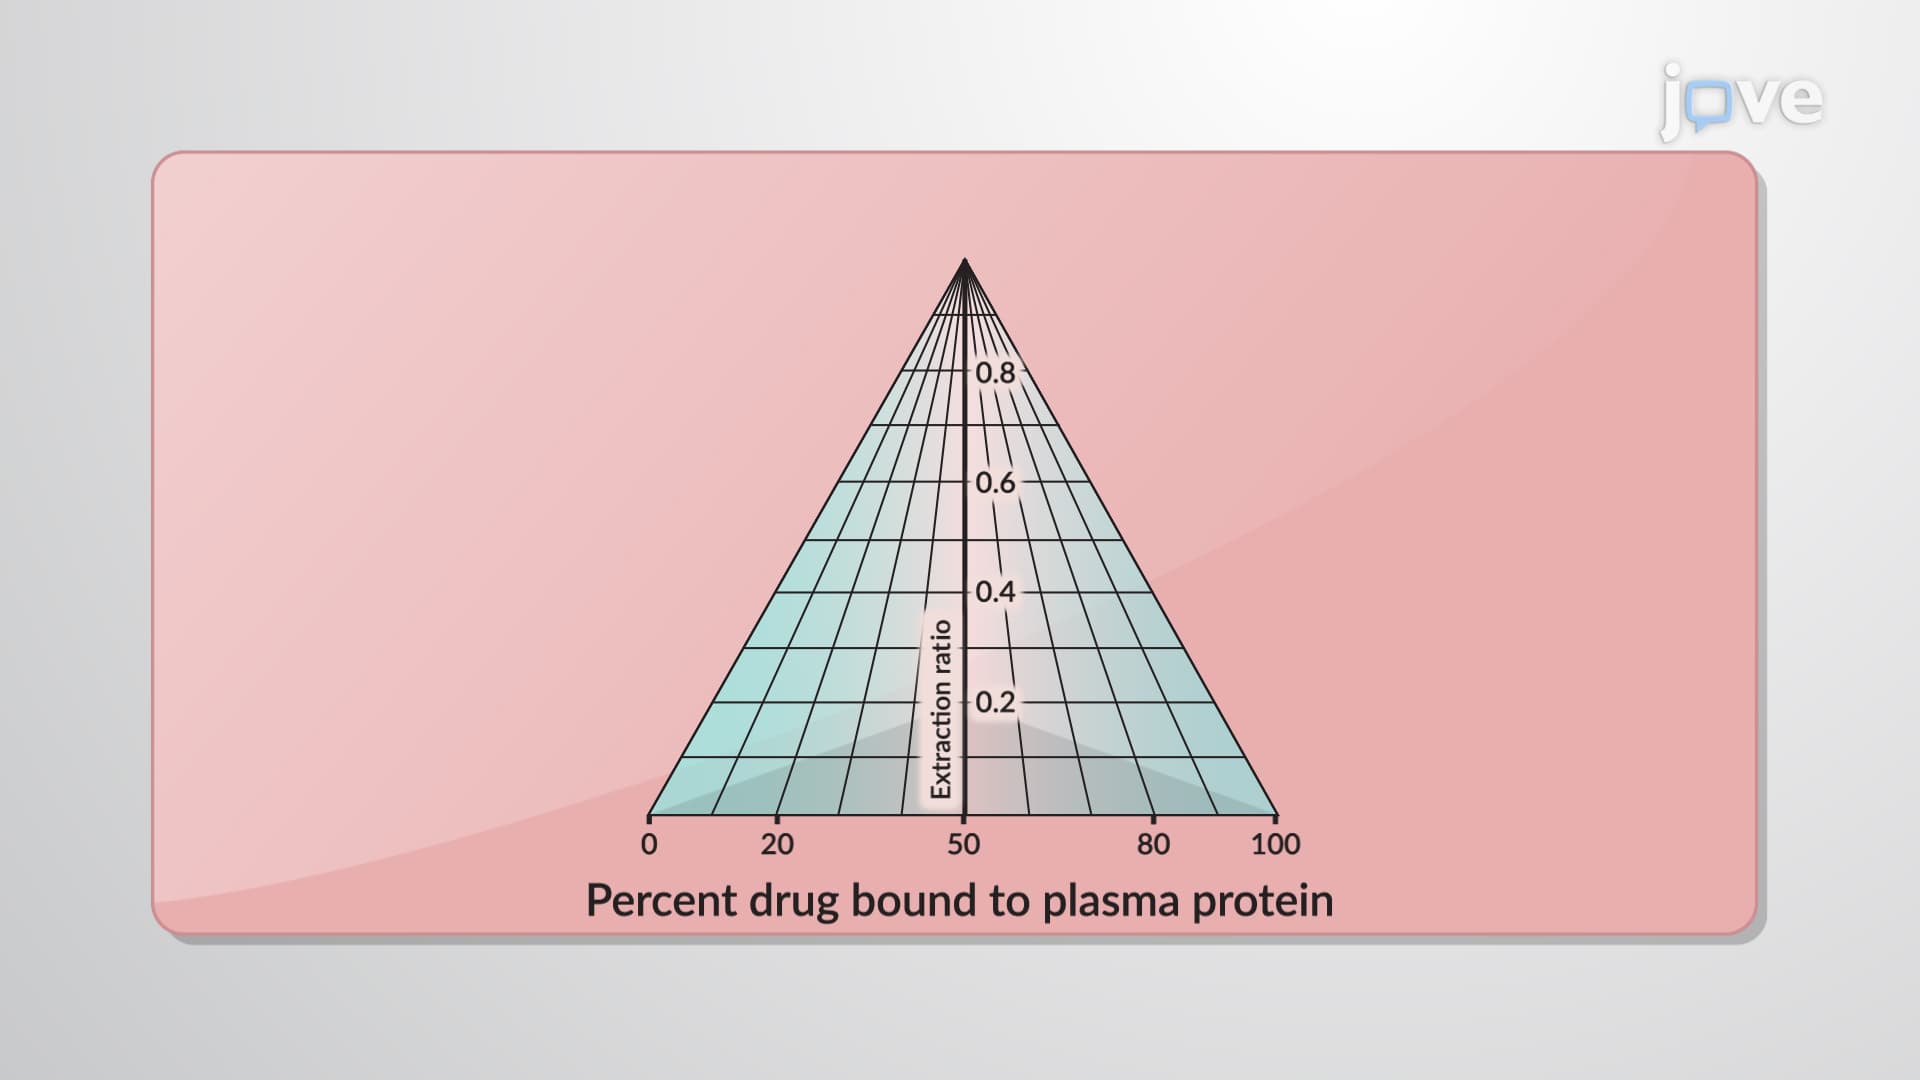
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...