Related Experiment Video
Updated: May 14, 2026

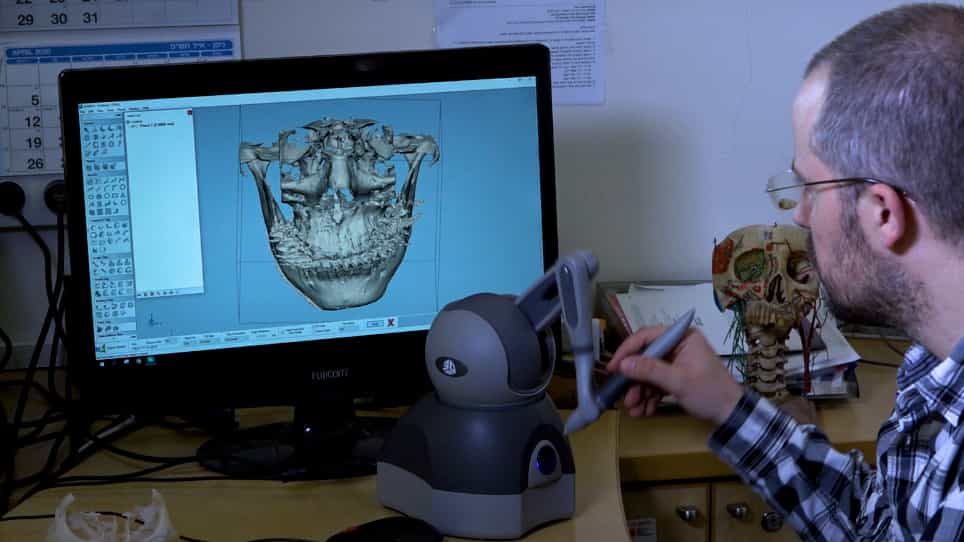
Designing CAD/CAM Surgical Guides for Maxillary Reconstruction Using an In-house Approach
Published on: August 24, 2018
Monobloc and bipartition in craniofacial surgery
Alistair R M Cobb1, Peter Boavida, Rosanne Docherty
1Craniofacial Centre, Great Ormond Street Hospital for Children, Great Ormond St, London WC1N 3JH, United Kingdom. alicobb@yahoo.com

Background:
The frontofacial monobloc advancement with osteogenic distraction is increasingly used as a surgical treatment for children with complex craniosynostosis-associated syndromes. However, the subfrontal osteotomy cuts to free the facial skeleton from the skull base require extradural retraction of the frontal lobes. The purpose of this study was to determine the frequency and degree of radiologically identifiable frontal lobe changes and whether any such changes affected the patients' outcome.
Methods:
The clinical records and preoperative and postoperative computed tomography imaging of all patients undergoing monobloc frontofacial distraction advancement (with or without bipartition) were reviewed. A retrospective medical notes review was undertaken to assess any patient or surgically related factors that might predispose to frontal lobe changes and evaluate outcome from surgery. Where available, magnetic resonance imaging scans were reviewed to compare outcome with that on computed tomography.
Results:
Fifty cases were identified as suitable for the study. Eighteen patients (36%) had no frontal lobe changes. Thirty-two cases (64%) did have changes that appeared related to the position of maximum retraction during subfrontal osteotomy cuts. There were no changes in the incidence/extent of these changes over time or of any link to the patients' diagnosis, age at surgery, phenotype severity, surgery type, or any surgical or postoperative adverse events. We found no evidence that these changes were responsible for neurologic problems (eg, epilepsy) or reduced cognitive function.
Conclusions:
This study reveals a high incidence of frontal lobe changes demonstrable on neuroimaging following the frontofacial monobloc procedure reflecting the retraction points during surgery. Although no postoperative disability was reported, it is clearly important to consider more detailed neuropsychologic testing and review current surgical techniques to ensure that such changes are kept to a minimum.
Related Concept Videos
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...