Related Experiment Video
Updated: May 14, 2026


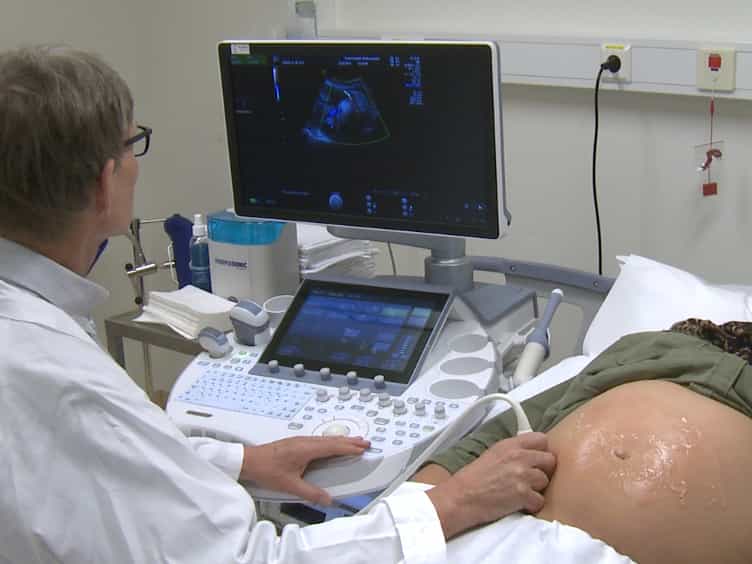
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
The placental factor in early- and late-onset normotensive fetal growth restriction
M Kovo1, L Schreiber, A Ben-Haroush
1Department of Obstetrics & Gynecology, Edith Wolfson Medical Center, Holon, Israel. michalkovo@gmail.com

Objective:
Our objective was to investigate the placental component in early- and late-onset fetal growth restriction (FGR) compared to placentas from neonates appropriate for gestational age (AGA).
Study Design:
Placentas from normotensive women who gave birth at 24-42 weeks to neonates with a birth-weight below the 10th percentile (FGR group), or to healthy AGA neonates (AGA group), were analyzed. Placental lesions were classified to lesions related to maternal underperfusion, lesions consistent with fetal thrombo-occlusive disease and inflammatory lesions. Findings were compared between patients who delivered ≤ 34 weeks (early-onset FGR) or >34 weeks (late-onset FGR) and controls with AGA neonates.
Results:
The early-onset FGR group (n = 24) had a higher rate of placental vascular lesions related to maternal underperfusion than the late-FGR group (n = 334) (41.7% vs. 8.7%, P < 0.001) and more villous lesions related to maternal underperfusion than the preterm AGA group (n = 68) (70.8% vs. 5.9%, P < 0.001). The late-onset FGR group had more placental villous lesions related to maternal underperfusion (57% vs. 19% P < 0.001) and more lesions consistent with fetal thrombo-occlusive disease (26.3% vs. 8.5%, P < 0.001) than the term AGA group (n = 153).
Conclusion:
Early- and late-onset FGR have different placental pathology compared with AGA controls, suggesting that a combination of fetal and maternal vascular compromise is more dominant in the late-onset FGR, rather than more severe maternal vascular compromise in early-onset FGR.

Related Concept Videos
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:07
Teratogenicity
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:24
Regulation of Angiogenesis and Blood Supply
 01:07
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...