Related Experiment Video
Updated: May 14, 2026
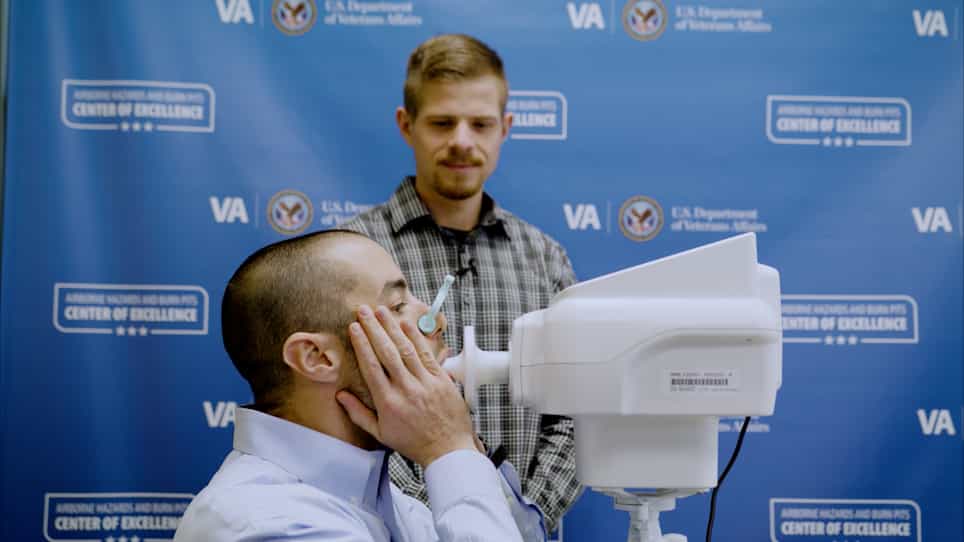
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
A comparison of inspiratory airflow dynamics during sleep between upper airway resistance syndrome patients and
Avram R Gold1, Joan E Broderick, Morris S Gold
1Division of Pulmonary/Critical Care/Sleep Medicine, Stony Brook University School of Medicine, Stony Brook, NY, 11794, USA, avram.gold@va.gov.

Objectives:
A test of the hypothesis that upper airway resistance syndrome (UARS) patients have an increased prevalence of inspiratory airflow limitation (IFL) during sleep compared to healthy controls.
Methods:
We compared inspiratory airflow dynamics during sleep between 12 UARS patients (nine females and three males) and 12 healthy controls matched for age, gender and obesity with maximal age limited at 45 years. A standard clinical polysomnogram (airflow measured with a nasal/oral pressure catheter) was performed to assess the impact of SDB on the participants' natural sleep. A second full-night polysomnogram with a pneumotachograph and a supraglottic pressure catheter to measure airflow and effort was performed to compare the maximal inspiratory airflow and effort and the percentage of flow-limited breaths during supine, continuous stage 2 sleep between groups.
Results:
During clinical polysomnography, UARS participants did not differ significantly from controls in sleep architecture or fragmentation. We observed a small difference in apnea hypopnea index between UARS participants and controls (1.6 ± 1.9 vs. 0.4 ± 0.3, respectively; p = 0.035). During supine, continuous stage 2 sleep, 64.2 % (35.8; mean (SD)) of UARS participants' breaths were flow-limited compared with 34.0 % (39.3) of controls' breaths (p = 0.06). The groups did not differ in maximal inspiratory airflow or inspiratory effort.
Conclusions:
Our findings indicate a less-than-robust difference in respiratory parameters during sleep between UARS patients and healthy controls and no difference in standard sleep parameters or sleep fragmentation. We consider a pathophysiology of UARS that incorporates these findings.
More Related Videos
 07:45
Minimally Invasive Murine Laryngoscopy for Close-Up Imaging of Laryngeal Motion During Breathing and Swallowing
Published on: December 1, 2023
 07:54
Drug-Induced Sleep Endoscopy (DISE) with Target Controlled Infusion (TCI) and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:26
Respiratory Volumes and Capacities I
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...