Related Experiment Video
Updated: May 14, 2026
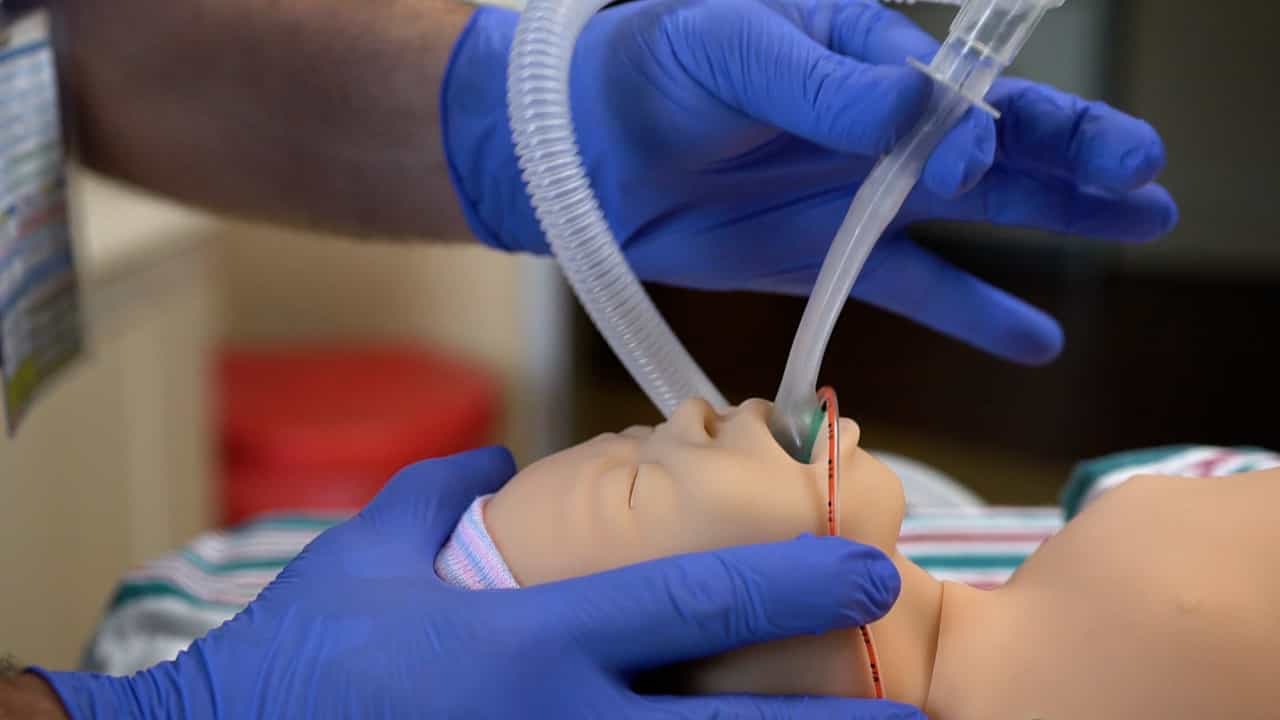

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Children born small for gestational age (SGA)
A Jancevska1, V Tasic, N Damcevski
1Medical Faculty Skopje, R. Macedonia.

Insights
Small for gestational age (SGA) newborns face significant health risks and may experience long-term growth issues. Growth hormone treatment is considered for SGA children over 4 years old who don't achieve catch-up growth.
Area of Science:
- Pediatrics
- Neonatology
- Endocrinology
Background:
- Small for gestational age (SGA) describes newborns with birth weight and/or length below two standard deviations for their gestational age and sex.
- Approximately 5% of newborns are classified as SGA, with diverse causative factors including maternal, placental, fetal, metabolic, and genetic origins.
- SGA infants are susceptible to immediate neonatal complications such as hypoglycemia, hypercoagulability, and necrotizing enterocolitis.
Purpose of the Study:
- To outline the risks and long-term implications associated with being small for gestational age.
- To identify potential interventions for SGA children experiencing growth failure.
Main Methods:
- Review of existing literature on SGA definitions, causes, neonatal risks, and long-term outcomes.
- Analysis of criteria for considering growth hormone (GH) treatment in SGA children.
Main Results:
- SGA children face increased risks of neonatal morbidities and may not achieve spontaneous catch-up growth.
- Around 10% of SGA children remain short into adulthood, exhibiting a higher incidence of metabolic syndrome, cardiovascular disease, and osteoporosis.
- SGA children over 4 years old with persistent short stature (height ≥ -2.5 SDS) and no catch-up growth are candidates for GH therapy.
Conclusions:
- SGA is a significant condition with potential for severe neonatal complications and lasting health consequences.
- Early identification and intervention, including growth hormone therapy for eligible children, are crucial for managing SGA outcomes.
Abstract:
SGA (small for gestational age) is a child born with birth weight and/or length (BW/BL) under two standard deviations (2 SDS) for the gestational age and sex of the population. ~5% of all newborn children are SGA. A broad spectrum of factors are found to be causative: maternal, placental, foetal, metabolic, and genetic. In the newborn period the SGA children are at greater risk of life-threatening conditions: hypoglycaemia, hypercoagulability, necrotic enterocolitis, direct hyperbilirubinemia, hypotension, etc. Approximately 10 percent of SGA children do not achieve catch-up growth and remain short (≥-2 SDS) into adulthood. SGA people have an increased incidence of metabolic syndrome, coronary artery disease, stroke, low bone density and osteoporosis. SGA children aged more than 4 years with no evidence of spontaneous catch-up and with a height≥2.5 SD are considered for growth hormone (GH) treatment.

Related Concept Videos
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:07
Teratogenicity
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:10
Nature and Nurture
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption