
Transfer of doxazosin into breast milk
Berit Packert Jensen1, Judith Maree Dalrymple, Evan James Begg
1Department of Medicine, University of Otago, Christchurch, New Zealand.

To the best of our knowledge, there have been no published studies of doxazosin transfer into human milk. In rats, milk concentrations twentyfold higher than in plasma have been reported. Based on these animal data, some references advise to avoid breastfeeding during doxazosin therapy. However, the physicochemical properties of doxazosin suggest low transfer into human milk. A 37-year-old breastfeeding woman who was administered doxazosin 4 mg daily for 2 doses was studied. Doxazosin concentrations in milk and plasma were measured by liquid chromatography-tandem mass spectrometry (LC-MS/MS). The milk/plasma area under the concentration-time curve (AUC0-18 hours) ratio was 0.1. This finding is consistent with what could be predicted based on the physicochemical properties of doxazosin. The average and maximum milk concentrations were 2.9 and 4.2 µg/L. These values correspond to estimated relative infant doses of 0.06% and 0.09%, respectively, assuming standard infant milk intake. These values are well below the generally accepted cutoff of 10% for predicting safety during breastfeeding. A low relative infant dose of < 0.1% suggests that maternal doxazosin therapy may be compatible with breastfeeding after careful individual risk-benefit analysis.
To the best of our knowledge, there have been no published studies of doxazosin transfer into human milk. In rats, milk concentrations twentyfold higher than in plasma have been reported. Based on these animal data, some references advise to avoid breastfeeding during doxazosin therapy. However, the physicochemical properties of doxazosin suggest low transfer into human milk. A 37-year-old breastfeeding woman who was administered doxazosin 4 mg daily for 2 doses was studied. Doxazosin concentrations in milk and plasma were measured by liquid chromatography-tandem mass spectrometry (LC-MS/MS). The milk/plasma area under the concentration-time curve (AUC0-18 hours) ratio was 0.1. This finding is consistent with what could be predicted based on the physicochemical properties of doxazosin. The average and maximum milk concentrations were 2.9 and 4.2 µg/L. These values correspond to estimated relative infant doses of 0.06% and 0.09%, respectively, assuming standard infant milk intake. These values are well below the generally accepted cutoff of 10% for predicting safety during breastfeeding. A low relative infant dose of < 0.1% suggests that maternal doxazosin therapy may be compatible with breastfeeding after careful individual risk-benefit analysis.

Related Concept Videos
 01:23
Nonlinear Pharmacokinetics: Dependence of Elimination Half-Life and Dose Clearance
A study on guinea pigs examined the...
 01:10
Drug Excretion: Miscellaneous Routes
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:22
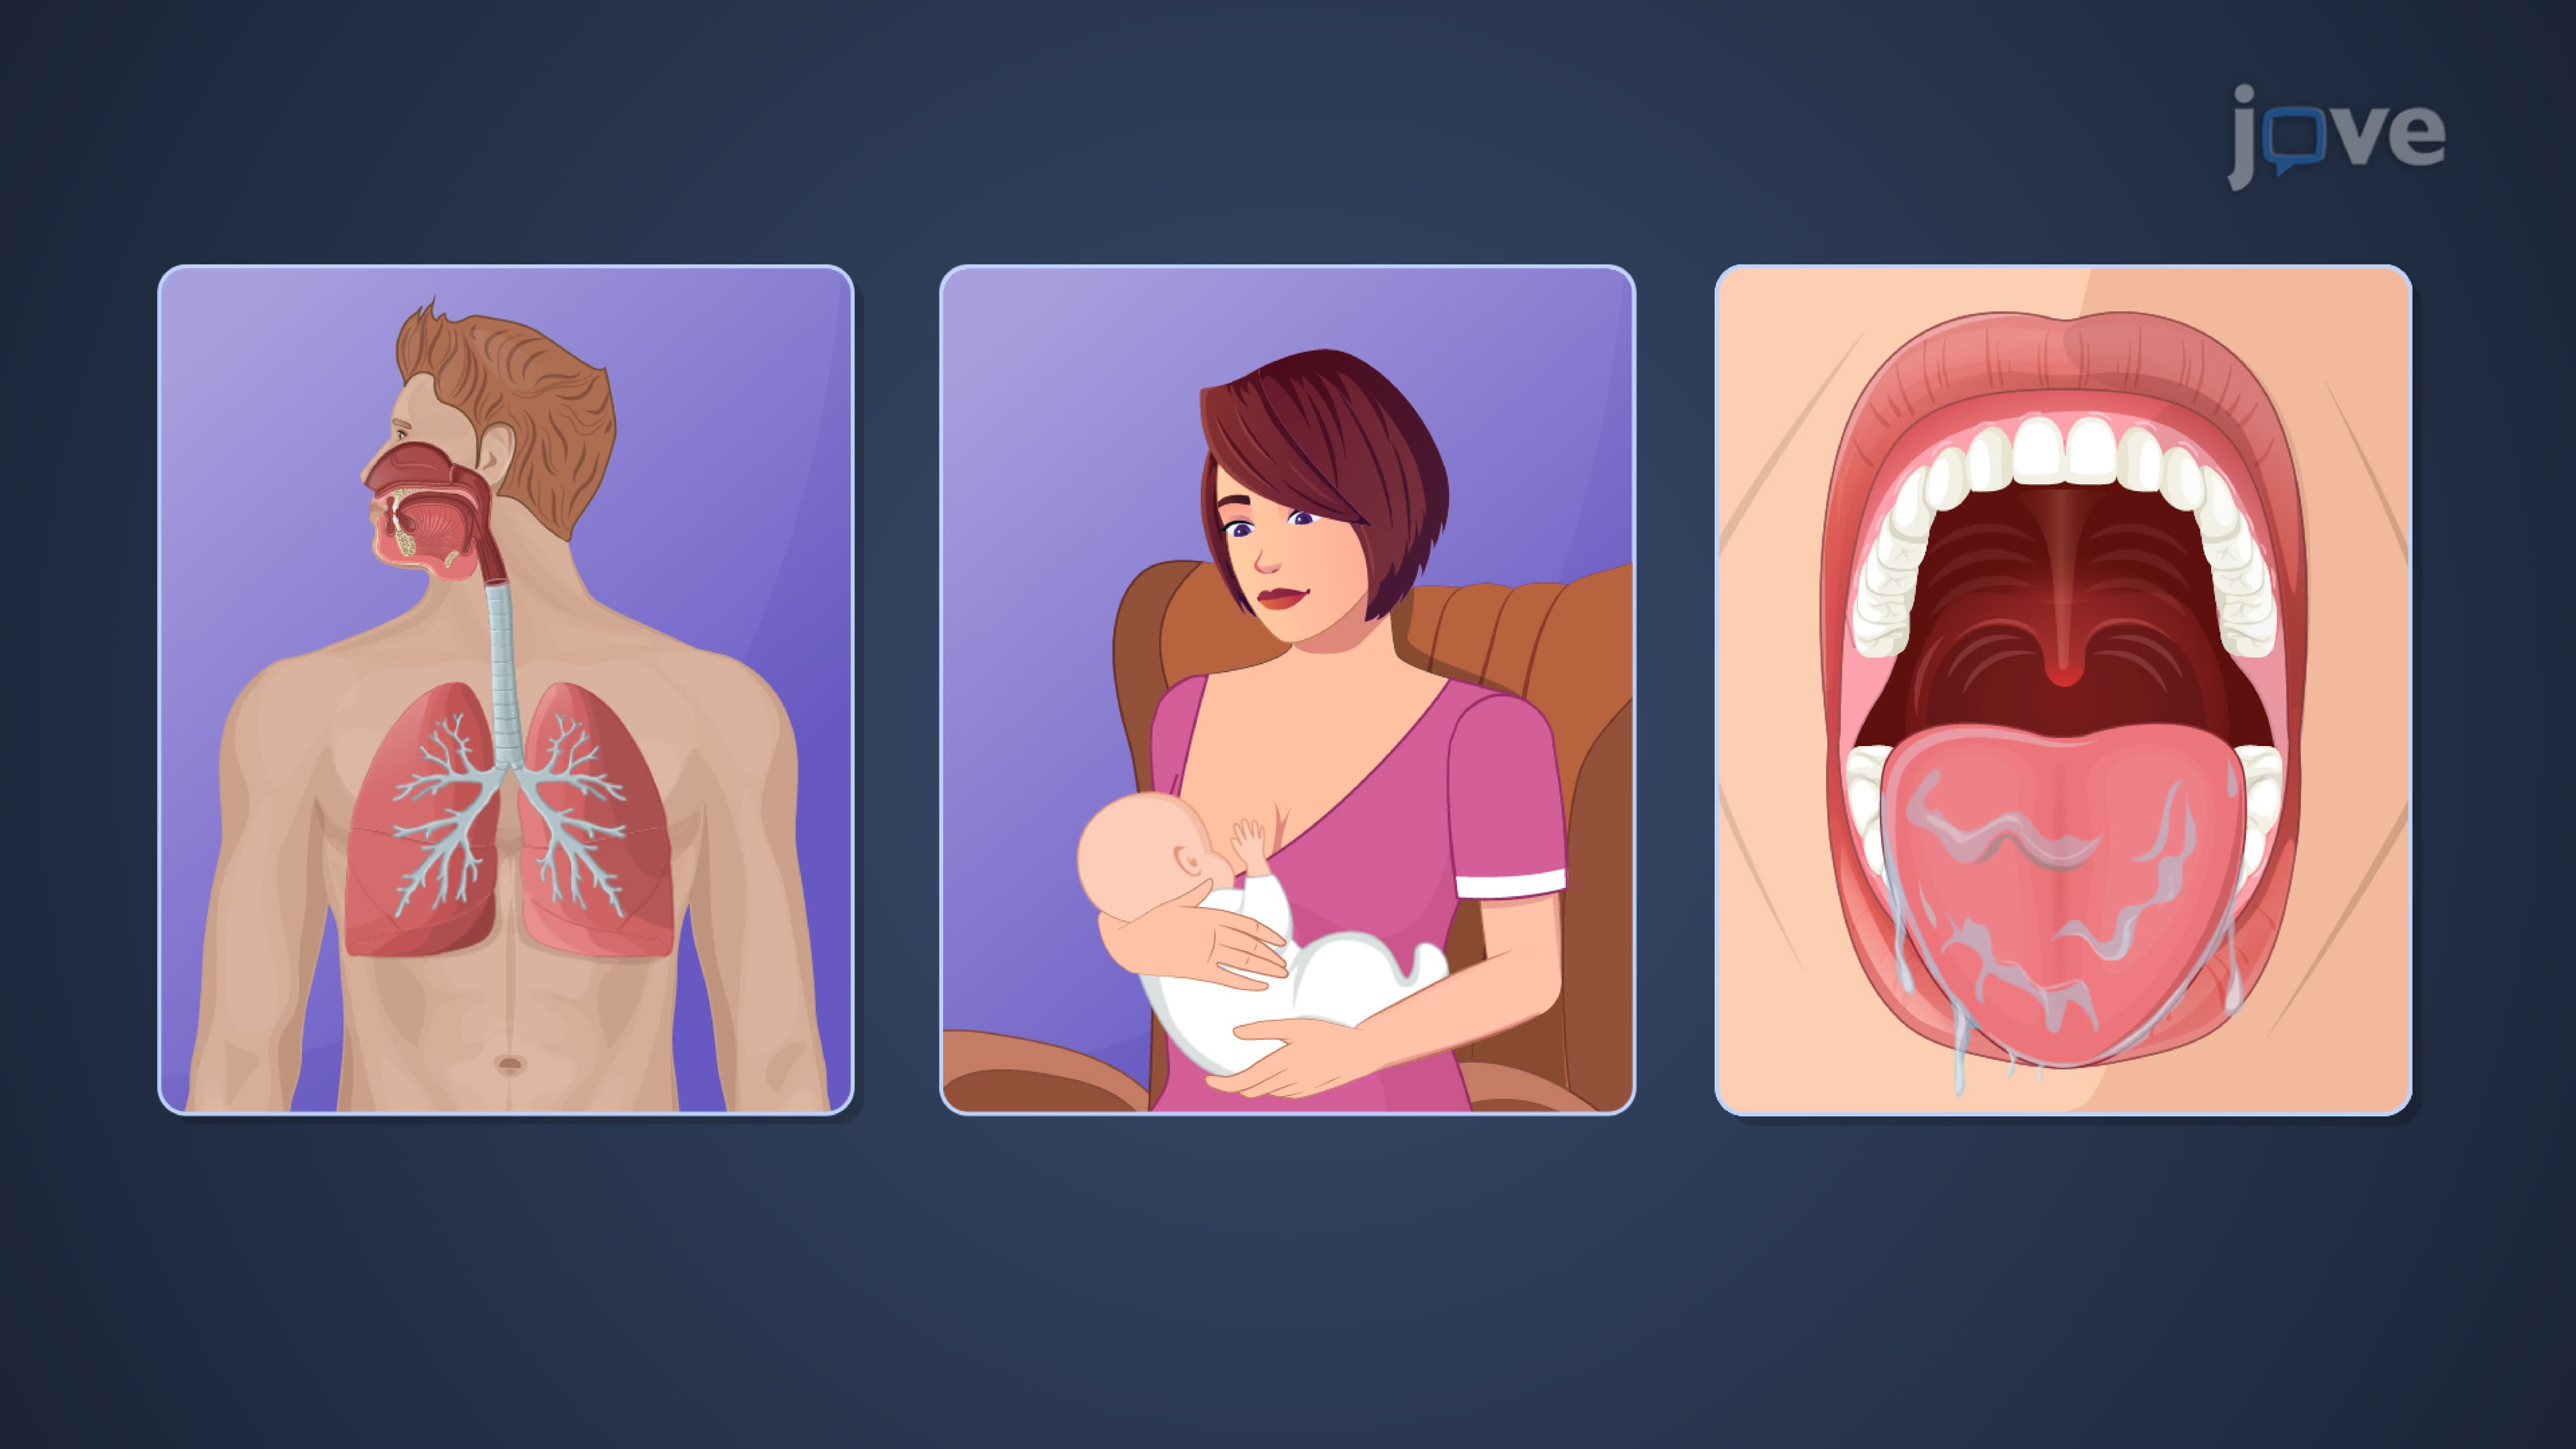
Drug Excretion: Pulmonary and Glandular Routes
Drugs can also be excreted in breast milk, which is crucial for breastfeeding infants. The process...
 01:29
Drug Dosing: Infants and Children
 01:25
Pharmacokinetics: Drug–Drug Interactions