Related Experiment Video
Updated: May 13, 2026
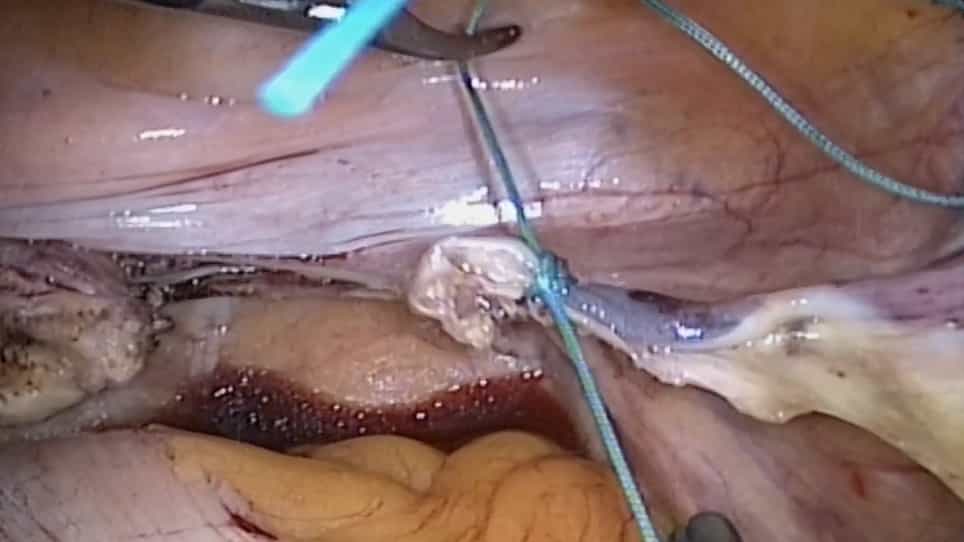

Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Pelvic floor trauma in childbirth
1Sydney Medical School Nepean, University of Sydney, Penrith, NSW 2750, Australia. hpdietz@bigpond.com

The investigation of female pelvic floor function and anatomy is moving from the fringes to the mainstream of urogynaecology and female urology, and it is becoming increasingly relevant for obstetrics. We are coming to realise that pelvic floor trauma in labour is common, usually overlooked, and a major factor in the causation of pelvic organ prolapse. Modern imaging methods such as magnetic resonance and 3D/4D ultrasound have enabled us to diagnose such trauma reliably and accurately, most commonly in the form of an avulsion of the puborectalis muscle; that is, a disconnection of the muscle from its insertion on the os pubis. Such damage to the levator muscle is macroscopically evident and can also be palpated, a skill that is available to every clinician, requiring neither investment nor specialised equipment. In this review, I will describe pelvic floor assessment by palpation and ultrasound and illustrate the commonest abnormalities and their clinical consequences. This paper will not focus on magnetic resonance imaging due to technical restrictions, cost and access issues in most jurisdictions, and because several papers have recently shown that ultrasound is at least as effective in diagnosing such trauma. Anal sphincter trauma is generally well covered in the literature and hence not subject of this review.
The investigation of female pelvic floor function and anatomy is moving from the fringes to the mainstream of urogynaecology and female urology, and it is becoming increasingly relevant for obstetrics. We are coming to realise that pelvic floor trauma in labour is common, usually overlooked, and a major factor in the causation of pelvic organ prolapse. Modern imaging methods such as magnetic resonance and 3D/4D ultrasound have enabled us to diagnose such trauma reliably and accurately, most commonly in the form of an avulsion of the puborectalis muscle; that is, a disconnection of the muscle from its insertion on the os pubis. Such damage to the levator muscle is macroscopically evident and can also be palpated, a skill that is available to every clinician, requiring neither investment nor specialised equipment. In this review, I will describe pelvic floor assessment by palpation and ultrasound and illustrate the commonest abnormalities and their clinical consequences. This paper will not focus on magnetic resonance imaging due to technical restrictions, cost and access issues in most jurisdictions, and because several papers have recently shown that ultrasound is at least as effective in diagnosing such trauma. Anal sphincter trauma is generally well covered in the literature and hence not subject of this review.

Related Concept Videos
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:29
Herniated Intervertebral Disc l: Introduction
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: