Related Experiment Video
Updated: May 13, 2026
A Reference Broth Microdilution Method for Dalbavancin In Vitro Susceptibility Testing of Bacteria that Grow Aerobically
Published on: September 9, 2015
Nephrotoxicity in patients with vancomycin trough concentrations of 15-20 μg/ml in a pediatric intensive care unit
Jeffrey J Cies1, Venkat Shankar
1St. Christopher's Hospital for Children, Philadelphia, PA 19134, USA. jeffrey.cies@gmail.com

Study Objectives:
To determine if a higher serum vancomycin (Vt) target trough concentration of 15-20 μg/ml or greater is associated with an increased rate of vancomycin-induced nephrotoxicity in children admitted to a pediatric intensive care unit (PICU), and to determine risk factors for developing vancomycin-induced nephrotoxicity.
Design:
Retrospective cohort study.
Setting:
A PICU within a freestanding tertiary care pediatric hospital.
Patients:
A total of 113 patients received vancomycin for at least 48 hours The high-trough cohort (H group [57 patients]) received vancomycin therapy between November 2008 and June 2009 for pneumonia, bacteremia, or meningitis that was managed by a clinical pharmacist who directed dosage adjustments driven by a novel algorithm to attain a target Vt concentration of 15-20 μg/ml or greater; the control group (C group [56 patients]) received vancomycin therapy during the preceding 10 months (between January and October 2008) for pneumonia or meningitis using standard dosing guidelines with lower target Vt concentrations of 5-15 μg/ml.
Measurements And Main Results:
The highest grade of renal dysfunction according to the Common Terminology Criteria for Adverse Events criteria, v.4.0, was recorded. The mean ± SD Vt was 17.8 ± 3.1 and 8.4 ± 3.1 in the H and C groups, respectively (p<0.001). The rate of grade 1 nephrotoxicity was not significantly different between groups (8.8% in the H group vs 5.4% in the C group; p=0.72). No patient in either group developed a higher grade of renal dysfunction. In the univariable analysis, duration of vancomycin therapy (odds ratio [OR] 1.32, 95% confidence interval [CI] 1.01-1.02, p=0.003), use of extracorporeal membrane oxygenation (OR 1.32, 95% CI 1.13-1.75, p=0.003), and vasopressor use (OR 1.41, 95% CI 1.11-1.37, p<0.001) were associated with nephrotoxicity. In the multivariable analysis, vasopressor use (OR 11.1, 95% CI 1.4-85, p=0.021) and duration of therapy were associated with nephrotoxicity (OR 1.19, 95% CI 1.04-1.37, p=0.011).
Conclusion:
Our observations suggest that maintaining Vt concentrations 15 µg/ml or greater is not associated with an increased rate of nephrotoxicity in a PICU population.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:20
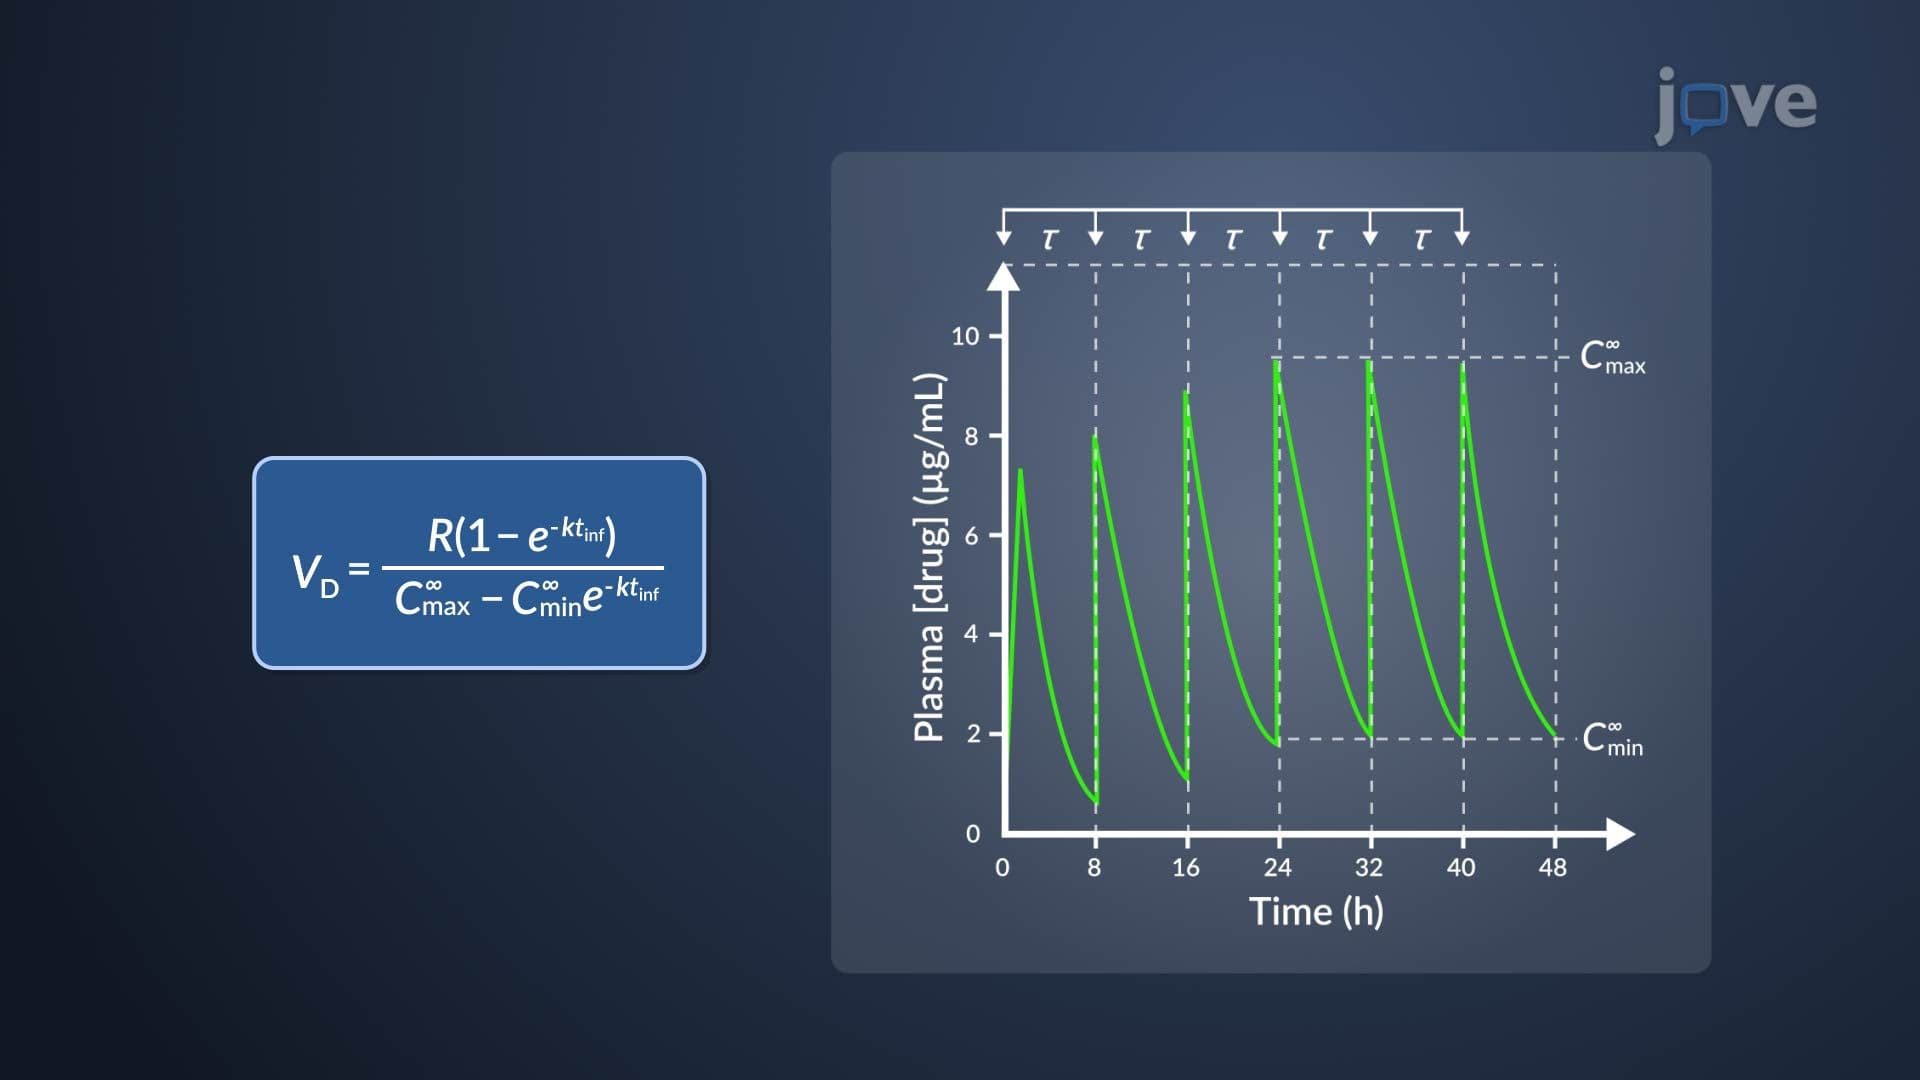
Estimation of k and VD of Aminoglycosides
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:15
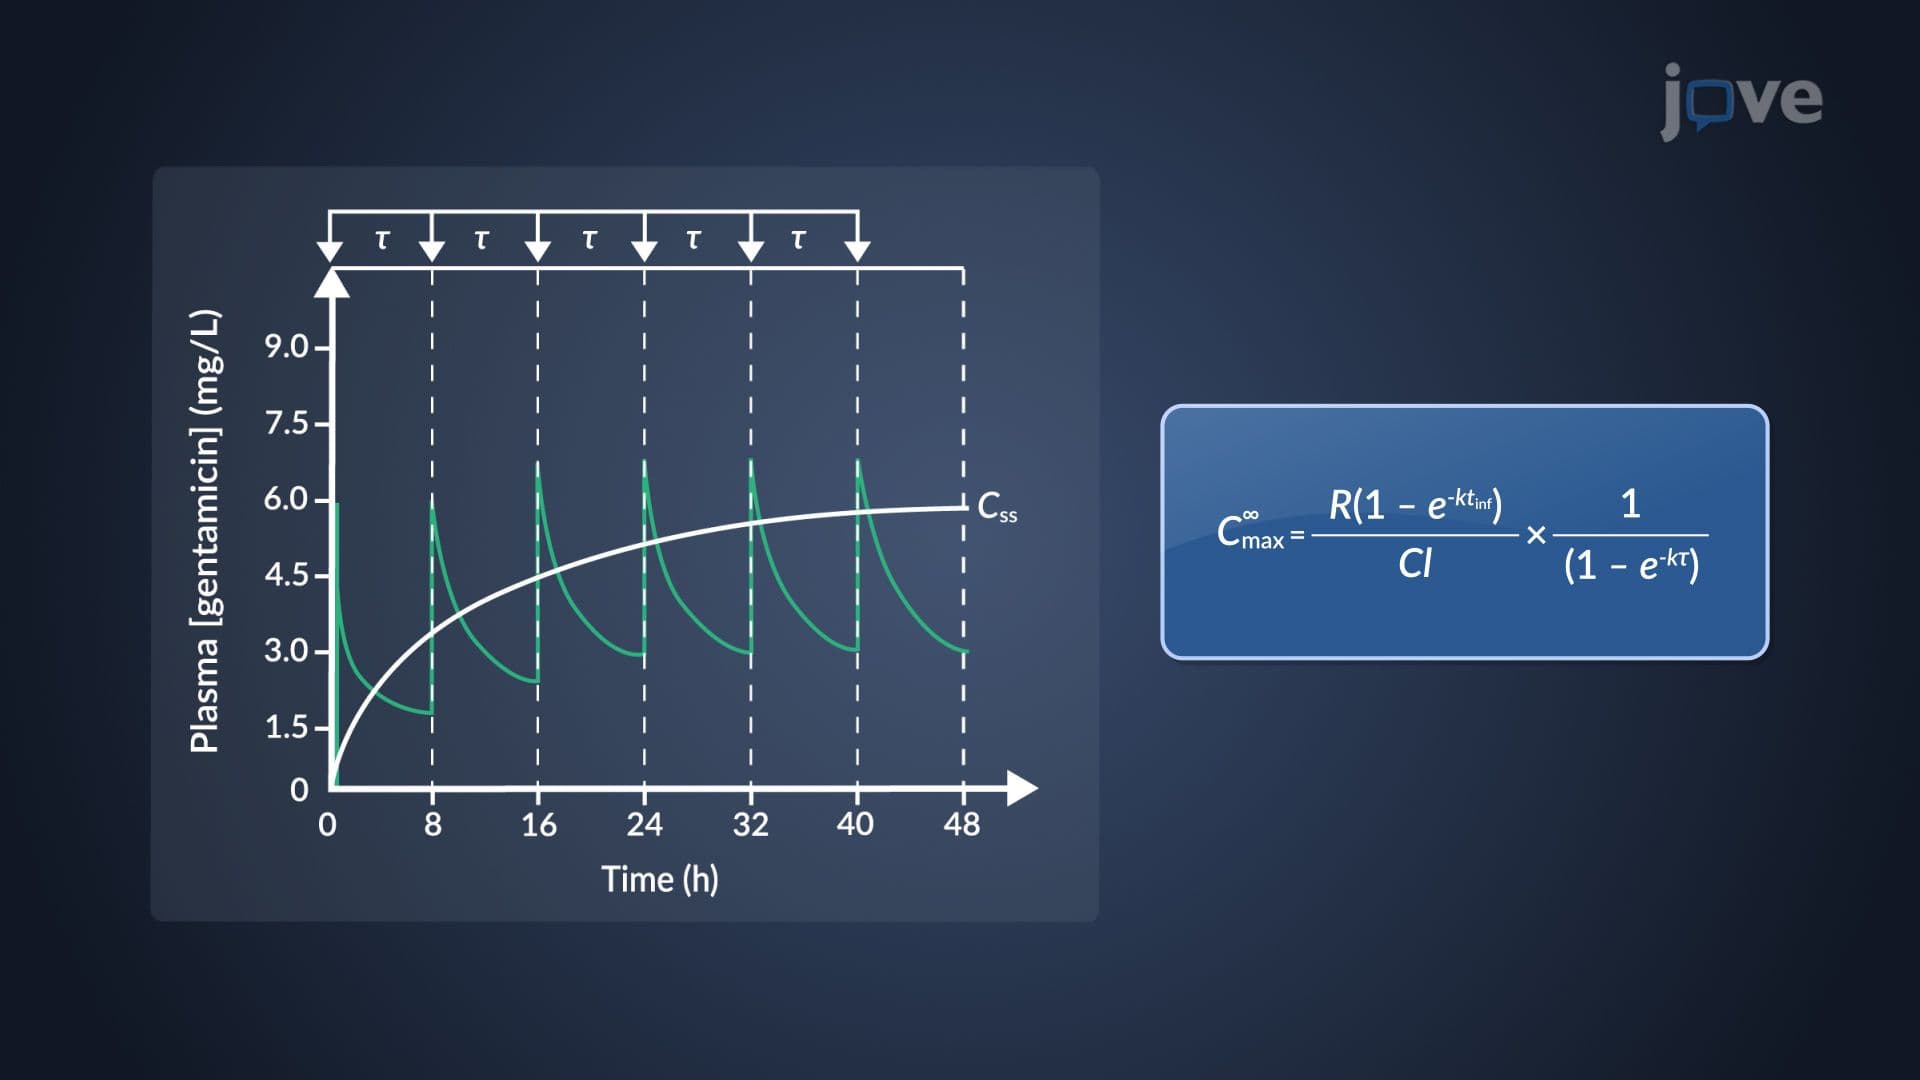
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism