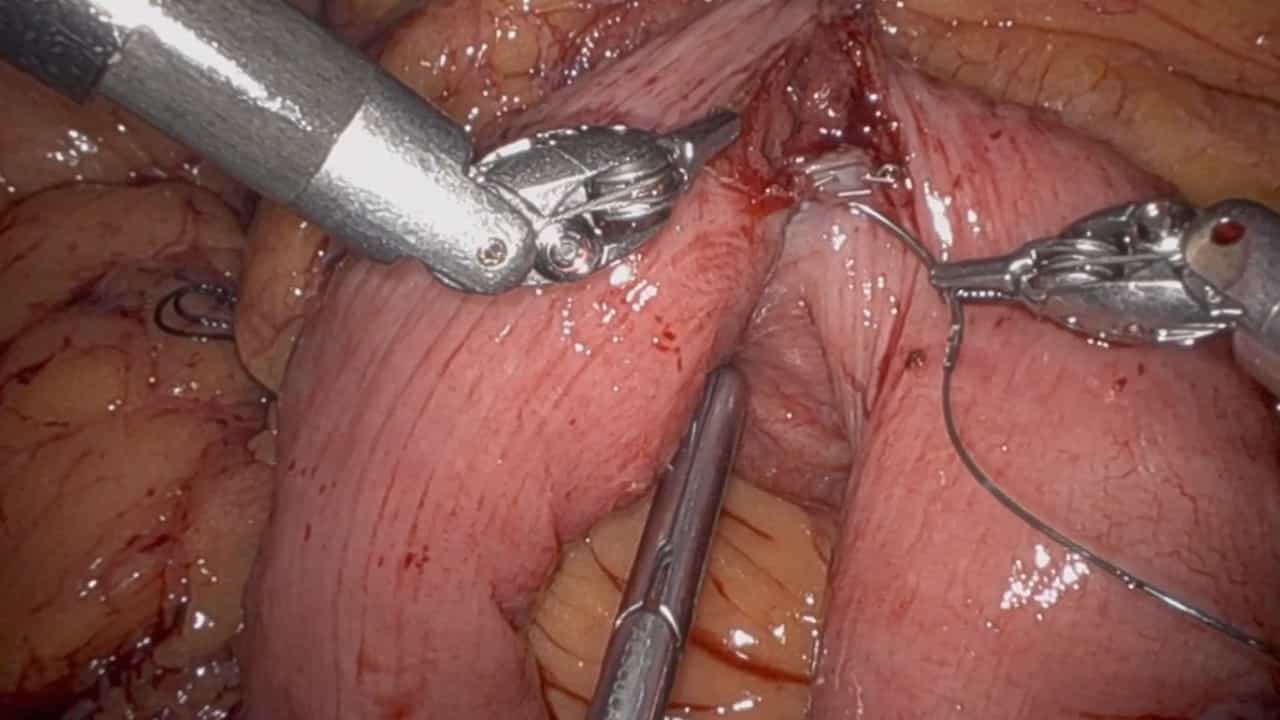
Rendezvous ductoplasty for biliary anastomotic stricture after living-donor liver transplantation
Shohei Yoshiya1, Ken Shirabe, Yoshihiro Matsumoto
1Department of Surgery and Science, Graduate School of Medical Sciences, Kyushu University, Fukuoka, Japan. yoshiya@surg2.med.kyushu-u.ac.jp

Background:
Biliary anastomotic stricture (BAS) after living-donor liver transplantation (LDLT) is difficult to manage. We used rendezvous ductoplasty (RD) to treat BAS after LDLT.
Methods:
We retrospectively analyzed 53 patients with BAS after adult-to-adult LDLT with duct-to-duct biliary reconstruction.
Results:
BAS was classified according to endoscopic retrograde cholangiography findings after normal-pressure contrast injection: type I (n=32) in which the stricture was visualized; type II (n=13) in which the common hepatic duct and graft intrahepatic ducts were visualized, but the stricture was not visualized; or type III (n=8) in which the stricture and graft intrahepatic ducts were not visualized. In right lobe grafts, types II and III occurred more frequently than type I (P=0.0023). Type I had significantly shorter cold ischemic time (76±11 vs. 118±12 min; P=0.0155) and warm ischemic time (38±2 vs. 49±3 min; P=0.0069) than types II and III. The number of attempts to pass the guidewire through the stricture was significantly lower in type I (1.2±0.2 attempts) than type II (2.2±0.2 attempts; P=0.0018) or type III (2.8±0.3 attempts; P<0.0001). The treatment success rate was 78.1% for type I, 38.5% for type II, and 50.0% for type III (P=0.0282). RD was the first successful treatment in a higher proportion of types II and III patients than type I patients (66.7% vs. 6.3%; P<0.0001). Cumulative treatment success rates were not significantly different between the RD and the non-RD groups (P=0.0920).
Conclusions:
RD was a useful treatment for difficult cases of BAS after LDLT and achieved successful outcomes.