Related Experiment Video
Updated: May 12, 2026
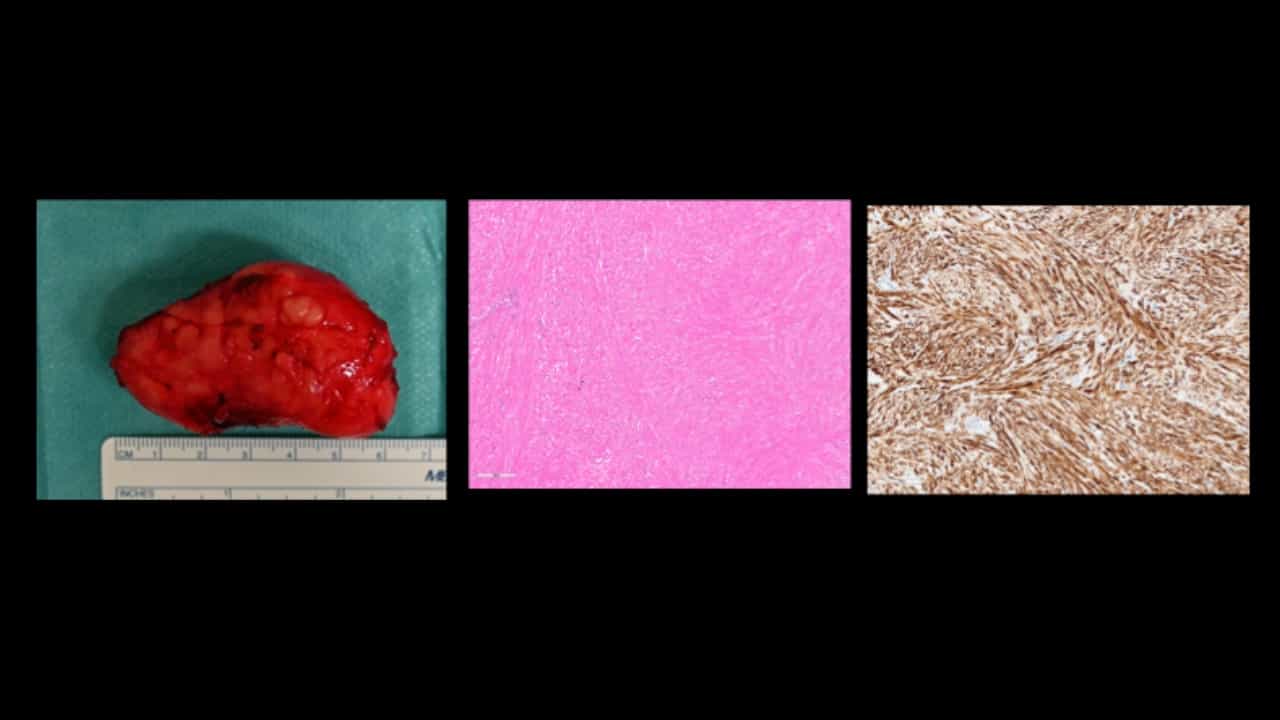
Robotic Enucleation of Esophageal Leiomyoma
Published on: February 20, 2026
Endoscopic and surgical resection of T1a/T1b esophageal neoplasms: a systematic review
George Sgourakis1, Ines Gockel, Hauke Lang
1Department of General and Abdominal Surgery, Johannes Gutenberg University Hospital of Mainz, D-55131 Mainz, Germany. ggsgourakis@yahoo.gr

Aim:
To investigate potential therapeutic recommendations for endoscopic and surgical resection of T1a/T1b esophageal neoplasms.
Methods:
A thorough search of electronic databases MEDLINE, Embase, Pubmed and Cochrane Library, from 1997 up to January 2011 was performed. An analysis was carried out, pooling the effects of outcomes of 4241 patients enrolled in 80 retrospective studies. For comparisons across studies, each reporting on only one endoscopic method, we used a random effects meta-regression of the log-odds of the outcome of treatment in each study. "Neural networks" as a data mining technique was employed in order to establish a prediction model of lymph node status in superficial submucosal esophageal carcinoma. Another data mining technique, the "feature selection and root cause analysis", was used to identify the most important predictors of local recurrence and metachronous cancer development in endoscopically resected patients, and lymph node positivity in squamous carcinoma (SCC) and adenocarcinoma (ADC) separately in surgically resected patients.
Results:
Endoscopically resected patients: Low grade dysplasia was observed in 4% of patients, high grade dysplasia in 14.6%, carcinoma in situ in 19%, mucosal cancer in 54%, and submucosal cancer in 16% of patients. There were no significant differences between endoscopic mucosal resection and endoscopic submucosal dissection (ESD) for the following parameters: complications, patients submitted to surgery, positive margins, lymph node positivity, local recurrence and metachronous cancer. With regard to piecemeal resection, ESD performed better since the number of cases was significantly less [coefficient: -7.709438, 95%CI: (-11.03803, -4.380844), P < 0.001]; hence local recurrence rates were significantly lower [coefficient: -4.033528, 95%CI: (-6.151498, -1.915559), P < 0.01]. A higher rate of esophageal stenosis was observed following ESD [coefficient: 7.322266, 95%CI: (3.810146, 10.83439), P < 0.001]. A significantly greater number of SCC patients were submitted to surgery (log-odds, ADC: -2.1206 ± 0.6249 vs SCC: 4.1356 ± 0.4038, P < 0.05). The odds for re-classification of tumor stage after endoscopic resection were 53% and 39% for ADC and SCC, respectively. Local tumor recurrence was best predicted by grade 3 differentiation and piecemeal resection, metachronous cancer development by the carcinoma in situ component, and lymph node positivity by lymphovascular invasion. With regard to surgically resected patients: Significant differences in patients with positive lymph nodes were observed between ADC and SCC [coefficient: 1.889569, 95%CI: (0.3945146, 3.384624), P < 0.01). In contrast, lymphovascular and microvascular invasion and grade 3 patients between histologic types were comparable, the respective rank order of the predictors of lymph node positivity was: Grade 3, lymphovascular invasion (L+), microvascular invasion (V+), submucosal (Sm) 3 invasion, Sm2 invasion and Sm1 invasion. Histologic type (ADC/SCC) was not included in the model. The best predictors for SCC lymph node positivity were Sm3 invasion and (V+). For ADC, the most important predictor was (L+).
Conclusion:
Local tumor recurrence is predicted by grade 3, metachronous cancer by the carcinoma in-situ component, and lymph node positivity by L+. T1b cancer should be treated with surgical resection.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...