Related Experiment Video
Updated: May 12, 2026
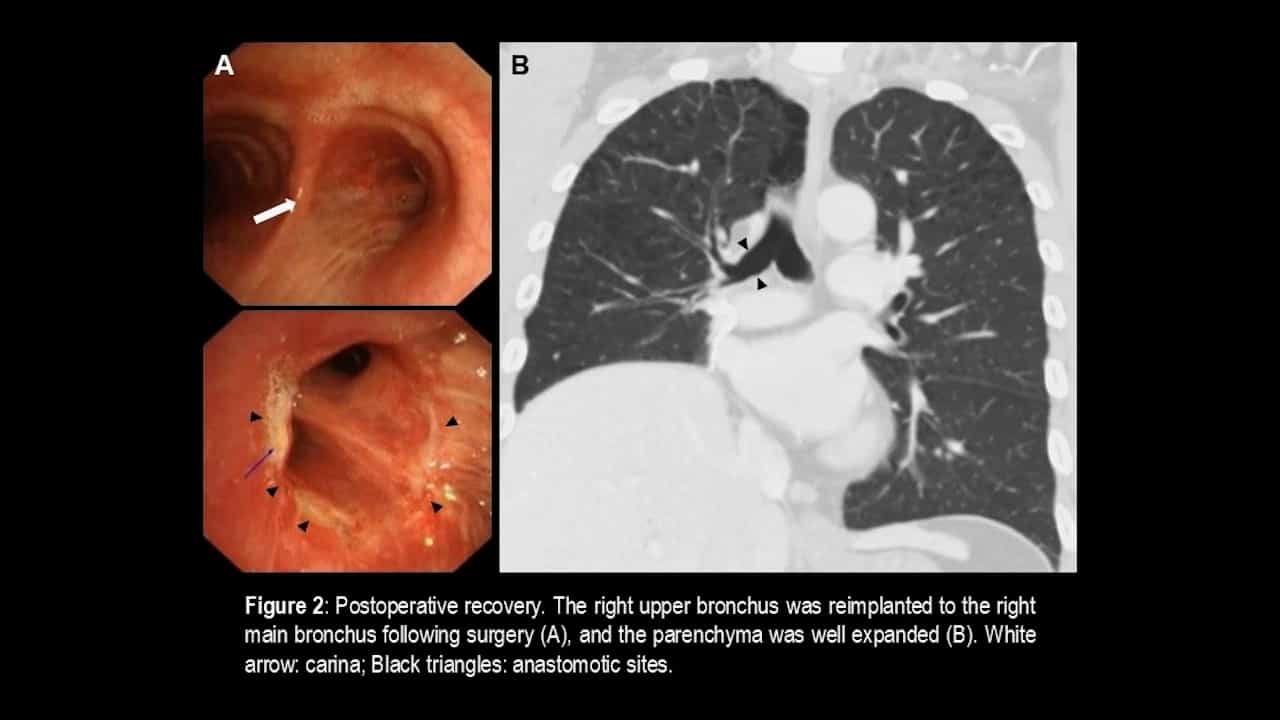
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Response to sorafenib in a pediatric patient with papillary thyroid carcinoma with diffuse nodular pulmonary disease
Pallavi Iyer1, Jennifer L R Mayer, Jeffrey M Ewig
11 Endocrinology & Diabetes, All Children's Specialty Physicians, All Children's Hospital/Johns Hopkins Medicine , St. Petersburg, Florida.

Background:
Papillary thyroid cancer (PTC) presents with local and distant metastases more frequently in children than in adults. However, hypoxemia secondary to pulmonary metastases has not been reported in the literature. Sorafenib is a small-molecule multikinase inhibitor used in radioactive iodine ((131)I)-refractive papillary thyroid carcinoma.
Patient Findings:
An eight-year-old boy presented with fever and hypoxemia and was found to have H1N1 viral pneumonia requiring mechanical ventilation and antiviral and glucocorticoid treatment. After initial improvement, he was readmitted one month later because of persistent hypoxemia. A high-resolution computed tomography of the chest and neck revealed multiple 1-4 mm nodules and necrotic lymph nodes on the right side of the neck. Left lung wedge resection and right deep cervical node biopsies were consistent with PTC. He underwent a total thyroidectomy with a central neck node dissection and postoperatively required prolonged mechanical ventilation. Due to the inability to be weaned from mechanical ventilation, treatment with sorafenib 200 mg daily (10 mg/kg/day, 250 mg/m(2)) was initiated. Eight days thereafter, ventilation support was discontinued and the child was extubated. However, he failed extubation secondary to supraglottic edema, and seven days later tracheostomy was performed. The dosage of sorafenib was increased to 200 mg twice daily (20 mg/kg/day, 500 mg/m(2)). After 52 days of therapy, a repeat computed tomography scan showed reduction in the lung nodule size to 1-2 mm. He underwent (131)I therapy 87 days after sorafenib was started. A post-treatment scan showed extensive uptake throughout the lungs and thyroid bed, supraclavicular nodes, and cervical nodes.
Conclusions:
This is the first reported case of a pediatric patient with respiratory failure possibly secondary to diffuse micronodular PTC requiring mechanical ventilation and subsequent delay in definitive therapy. Sorafenib could be considered for gap therapy when (131)I therapy cannot be administered in a timely manner. Treatment with this multikinase inhibitor does not seem to adversely affect the uptake of (131)I in radiation-naïve patients.
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic sinusitis...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...