Related Experiment Video
Updated: Oct 9, 2026
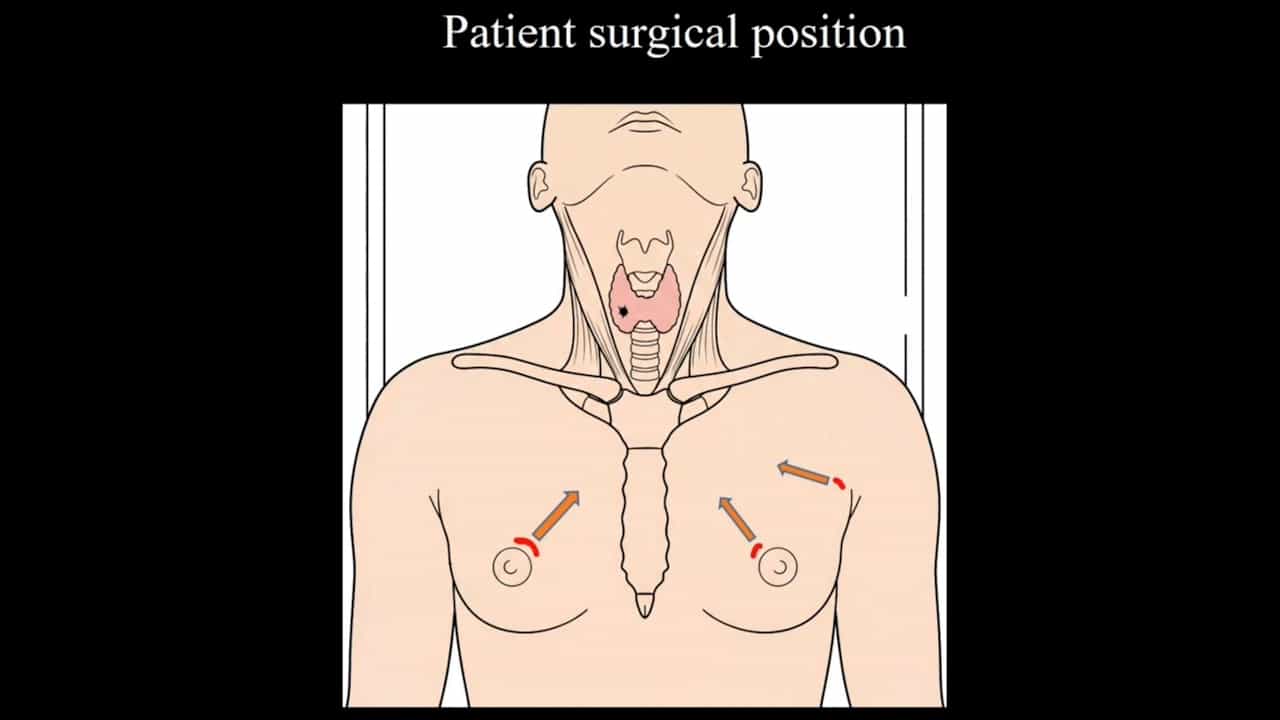

A Novel Contralateral Axillo-Bilateral-Breast Approach for Endoscopic Thyroid Surgery
Published on: July 28, 2026
Changes in Multisystem Morbidity in Thyroid Cancer after the 2015 ATA Guideline: A Nationwide Population-Based
Seong Hee Ahn1,2, Dong Wook Kim3, Jinyoung Kim4
1Division of Endocrinology and Metabolism, Department of Internal Medicine, Ewha Womans University Mokdong Hospital, Ewha Womans University College of Medicine, Seoul, Korea.

Background:
As survivorship has become increasingly important in differentiated thyroid cancer (DTC), the 2015 American Thyroid Association (ATA) guideline introduced a more risk-adapted and less intensive approach to management. However, evidence regarding the association between guideline-driven de-intensification and non-cancer-specific multisystem morbidity remains limited.
Methods:
We conducted a nationwide population-based retrospective cohort study using Korean national claims data and compared patients who underwent total thyroidectomy before (2009-2014, n = 96,776) and after (2016-2021, n = 29,408) the 2015 ATA guideline. Outcome-specific 1:1 propensity score-matched analytic sets were constructed. The primary outcomes were composite cardiovascular/cerebrovascular, composite skeletal, and composite neurocognitive/psychiatric outcomes, as well as all-cause mortality. Secondary analyses examined the individual components of each composite outcome. Time-to-event analyses were performed using multivariable Cox proportional hazards models.
Results:
After matching and adjustment, the postguideline period demonstrated lower risks of composite skeletal outcomes (hazard ratio [HR] = 0.83; confidence interval [CI] 0.69-0.99) and composite neurocognitive/psychiatric outcomes (HR = 0.73; CI 0.69-0.77). Composite cardiovascular/cerebrovascular outcomes did not differ significantly between periods; however, secondary analyses showed lower risks of atrial fibrillation (HR = 0.62; CI 0.50-0.76), myocardial infarction (HR = 0.81; CI 0.66-0.99), and stroke (HR = 0.56; CI 0.49-0.63). All-cause mortality was similar between periods.
Conclusions:
During the post-2015 ATA guideline period, there was a lower burden of non-cancer-specific multisystem morbidity among patients undergoing total thyroidectomy for thyroid cancer. These findings support the relevance of guideline-recommended, risk-adapted de-intensification strategies for improving long-term survivorship outcomes in DTC.
Related Concept Videos
 01:28
Graves' Disease I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction