Hemicrania continua. Unquestionably a trigeminal autonomic cephalalgia
Related Experiment Video
Updated: May 12, 2026
Subcutaneous Trigeminal Nerve Field Stimulation for Refractory Facial Pain
Published on: May 10, 2017
1Hospital Universitário Clementino Fraga Filho, Universidade Federal do Rio de Janeiro, Rio de Janeiro, Brazil.

Insights
Hemicrania continua (HC) is reclassified as a trigeminal autonomic cephalalgia, not a miscellaneous headache. Evidence shows shared clinical features, indomethacin response, and hypothalamic activation with other TACs.
Area of Science:
- Neurology
- Headache Medicine
Background:
- Hemicrania continua (HC) is currently classified under 'other primary headaches' in the International Classification of Headache Disorders.
- Emerging evidence suggests HC shares characteristics with trigeminal autonomic cephalalgias (TACs).
Purpose of the Study:
- To evaluate the evidence supporting the reclassification of Hemicrania continua (HC) as a trigeminal autonomic cephalalgia (TAC).
- To consolidate clinical, therapeutic, and neuroimaging data to support HC's placement within the TAC spectrum.
Main Methods:
- Review of clinical presentations of HC and other TACs (cluster headache, paroxysmal hemicrania, SUNHA).
- Analysis of treatment responses, particularly to indomethacin.
- Examination of neuroimaging findings, focusing on hypothalamic activation patterns.
Main Results:
- HC exhibits a shared clinical profile with TACs: paroxysmal, unilateral, side-locked headaches with ipsilateral autonomic symptoms.
- Indomethacin demonstrates a unique and potent efficacy in HC, mirroring its effect in paroxysmal hemicrania.
- Neuroimaging reveals posterior hypothalamic activation in HC, consistent with other TACs.
Conclusions:
- Hemicrania continua (HC) demonstrates sufficient shared features with cluster headache, paroxysmal hemicrania, and SUNHA to be classified as a trigeminal autonomic cephalalgia.
- The current classification of HC as a miscellaneous primary headache is outdated and does not reflect its underlying pathophysiology.
- HC should be integrated into the spectrum of trigeminal autonomic cephalalgias based on clinical, therapeutic, and neuroimaging evidence.
Abstract:
Hemicrania continua (HC) is a well-known primary headache. The present version of the International Classification of Headache Disorders lists HC in the "other primary headaches" group. However, evidence has emerged demonstrating that HC is a phenotype that belongs to the trigeminal autonomic cephalalgias together with cluster headache, paroxysmal hemicrania (PH), and short-lasting, unilateral neuralgiform headache attacks with conjunctival injection and tearing. This is supported by a common general clinical picture - paroxysmal, fluctuating, unilateral, side-locked headaches located to the ocular, frontal, and/or temporal regions, accompanied by ipsilateral autonomic dysfunctions including for example, tearing and conjunctival injection. Apart from the remarkable clinical similarities, the absolute and incomparable effect of indomethacin in HC parallels the effect of this drug in PH, suggesting a shared core pathogenesis. Finally, neuroimage findings demonstrate a posterior hypothalamic activation in HC similarly to cluster headache, PH, and short-lasting, unilateral neuralgiform headache attacks with conjunctival injection and tearing. Taken together, data indicate that HC is certainly a type of trigeminal autonomic cephalalgia that should no longer be placed in a group of miscellaneous primary headache disorders.

Related Concept Videos
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:26
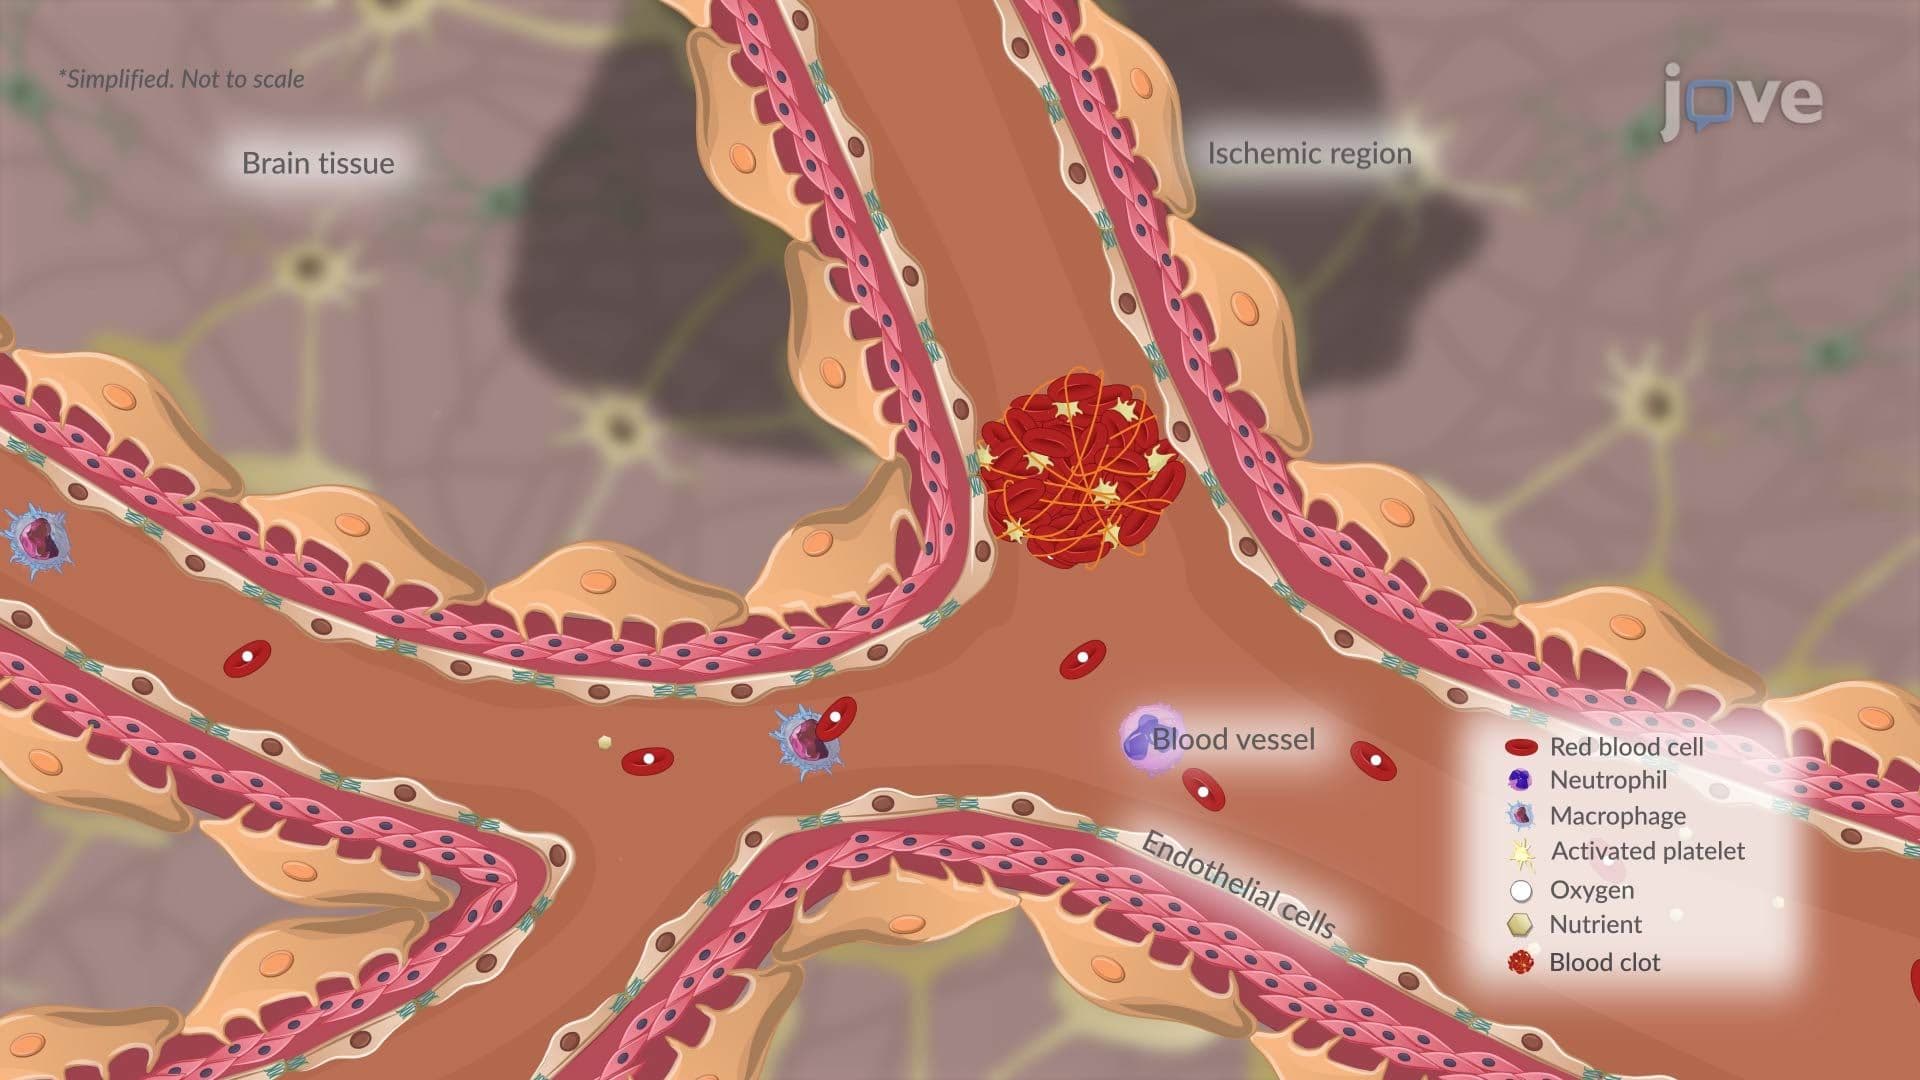
Transient Ischemic Attack l: Introduction
 01:14
Increased Intracranial Pressure l: Introduction
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...