Related Experiment Video
Updated: May 11, 2026
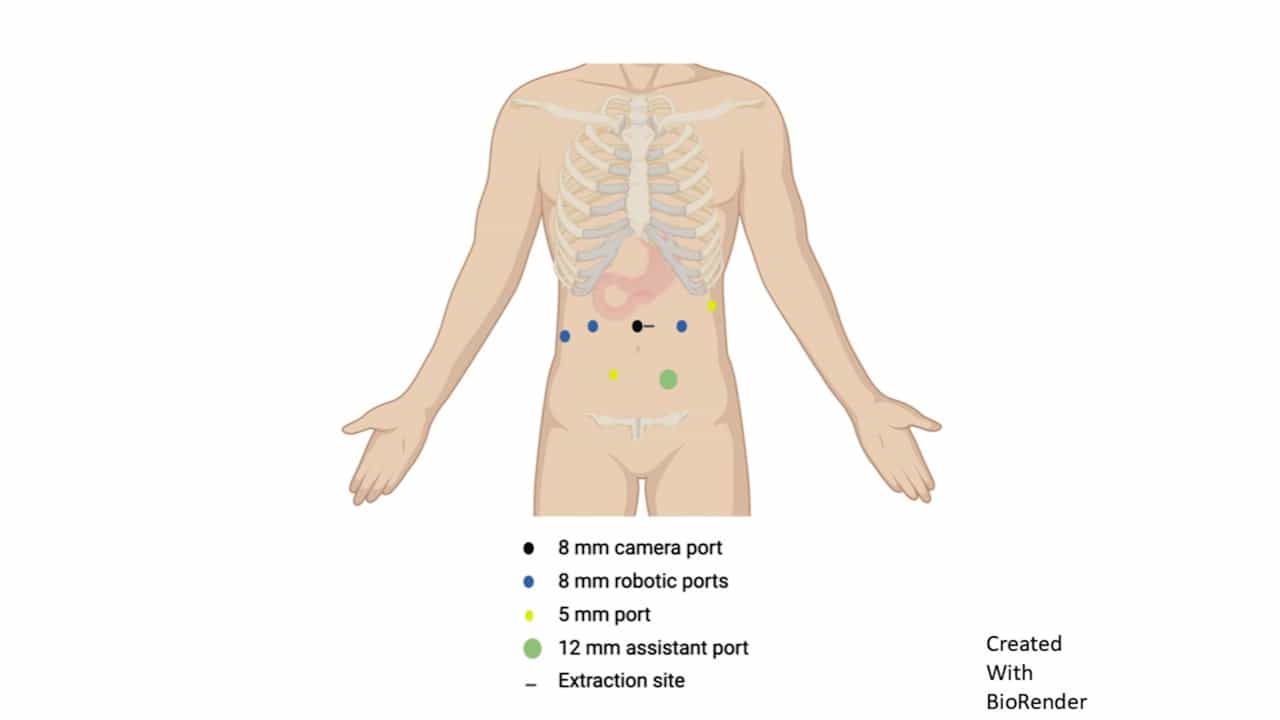

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Gastrointestinal stromal tumour
Heikki Joensuu1, Peter Hohenberger, Christopher L Corless
1Department of Oncology, Helsinki University Central Hospital, Helsinki, Finland. heikki.joensuu@hus.fi

Gastrointestinal stromal tumours (GISTs) are mesenchymal neoplasms that arise in the gastrointestinal tract, usually in the stomach or the small intestine and rarely elsewhere in the abdomen. They can occur at any age, the median age being 60-65 years, and typically cause bleeding, anaemia, and pain. GISTs have variable malignant potential, ranging from small lesions with a benign behaviour to fatal sarcomas. Most tumours stain positively for the mast/stem cell growth factor receptor KIT and anoctamin 1 and harbour a kinase-activating mutation in either KIT or PDGFRA. Tumours without such mutations could have alterations in genes of the succinate dehydrogenase complex or in BRAF, or rarely RAS family genes. About 60% of patients are cured by surgery. Adjuvant treatment with imatinib is recommended for patients with a substantial risk of recurrence, if the tumour has an imatinib-sensitive mutation. Tyrosine kinase inhibitors substantially improve survival in advanced disease, but secondary drug resistance is common.
Gastrointestinal stromal tumours (GISTs) are mesenchymal neoplasms that arise in the gastrointestinal tract, usually in the stomach or the small intestine and rarely elsewhere in the abdomen. They can occur at any age, the median age being 60-65 years, and typically cause bleeding, anaemia, and pain. GISTs have variable malignant potential, ranging from small lesions with a benign behaviour to fatal sarcomas. Most tumours stain positively for the mast/stem cell growth factor receptor KIT and anoctamin 1 and harbour a kinase-activating mutation in either KIT or PDGFRA. Tumours without such mutations could have alterations in genes of the succinate dehydrogenase complex or in BRAF, or rarely RAS family genes. About 60% of patients are cured by surgery. Adjuvant treatment with imatinib is recommended for patients with a substantial risk of recurrence, if the tumour has an imatinib-sensitive mutation. Tyrosine kinase inhibitors substantially improve survival in advanced disease, but secondary drug resistance is common.

