Related Experiment Video
Updated: May 11, 2026
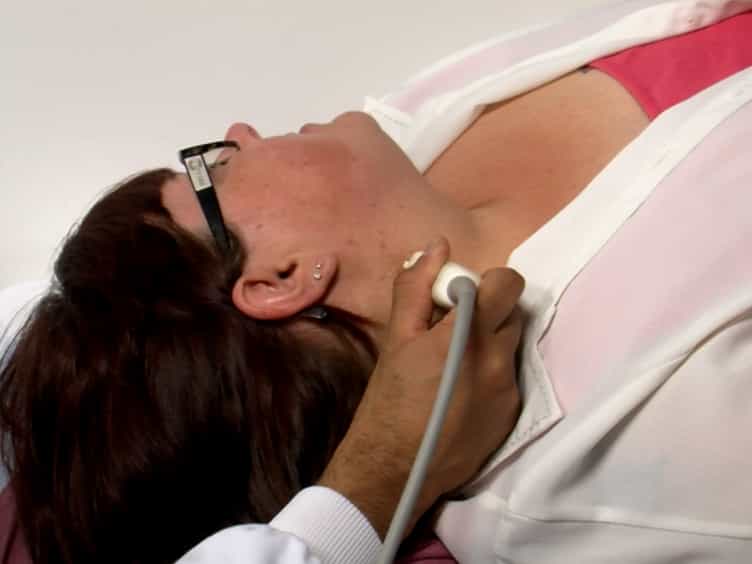

A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Myocardial perfusion and intima-media thickness in patients with subclinical hypothyroidism
M Knapp1, A Lisowska, B Sobkowicz
1Department of Cardiology, Medical University of Bialystok, Bialystok, Poland. malgo33@interia.pl

Insights
Subclinical hypothyroidism (SH) is linked to reduced myocardial perfusion and increased intima-media thickness (IMT), suggesting a higher cardiovascular disease risk in affected individuals.
Area of Science:
- Cardiology
- Endocrinology
- Medical Imaging
Background:
- Subclinical hypothyroidism (SH) presents a potential, yet debated, risk factor for cardiovascular disease (CVD).
- Existing data on the association between SH and CVD risk remain inconclusive.
- Assessing subclinical cardiac changes in SH is crucial for risk stratification.
Purpose of the Study:
- To evaluate myocardial perfusion using contrast-enhanced echocardiography in patients with SH.
- To measure intima-media thickness (IMT) in individuals diagnosed with SH.
- To investigate the relationship between SH, myocardial perfusion, and arterial wall thickness.
Main Methods:
- Contrast-enhanced echocardiography with dobutamine stress testing was employed to assess myocardial perfusion.
- Quantitative analysis of myocardial perfusion was performed using Q-LAB Philips software.
- Carotid and femoral intima-media thickness (IMT) were measured in 40 female patients with SH and 15 healthy controls.
Main Results:
- Patients with SH exhibited significantly higher IMT compared to controls (0.7 mm vs. 0.38 mm, p=0.001).
- Myocardial perfusion was significantly reduced at rest and during stress in the SH group (p=0.039 and p=0.01, respectively).
- A negative correlation was observed between IMT and myocardial perfusion index at peak stress (r=-0.54, p=0.014).
Conclusions:
- Contrast-enhanced echocardiography revealed myocardial hypoperfusion and increased IMT in patients with SH.
- These findings suggest that SH may be associated with an elevated risk of developing cardiovascular disease.
- Early detection of subclinical cardiac abnormalities in SH patients is warranted.
Purpose:
The data concerning the relation between subclinical hypothyroidism (SH) and the risk of cardiovascular disease are divergent. We aimed to assess myocardial perfusion in contrast-enhanced echocardiography and intima-media thickness (IMT) in patients with SH.
Material/Methods:
Forty females with SH without symptoms of coronary artery disease and 15 healthy female volunteers were examined. Echocardiographic evaluation of the left ventricle function as well as carotid and femoral IMT complex measurements were performed at baseline. Thereafter, dobutamine stress echocardiography with myocardial perfusion assessment at rest and on the peak of stress test was performed. SonoVue® intravenous bolus as a contrast medium was used. The myocardial perfusion was assessed by quantitative method using Q-LAB Philips software (ROI modality). The perfusion index was calculated (a number of left ventricle segments with improved perfusion/a number of all segments).
Results:
A mean IMT value in the SH group was significantly higher than in the controls (0.7 mm vs. 0.38 mm, p=0.001). Myocardial perfusion at rest and at the peak of stress test was significantly lower in the SH patients as compared to the controls (at rest 120 Db in SH vs. 181 Db in controls, p=0.039 and at the peak of stress 115 Db and 188 Db, p=0.01, respectively). The perfusion index was not significantly worse in the SH group (p=0.6). IMT values negatively correlated with the myocardial perfusion index at the peak of stress (r=-0.54, p=0.014).
Conclusions:
In patients with SH contrast-enhanced echocardiographic examination revealed myocardial hypoperfusion and increased IMT. Our results may suggest that the patients with SH are at risk of the development of cardiovascular disease.
More Related Videos
 08:13
In Vivo Quantitative Assessment of Myocardial Structure, Function, Perfusion and Viability Using Cardiac Micro-computed Tomography
Published on: February 16, 2016
 06:04
Pulse-Wave Velocity, Flow-Mediated Dilation, and Carotid Intima-Media Thickness to Assess Cardiovascular Risk in Population with Metabolic Syndrome
Published on: September 27, 2024
Related Concept Videos
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:20
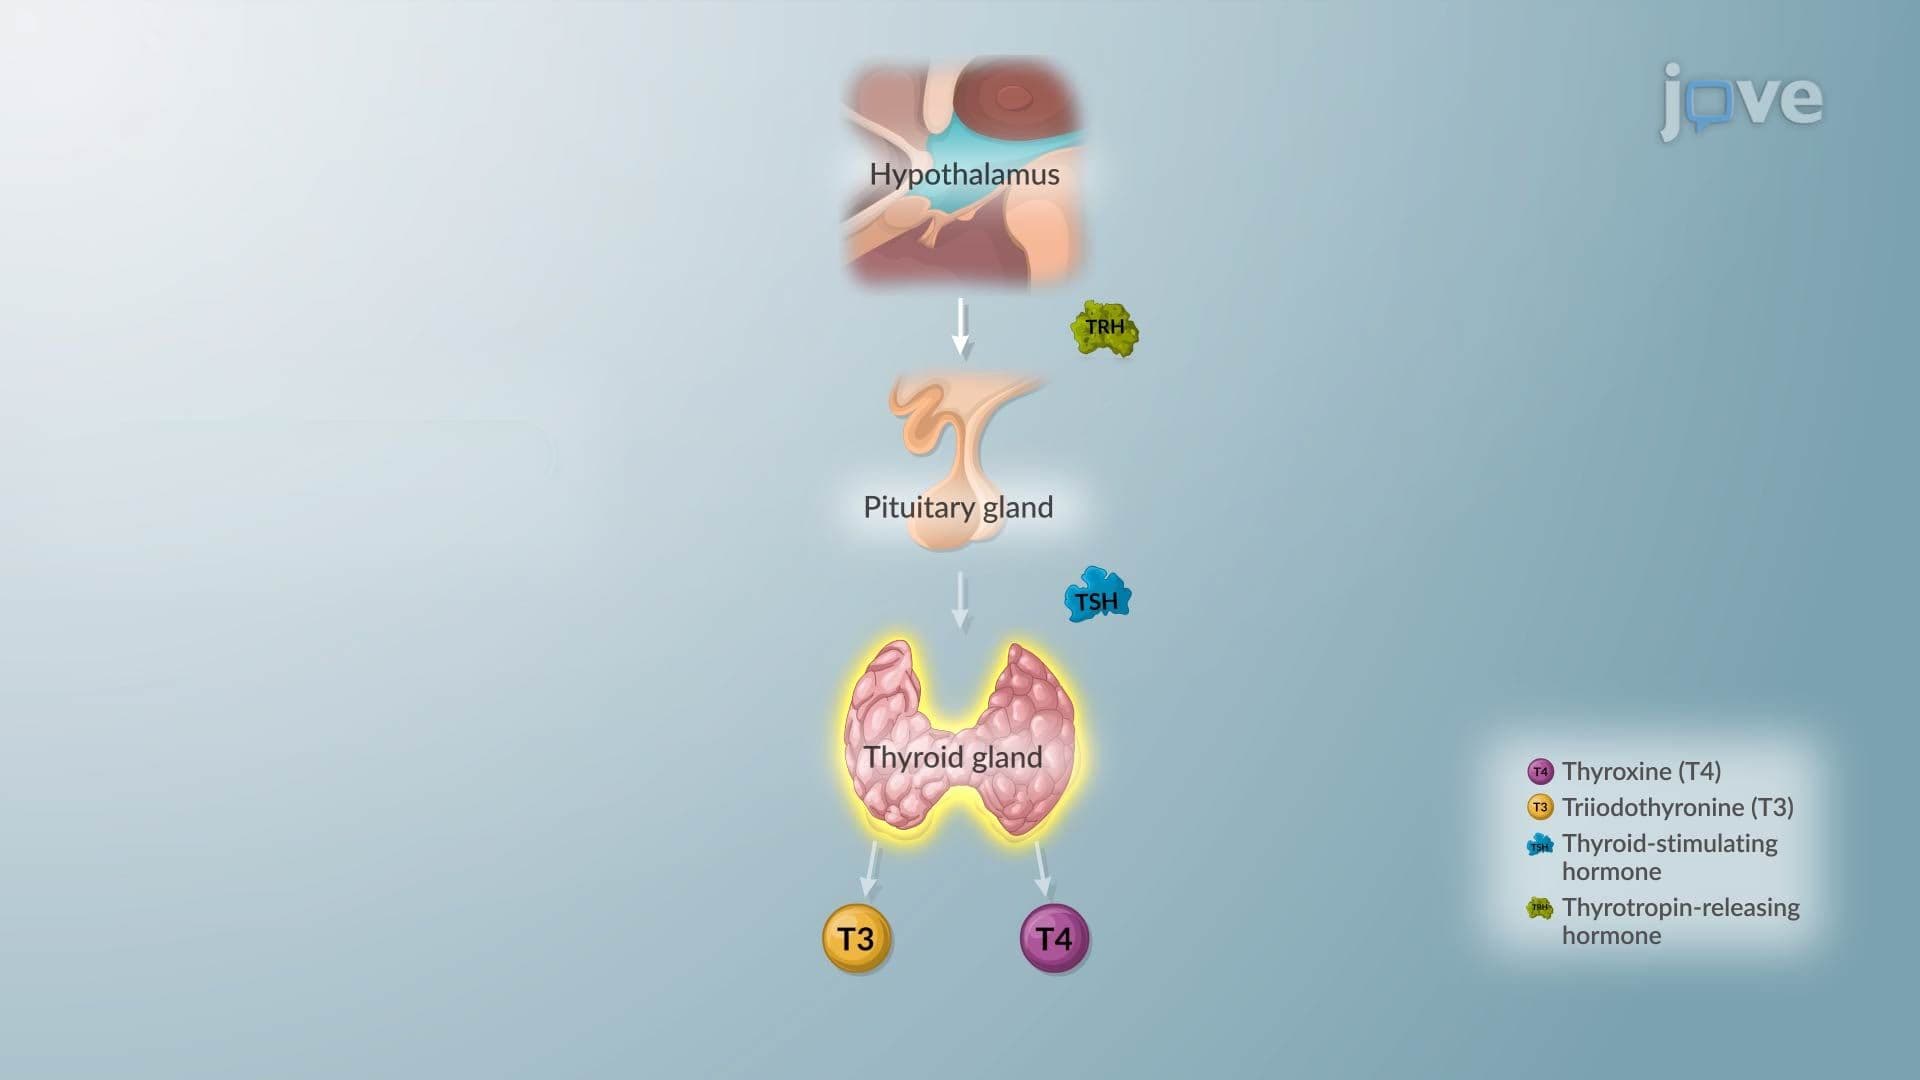
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies