Related Experiment Video
Updated: May 11, 2026
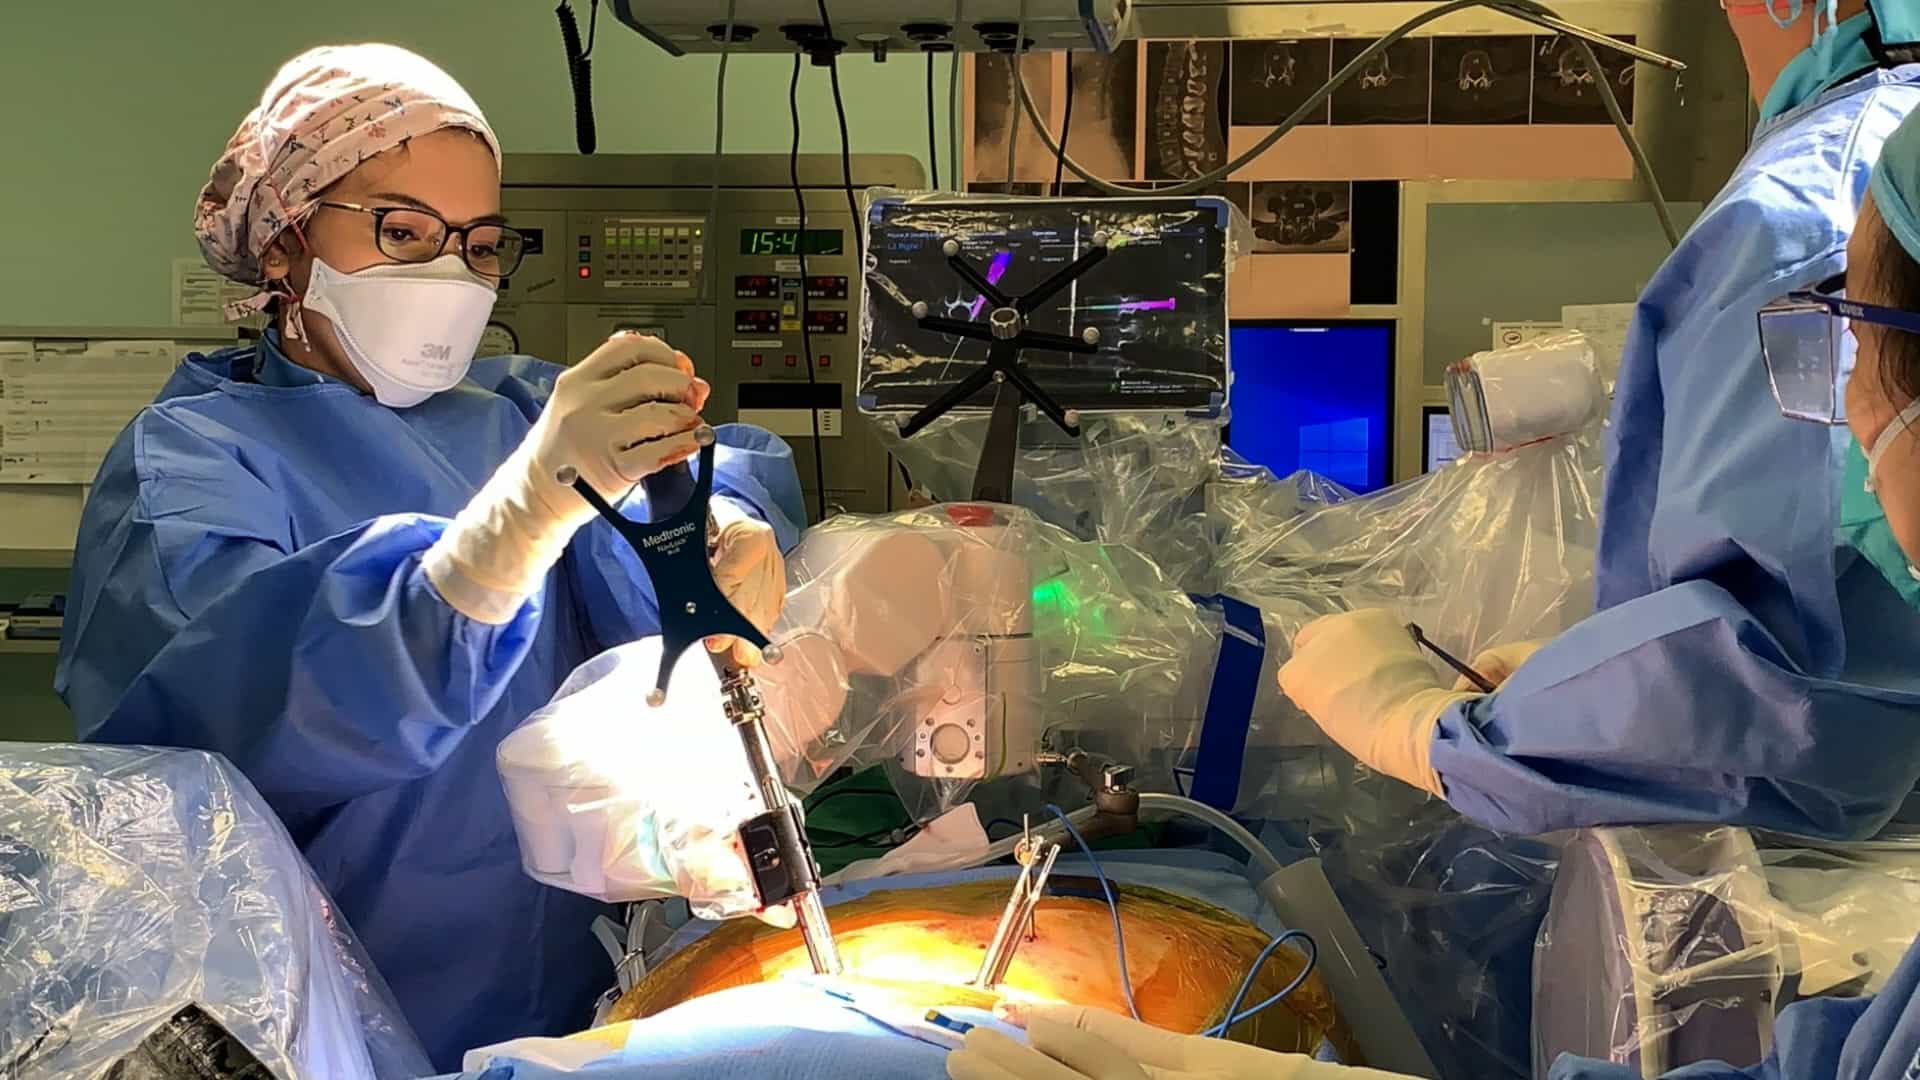

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Surgical management of 4-level cervical spondylotic myelopathy
Yu Shunzhi1, Li Zhonghai, Li Fengning
1Department of Orthopedics, Changhai Hospital, Second Military Medical University, Shanghai, the People’s Republic of China.

Abstract:
The optimal surgical approach for 4-level cervical spondylotic myelopathy is controversial. The authors compared the clinical outcomes, radiographic changes, and complications of 53 patients who underwent either discontinuous corpectomy and fusion (DCF) with reservation of the middle vertebra (n=29) or laminectomy and fusion (n=24). Neurological function was measured using Nurick's grade and modified Japanese Orthopedic Association scores. The Neck Disability Index was recorded for neck-shoulder pain level evaluation. Patients' satisfaction with the surgery was evaluated using the Short Form 36. Segmental lordosis was measured. Both groups demonstrated significantly improved Nurick's grades and Japanese Orthopedic Association scores (P<.001), and the recovery rate was similar between the groups (59.86% ± 17.63% and 60.18% ± 12.01%, respectively). In terms of Neck Disability Index scores, Short Form 36 scores, and cervical lordosis measurements, no significant intergroup differences were found preoperatively. Mean postoperative Neck Disability Index scores were significantly lower in the DCF group (12.31 ± 1.91) than in the laminectomy group (15.04 ± 3.09; P=.000). Mean postoperative segmental lordosis was significantly higher in the DCF group (14.24 ± 2.29) than in the laminectomy group (9.96 ± 2.14; P=.001). The Short Form 36 scores significantly improved in both groups postoperatively (P<.01). Relative to the DCF group, the laminectomy group had a significantly longer operative time (192.25 ± 33.47 vs 192.25 ± 33.47 minutes, respectively; P<.01) and significantly more operative blood loss (455.41 ± 140.46 vs 253.79 ± 77.94 mL, respectively; P<.01). Discontinuous corpectomy and fusion with reservation of the middle vertebra is a safe and effective surgical treatment for 4-level cervical spondylotic myelopathy that results in significant functional improvement in most patients.