Related Experiment Videos
[Magnesium and bronchopulmonary dysplasia]
1Department of Pediatrics A, Schneider Children's Medical Center of Israel, Petach Tikva.

Insights
Magnesium levels may impact bronchopulmonary dysplasia (BPD) in premature infants. Low magnesium (hypomagnesemia) might contribute to BPD development by increasing inflammation and oxidative stress.
Area of Science:
- Neonatology
- Pulmonology
- Biochemistry
Context:
- Bronchopulmonary dysplasia (BPD) is a chronic lung disease affecting premature infants requiring mechanical ventilation and oxygen.
- BPD is characterized by persistent respiratory symptoms, hypoxemia, and abnormal chest radiographs at 36 weeks gestational age.
- Proinflammatory cytokines and impaired angiogenesis contribute to BPD pathogenesis, exacerbated by postnatal hyperoxia.
Purpose:
- To investigate the unclear role of magnesium in the development of bronchopulmonary dysplasia (BPD).
- To explore the association between magnesium levels and respiratory outcomes in premature infants.
Summary:
- High magnesium levels at birth were linked to respiratory distress syndrome (RDS), pulmonary interstitial emphysema, respiratory failure, and BPD.
- Low magnesium intake is associated with reduced lung function; hypomagnesemia is found in acute pulmonary diseases and preterm neonates with RDS.
- Experimental hypomagnesemia induces inflammation, oxidative damage, and altered gene expression related to cell cycle, apoptosis, and remodeling, processes implicated in BPD.
Impact:
- Findings suggest hypomagnesemia may be a contributing factor to BPD pathogenesis.
- Understanding magnesium's role could inform novel therapeutic strategies for preventing or treating BPD.
- This research highlights the potential importance of monitoring and managing magnesium levels in high-risk infants.
Abstract:
Bronchopulmonary dysplasia (BPD) is a chronic lung disease that occurs in premature infants who have needed mechanical ventilation and oxygen therapy. BPD is defined as the presence of persistent respiratory symptoms, the need for supplemental oxygen to treat hypoxemia, and an abnormal chest radiograph at 36 weeks gestational age. Proinflammatory cytokines and altered angiogenic gene signaling impair prenatal and postnatal lung growth, resulting in BPD. Postnatal hyperoxia exposure further increases the production of cytotoxic free radicals, which cause lung injury and increase the levels of proinflammatory cytokines. Magnesium is the fourth most abundant metal in the body. It is commonly used for the treatment of preeclamsia, as well as for premature labor alleviation. Magnesium's role in BPD development is not clear. A significant association between high magnesium levels at birth and respiratory distress syndrome (RDS), pulmonary interstitial emphysema in the extremely low birth weight, respiratory failure, and later development BPD was found. Conversely, low magnesium intake is associated with lower lung functions, and hypomagnesemia was found in 16% of patients with acute pulmonary diseases. Magnesium is used for the treatment of asthmatic attacks. Magnesium deficiency in pregnant women is frequently seen due to low intake. Hypomagnesemia was also found among preterm neonates and respiratory distress syndrome (RDS). Experimental hypomagnesemia evokes an inflammatory response, and oxidative damage of tissues. These were accompanied by changes in gene expression mostly involved in regulation of cell cycle, apoptosis and remodeling, processes associated with BPD. It is rational to believe that hypomagnesemia can contribute to BPD pathogenesis.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
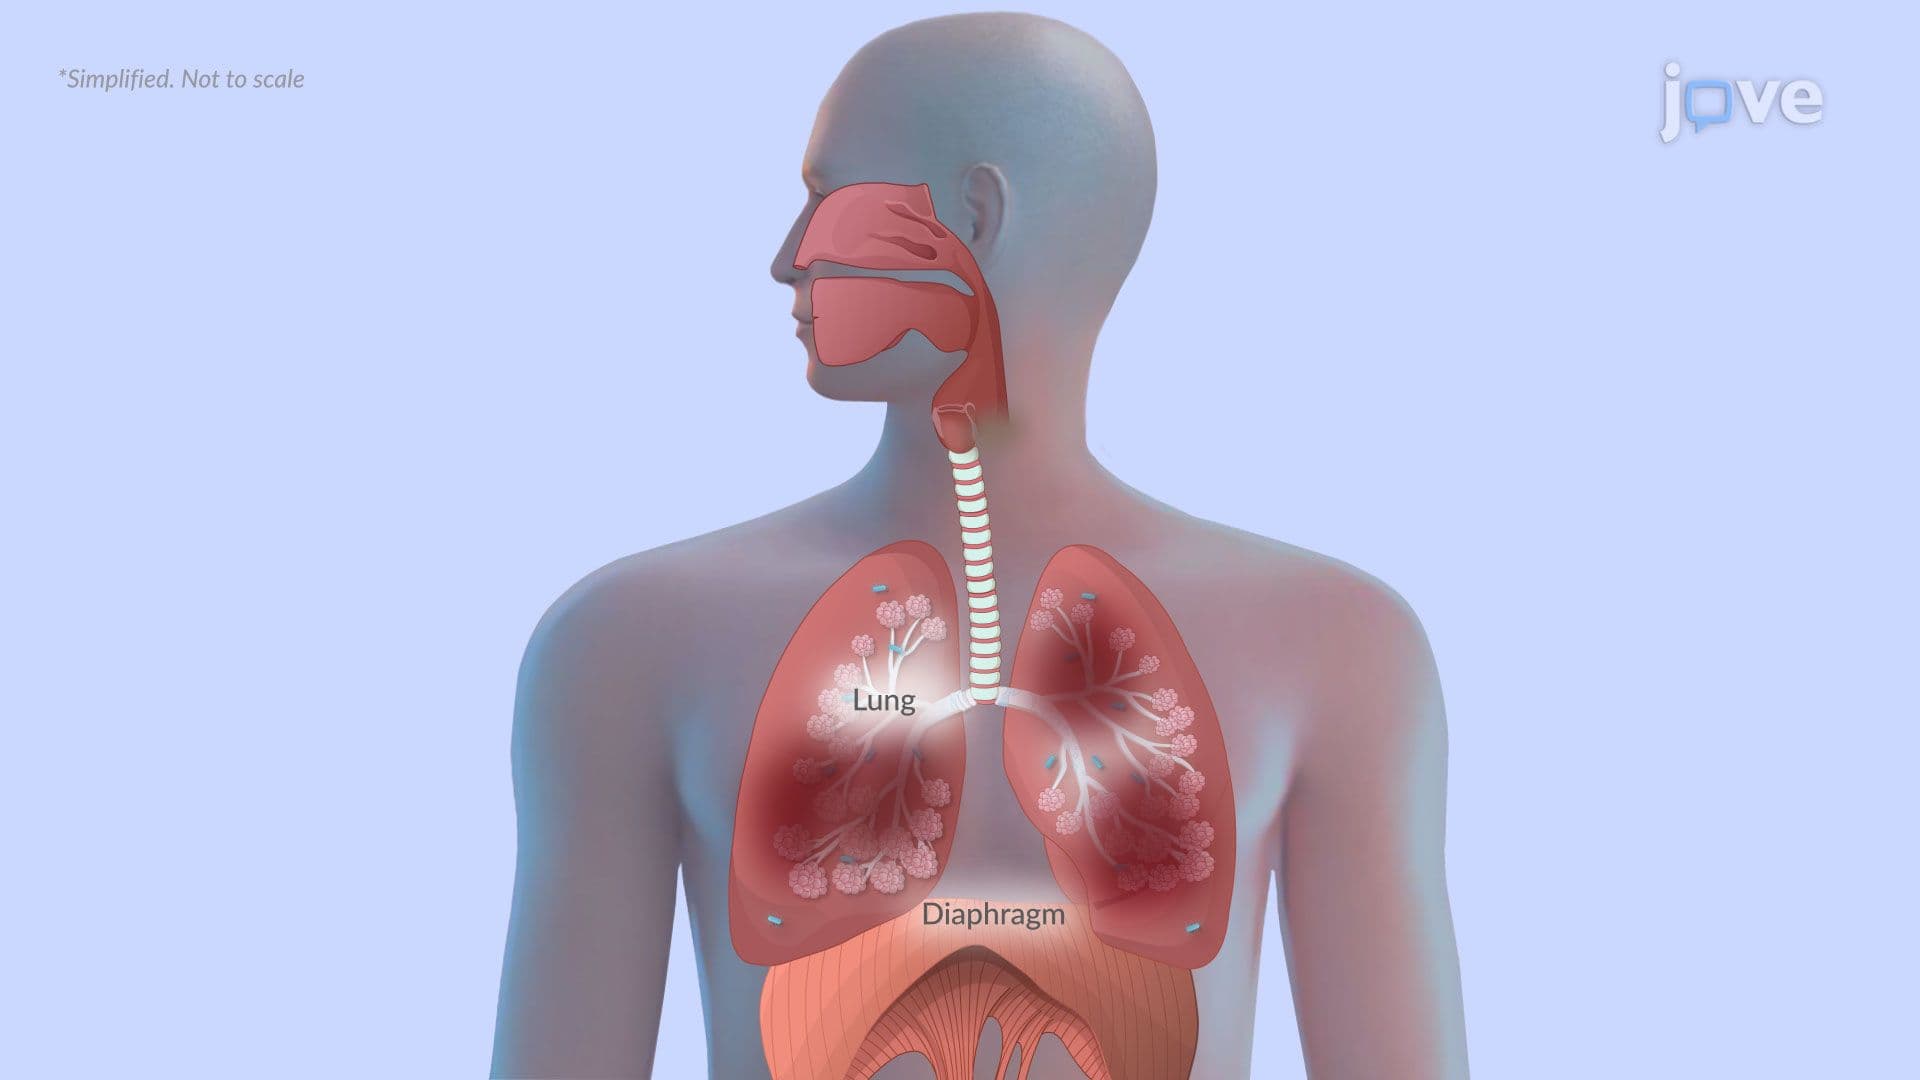 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:10
Atelectasis II: Pathophysiology