Related Experiment Video
Updated: May 10, 2026


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Intravenous sodium bicarbonate therapy in severely acidotic diabetic ketoacidosis
Bryson Duhon1, Rebecca L Attridge, A Crystal Franco-Martinez
1Department of Pharmacy, University Hospital, University Health System, San Antonio, TX, USA.

Background:
The use of intravenous bicarbonate in diabetic ketoacidosis (DKA) may be considered for patients with a pH less than 6.9 according to the American Diabetes Association. The impact of this therapy on resolution of acidosis in patients with DKA is unclear.
Objective:
To determine whether the use of intravenous bicarbonate therapy was associated with improved outcomes in patients with severe DKA who were seen in the emergency department.
Methods:
This review was conducted from 2007 to 2011 in the emergency department of a tertiary teaching hospital. Adults diagnosed with DKA with an initial pH less than 7.0 were included. Patients were stratified into 2 groups based on receipt of intravenous bicarbonate. The primary study outcome was time to resolution of acidosis, defined as return to pH greater than 7.2. Secondary outcomes included length of stay; continuous infusion insulin use; and intravenous fluid, po tas si um, and insulin requirements within the first 24 hours of hospital admission, beginning upon admittance to the emergency department. We also conducted a subgroup analysis of patients with an initial pH less than 6.9.
Results:
There was no significant difference in time to resolution of acidosis (8 hours vs 8 hours; p = 0.7) or time to hospital discharge (68 hours vs 61 hours; p = 0.3) between patients who received intravenous bicarbonate (n = 44) compared with those who did not (n = 42). The median dose of intravenous bicarbonate was 100 mEq (100-150) for patients who received intravenous bicarbonate. Insulin and fluid requirements in the first 24 hours were significantly higher in patients who received intravenous bicarbonate compared with those who did not (100 units vs 86 units; p = 0.04 and 7.6 L vs 7.2 L; p = 0.01, respectively). There was no significant difference in hours of continuous insulin infusion (27 hours vs 26 hours; p = 0.09) or potassium requirements in the first 24 hours of hospital stay (135 mEq vs 120 mEq; p = 0.84).
Conclusions:
Intravenous bicarbonate therapy did not decrease time to resolution of acidosis or time to hospital discharge for patients with DKA with an initial pH less than 7.0.


Related Concept Videos
 01:25
Diabetic Ketoacidosis l: Introduction
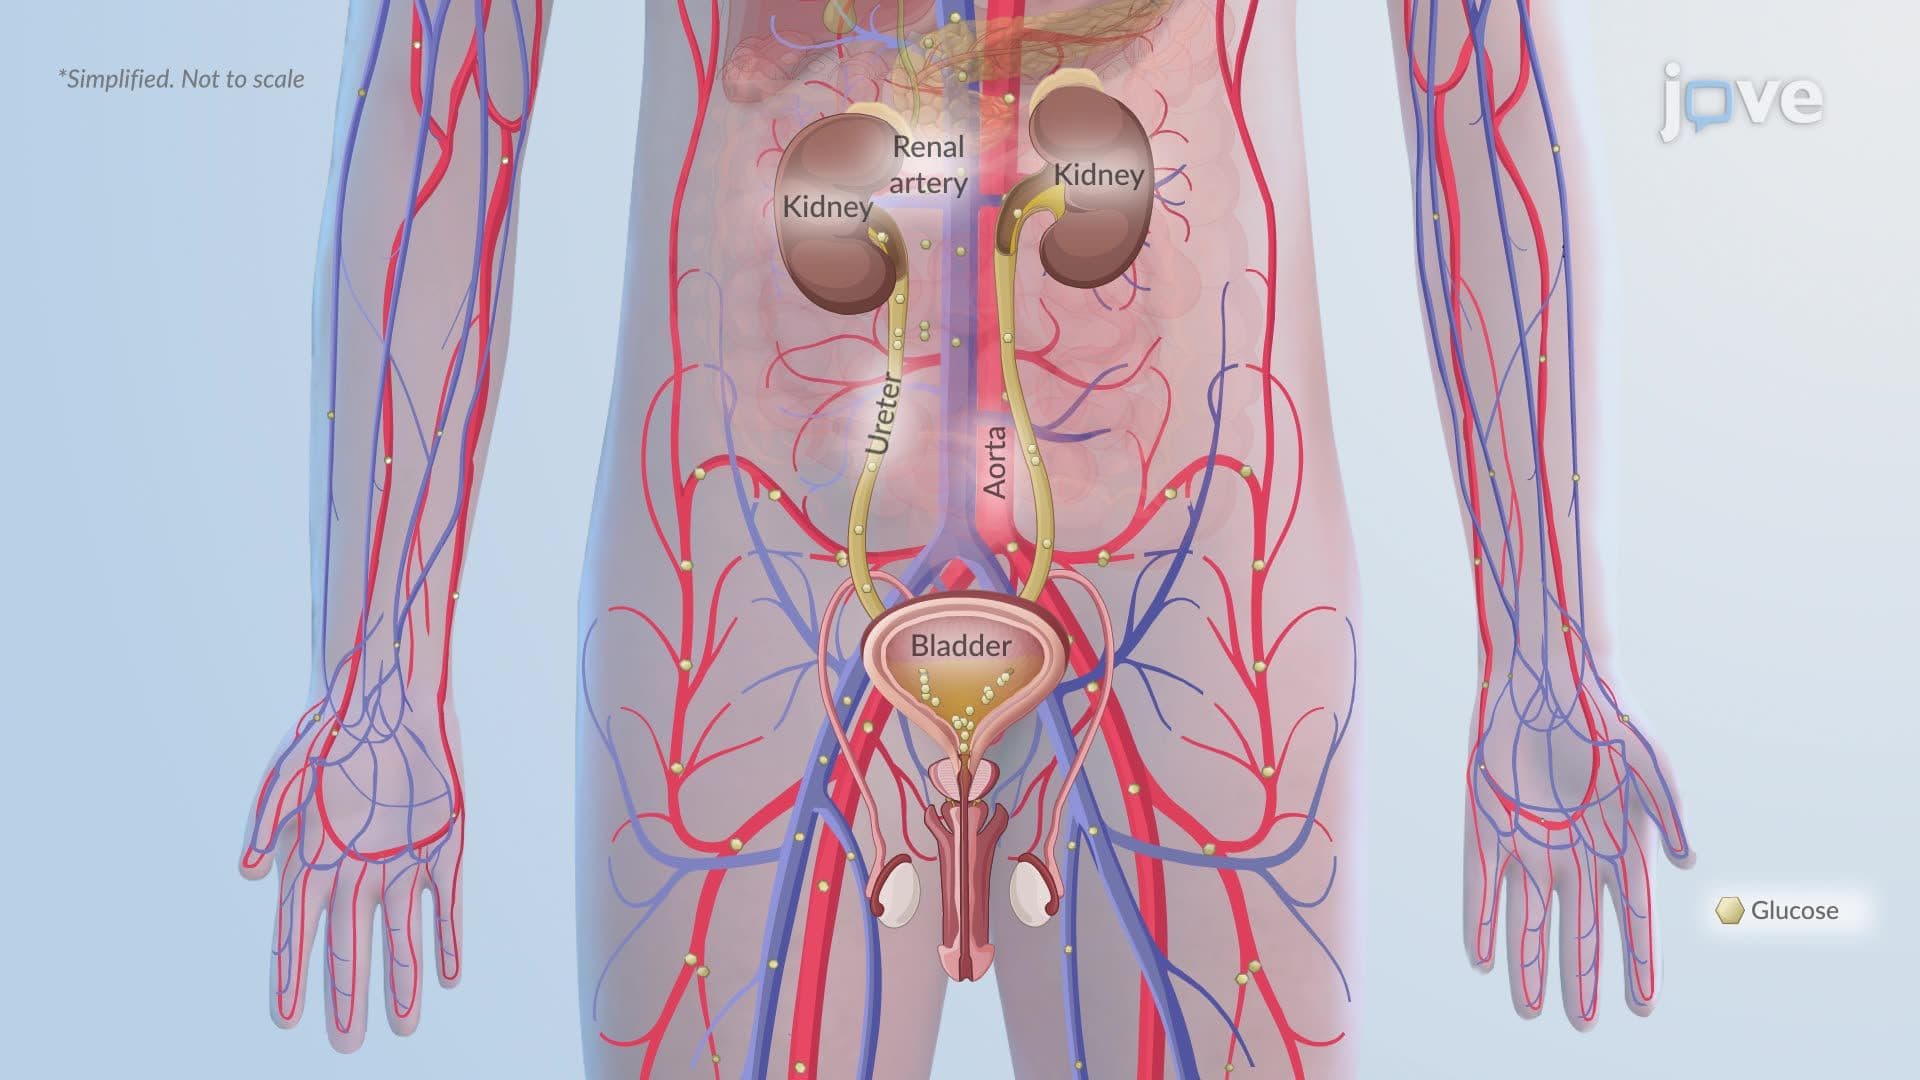 01:22
Diabetic Ketoacidosis ll: Pathophysiology
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
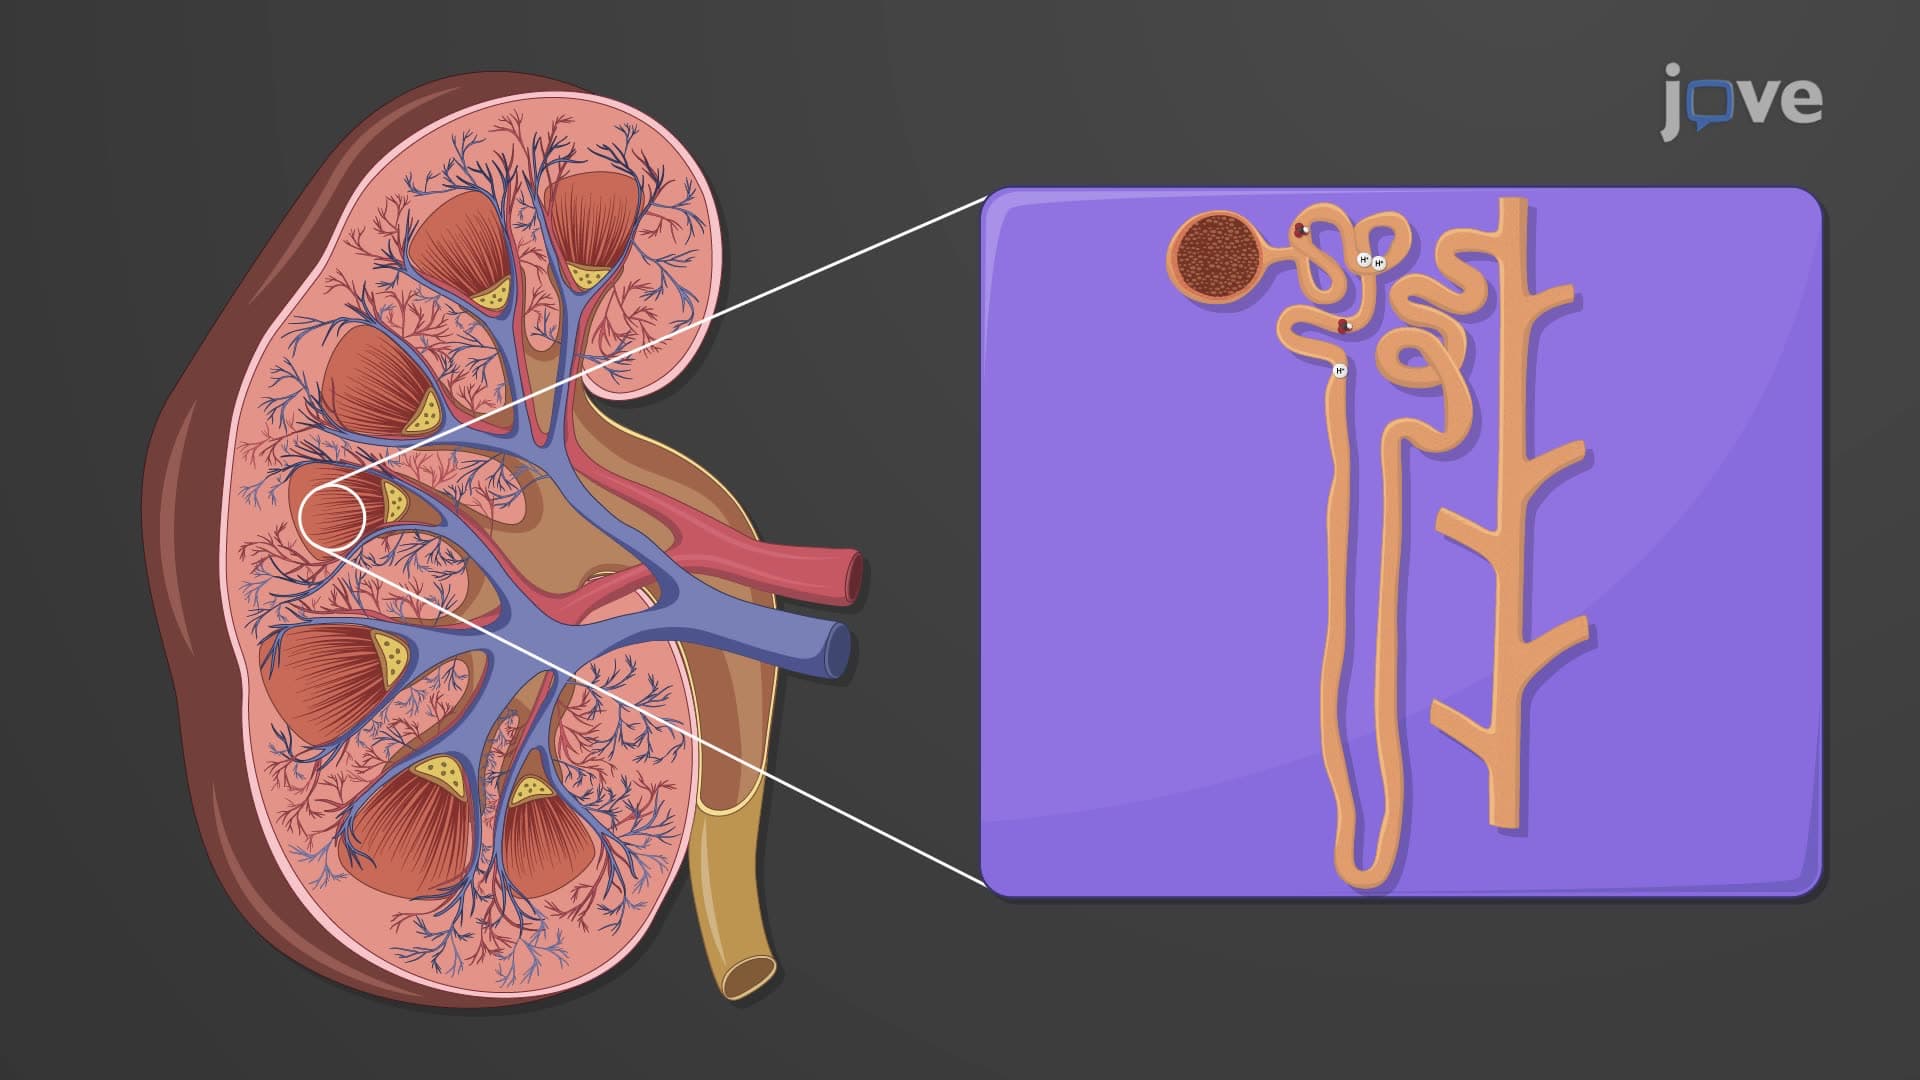 01:29
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...