Related Experiment Video
Updated: May 10, 2026
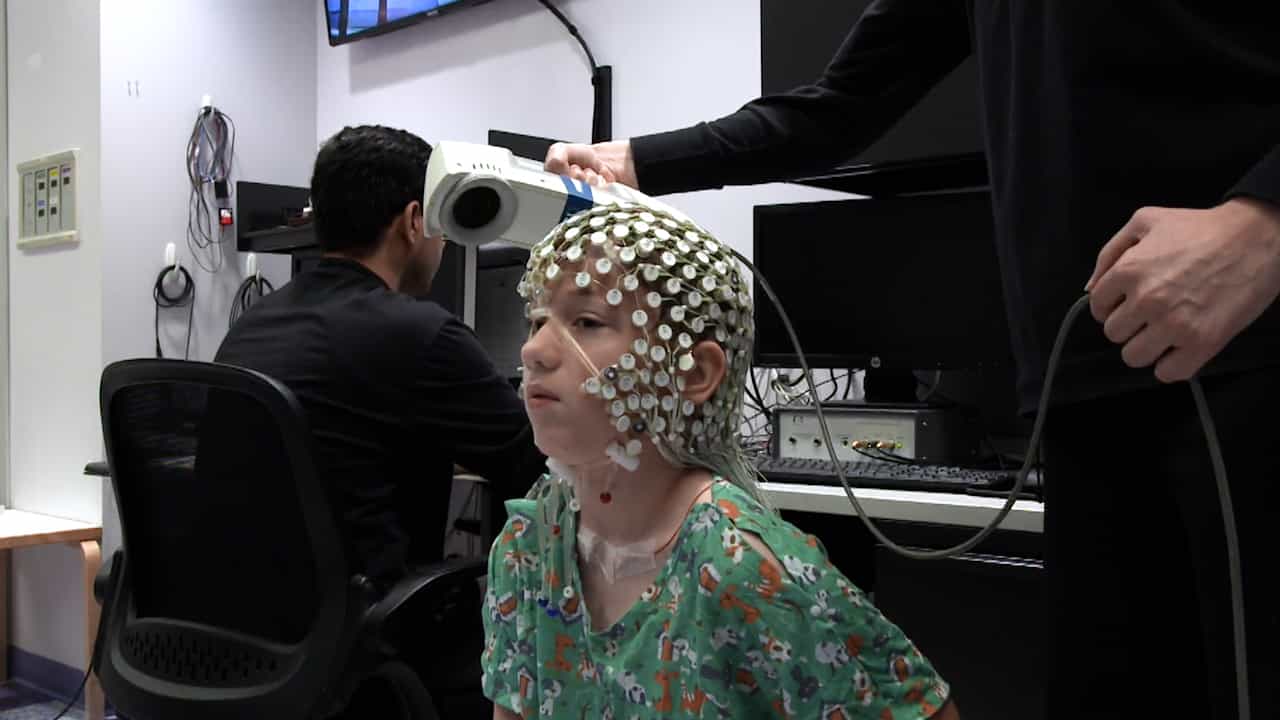

Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
Vitamin D deficiency in children with epilepsy: Do we need to detect and treat it?
Pooja Harijan1, Arif Khan, Nahin Hussain
1Department of Paediatric Neurology, Leicester Royal Infirmary, University Hospitals of Leicester NHS Trust, Leicester LE1 5WW, United Kingdom.

Insights
Children with epilepsy on antiepileptic drugs face higher fracture risks. While studies show mixed results on bone density, vitamin D supplementation is recommended due to potential benefits for bone health.
Area of Science:
- Pediatric Neurology
- Bone Metabolism
- Pharmacology
Background:
- Children on antiepileptic drugs (AEDs) exhibit compromised bone metabolism, reduced bone mineral density, and elevated fracture risk (2-3x controls).
- Existing literature on bone health in pediatric epilepsy is limited by small sample sizes and failure to account for confounding factors like comorbidities, mobility, nutrition, and obesity.
Purpose of the Study:
- To review existing literature on bone mineral density (BMD) in children with epilepsy.
- To evaluate the efficacy of vitamin D therapy in children treated with AEDs.
- To identify gaps in research and propose future study directions.
Main Methods:
- Systematic literature review of studies on bone mineral density markers in children with epilepsy.
- Review of studies investigating vitamin D therapy in pediatric epilepsy patients.
- Analysis of limitations in existing research, including sample size and confounding variables.
Main Results:
- Most studies found no significant differences in BMD markers, but were limited by small sample sizes and lack of control for confounding factors.
- Evidence for the efficacy of vitamin D therapy in children with epilepsy is limited and studies often lack stratification for confounding factors.
- A need for larger studies with clinically significant outcomes (e.g., fractures) and inclusion of at-risk populations (e.g., symptomatic generalized epilepsy, impaired mobility, polytherapy) is identified.
Conclusions:
- Despite limited evidence, concern persists regarding poor bone health in children with epilepsy, suggesting potential benefits from vitamin D therapy.
- Low-dose vitamin D supplementation (400 IU/day) is biologically plausible and recommended, especially given potential higher deficiency risk in this population.
- Neurologists should ensure prescription and compliance monitoring of low-dose vitamin D supplementation for children with epilepsy.
Abstract:
Children and adolescents treated with antiepileptic drugs are known to have problems with bone metabolism, bone mineral density loss, and 2-3 times the fracture risk of healthy controls. We reviewed the literature regarding bone mineral density in children with epilepsy and vitamin D therapy in children treated with anti-epileptic drugs. Studies of bone mineral density markers in children with epilepsy have mostly found little significant difference in bone mineral density markers in children with epilepsy. They have been limited by small sample size and many of the studies have not corrected for confounding factors such as comorbidities, mobility, nutrition, and obesity. Studies of vitamin D therapy in children with epilepsy have shown little evidence of effect and have been similarly limited by lack of stratification with regard to confounding factors. There is a need for larger studies, using clinically significant outcomes such as fractures, including at risk populations such as symptomatic generalised epilepsy, impaired mobility, and polytherapy. At the present time in the absence of good evidence to the contrary, there remains concern that children with epilepsy are at risk of poor bone health and that vitamin D therapy may be beneficial. As low-dose vitamin D supplementation (400 IU per day) is now recommended for healthy children and it is biologically feasible that children with epilepsy may be at higher risk of clinically significant deficiency, it is important that neurologists ensure that low-dose vitamin D supplementation should be prescribed and compliance followed up in children with epilepsy.
More Related Videos
 10:46
Sampling Cerebrospinal Fluid and Blood from Lateral Tail Vein in Rats During EEG Recordings
Published on: September 1, 2023
 10:22
Interictal High Frequency Oscillations Detected with Simultaneous Magnetoencephalography and Electroencephalography as Biomarker of Pediatric Epilepsy
Published on: December 6, 2016
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:22
Epilepsy ll: Types
 01:17
Antiepileptic Drugs: Calcium Channel Blockers
Calcium channel blockers exert their antiepileptic effects by targeting T-type calcium channels, which are integral to transmitting nerve signals in the central nervous system. These channels allow the passage of calcium ions, which are vital for neuronal communication. By inhibiting T-type calcium channels, calcium channel blockers effectively reduce the release of neurotransmitters and...
 01:08
Antiepileptic Drugs: Sodium Channel Blockers
Sodium channel blockers modulate ion channels, particularly voltage-gated sodium channels. They block only sodium ion movement.
Among the most commonly prescribed antiepileptic drugs are...
 01:20
Antiepileptic Drugs: Modulators of Neurotransmitter Release Mediated by SV2A Protein
SV2A is a transmembrane glycoprotein located predominantly in the brain, modulating the release of neurotransmitters for neuronal communication. Both levetiracetam and brivaracetam exhibit a high affinity for...
 01:14
Antiepileptic Drugs: Glutamate Antagonists