Related Experiment Video For Computer tomography
Updated: May 10, 2026

Dynamic Contrast Enhanced Magnetic Resonance Imaging of an Orthotopic Pancreatic Cancer Mouse Model
Published on: April 18, 2015
Focal autoimmune pancreatitis: radiological characteristics help to distinguish from pancreatic cancer
Gao-Feng Sun1, Chang-Jing Zuo, Cheng-Wei Shao
1Department of Radiology, Changhai Hospital, the Second Military Medical University, Shanghai 200433, China.

Aim:
To identify the radiological characteristics of focal autoimmune pancreatitis (f-AIP) useful for differentiation from pancreatic cancer (PC).
Methods:
Magnetic resonance imaging (MRI) and triple-phase computed tomography (CT) scans of 79 patients (19 with f-AIP, 30 with PC, and 30 with a normal pancreas) were evaluated retrospectively. A radiologist measured the CT attenuation of the pancreatic parenchyma, the f-AIP and PC lesions in triple phases. The mean CT attenuation values of the f-AIP lesions were compared with those of PC, and the mean CT attenuation values of pancreatic parenchyma in the three groups were compared. The diagnostic performance of CT attenuation changes from arterial phase to hepatic phase in the differentiation between f-AIP and PC was evaluated using receiver operating characteristic (ROC) curve analysis. We also investigated the incidence of previously reported radiological findings for differentiation between f-AIP and PC.
Results:
The mean CT attenuation values of f-AIP lesions in enhanced phases were significantly higher than those of PC (arterial phase: 60 ± 7 vs 48 ± 10, P < 0.05; pancreatic phase: 85 ± 6 vs 63 ± 15, P < 0.05; hepatic phase: 95 ± 7 vs 63 ± 13, P < 0.05). The mean CT attenuation values of f-AIP lesions were significantly lower those of uninvolved pancreas and normal pancreas in the arterial and pancreatic phase of CT (P < 0.001, P < 0.001), with no significant difference at the hepatic phase or unenhanced scanning (P = 0.4, P = 0.1). When the attenuation value increase was equal or more than 28 HU this was considered diagnostic for f-AIP, and a sensitivity of 87.5%, specificity of 100% and an area under the ROC curve of 0.974 (95%CI: 0.928-1.021) were achieved. Five findings were more frequently observed in f-AIP patients: (1) sausage-shaped enlargement; (2) delayed homogeneous enhancement; (3) hypoattenuating capsule-like rim; (4) irregular narrowing of the main pancreatic duct (MPD) and/or stricture of the common bile duct (CBD); and (5) MPD upstream dilation ≤ 5 mm.
Conclusion:
Analysis of a combination of CT and MRI findings could improve the diagnostic accuracy of differentiating f-AIP from PC.

Related Concept Videos
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
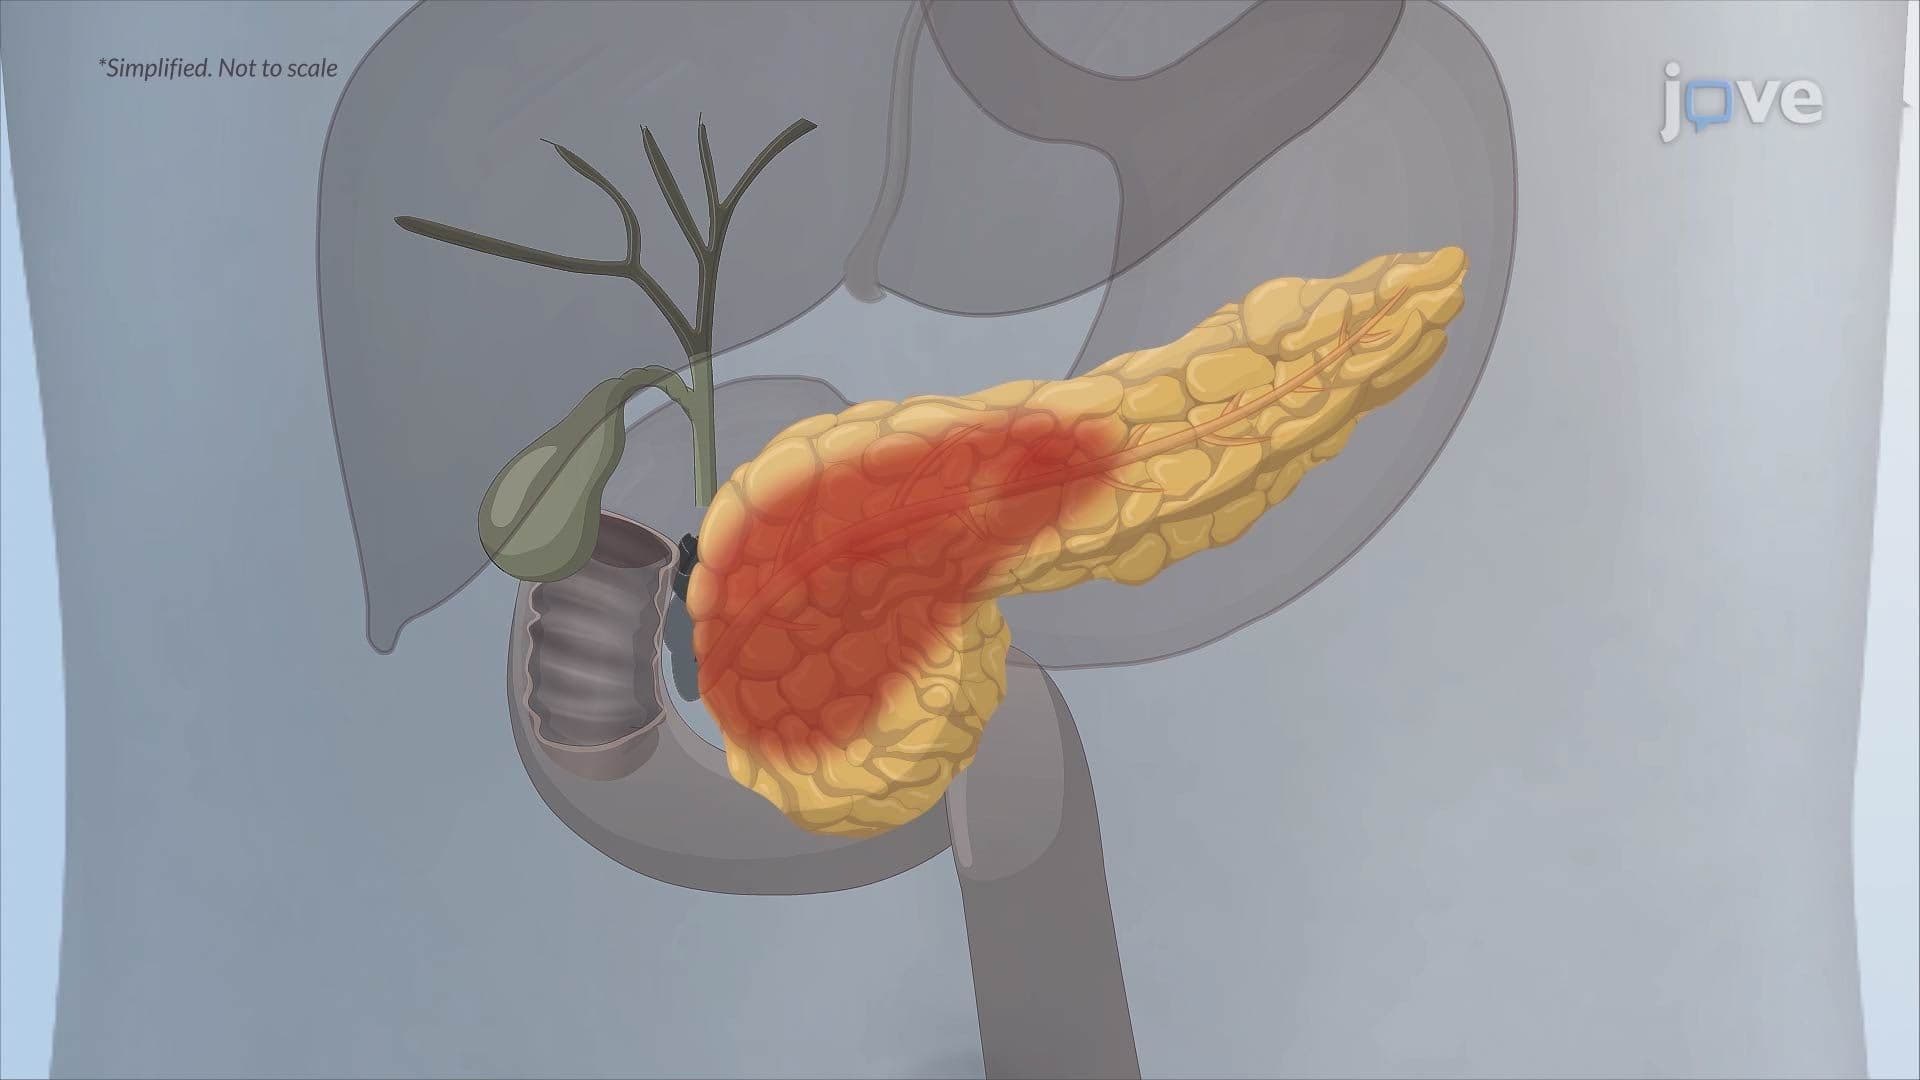
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: