Related Experiment Video
Updated: May 10, 2026
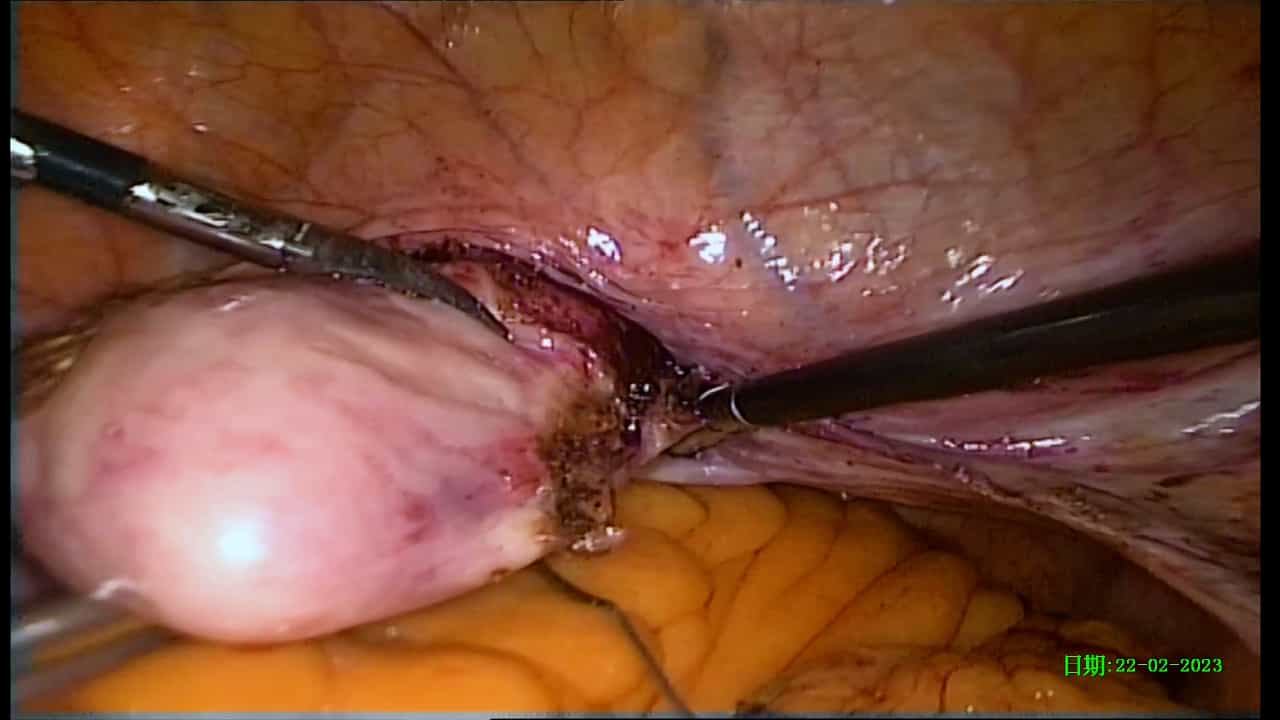
Laparoscopic Non-Mesh Cerclage Pectopexy with Uterine Preservation for Pelvic Organ Prolapse
Published on: October 25, 2024
Ulipristal acetate prevents ovulation more effectively than levonorgestrel: analysis of pooled data from three
Vivian Brache1, Leila Cochon, Maëva Deniaud
1PROFAMILIA, Santo Domingo, Dominican Republic.

Background:
The days just prior to ovulation are the most crucial for emergency contraception (EC) efficacy. Ulipristal acetate (UPA) and levonorgestrel's (LNG) capacity to inhibit follicular rupture have never been compared directly at this time of the cycle.
Study Design:
Raw data from three pharmacodynamics studies with similar methodology were pooled to allow direct comparison of UPA, LNG and LNG + meloxicam's ability to prevent ovulation when administered orally in the advanced follicular phase, with a leading follicle of ≥ 18 mm.
Results:
Forty eight LNG-treated (1.5 mg) cycles, 31 LNG (1.5 mg) + meloxicam (15 mg), 34 UPA (30 mg) cycles and 50 placebo cycles were compared. Follicle rupture was delayed for at least 5 days in 14.6%, 38.7%, 58.8% and 4% of the LNG-, LNG + meloxicam-, UPA- and placebo-treated cycles, respectively. UPA was more effective than LNG and placebo in inhibiting follicular rupture (p = .0001), while LNG, when administered at this time of the cycle, was not different than placebo. The addition of meloxicam improved the efficacy of LNG in preventing follicular rupture (p = .0292 vs. LNG; p = .0001 vs. placebo; non-significant vs. UPA). UPA was effective in preventing rupture in the 5 days following treatment, even when administered at the time of the luteinizing hormone (LH) surge (UPA 79%, LNG 14% and placebo 10%). None of the treatments were effective when administered on the day of the LH peak. The median time from treatment to rupture was 6 days during the ulipristal cycles and 2 days in the placebo and LNG/LNG + meloxicam cycles (p = .0015).
Conclusion:
Although no EC treatment is 100% effective in inhibiting follicular rupture when administered in the late follicular phase, UPA is the most effective treatment, delaying ovulation for at least 5 days in 59% of the cycles. LNG is not different from placebo in inhibiting follicular rupture at this advanced phase of the cycle. No treatment was effective in postponing rupture when administered on the day of LH peak.
Related Concept Videos
 01:22
Birth Control Methods
 01:21
Intrauterine Drug Delivery Systems
 01:27
Ovarian Cycle
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...