Related Experiment Video
Updated: May 10, 2026
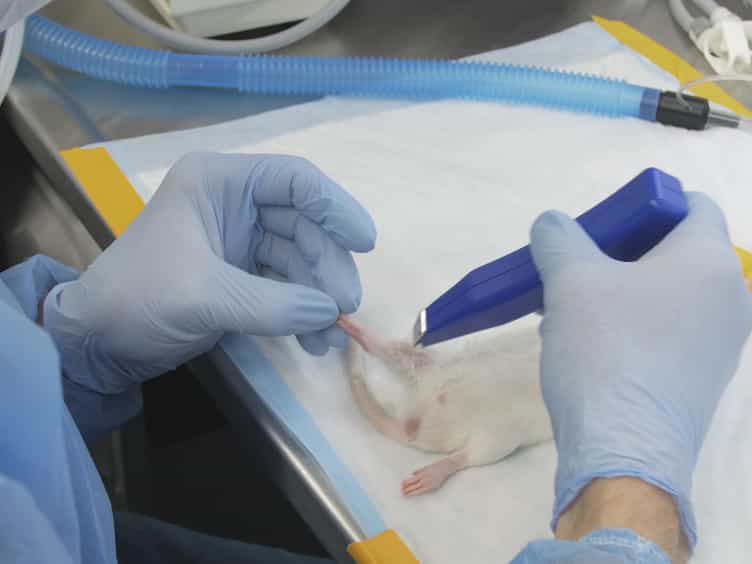

A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
Clinical characteristics of severe supracondylar humerus fractures in children
Sumeet Garg1, Amanda Weller, A Noelle Larson
1*Department of Orthopaedic Surgery, Children's Hospital, University of Colorado, Aurora, CO †UT Southwestern, Children's Medical Center #Texas Scottish Rite Hospital, Dallas, TX ‡Mayo Clinic Rochester, MN §Emory University, Children's Healthcare of Atlanta, Atlanta, GA ∥St. Christopher Hospital for Children, Drexel University, Philadelphia, PA ¶Department of Orthopedics, Brown University, Providence, RI.

Insights
Delayed surgery for severe pediatric elbow fractures is safe. This study found no increased complications with delayed treatment for type 3 supracondylar humerus fractures, suggesting clinical judgment is key.
Area of Science:
- Orthopedic surgery
- Pediatric trauma
- Fracture management
Background:
- The safety of delayed surgical intervention for severe pediatric elbow fractures, particularly type 3 supracondylar fractures, is a subject of ongoing debate.
- Limited large-scale studies have specifically evaluated the complications associated with both the injury and surgical treatment of type 3 fractures based on treatment timing.
Purpose of the Study:
- To evaluate the outcomes and complication rates of treating severe pediatric supracondylar elbow fractures (type 3) at varying time intervals after initial presentation.
- To determine if delayed surgical treatment impacts patient morbidity and surgical outcomes in this specific fracture type.
Main Methods:
- A retrospective review of 1296 children undergoing operative treatment for supracondylar humerus fractures between 2004 and 2007 was conducted, focusing on 872 cases of type 3 fractures.
- Patients were categorized into four groups based on time from presentation to surgery: <6 hours, 6-12 hours, 12-24 hours, and >24 hours.
- Data on vascular status, nerve injury, operative details, and postoperative complications were collected from clinical, operative, and outpatient records.
Main Results:
- No significant differences in sex, age, or injury mechanism were observed across the different time-to-surgery groups.
- Vascular compromise (absent pulse) was noted in 6% of patients at presentation, with only 5 requiring vascular intervention.
- Nerve injury occurred in 12% of patients; medial entry pin use was not linked to ulnar nerve injury. Importantly, increased time to surgery did not correlate with higher morbidity or complication rates; a trend towards decreased complications with delayed treatment was observed.
Conclusions:
- This single-center study, the largest of its kind on severe type 3 supracondylar humerus fractures, provides data on vascular compromise, nerve injury, and other complications.
- The findings suggest that delayed surgical management is a safe option for most children with type 3 supracondylar humerus fractures.
- Optimal patient outcomes depend on judicious clinical decision-making regarding the timing of surgical intervention.
Background:
The safety of delayed surgical treatment of severe supracondylar elbow fractures in children remains debated. No large studies have evaluated complications of injury and surgery evaluating only type 3 fractures. Our aim was to review the results of our experience treating children with severe supracondylar elbow fractures at various time points after injury.
Methods:
All children treated operatively for supracondylar humerus fractures from 2004 to 2007 at a single pediatric trauma center were identified. A total of 1296 children had operative treatment, of which 872 had type 3 fractures. Clinical records were reviewed to identify time to surgery from presentation at our institution. Patients were grouped into 4 cohorts [<6 h (n=325), 6 to 12 h (n=224), 12 to 24 h (n=295), and >24 h (n=28)]. Emergency, operative, inpatient, and outpatient records were reviewed to determine morbidity at presentation as well as operative and postoperative complications.
Results:
There was no difference in sex, age, or energy mechanism between children in the various time groups. An absent pulse was found in 54 children (6%) at presentation, of which only 5 ultimately required a vascular intervention. Nerve injury occurred in 105 patients (12%). Use of a medial entry pin was not associated with ulnar nerve injury. Increased time from presentation to surgery was not associated with increased morbidity from the injury or treatment complications. In contrast, there was a trend to steady decrease in morbidity and complication rates with increased time to surgery.
Conclusions:
This is the largest single-center study of severe supracondylar humerus fractures and describes rates of vascular compromise, nerve injury, infection, and other complications of these injuries. Most children with type 3 supracondylar humerus fractures can be treated safely in a delayed manner. Appropriate clinical judgment is imperative to optimize outcomes.
Level Of Evidence:
Level III--retrospective comparative study.
Related Concept Videos
 01:19
Bones of the Upper Limb: Humerus
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:15
Bones of the Upper Limb: Ulna
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:18
Classification of Bones
Long and Short Bones
The appendicular skeleton, particularly the upper and lower limbs, is primarily made of long and short bones. The long...