Related Experiment Video
Updated: May 10, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Risk stratification by injury distribution in polytrauma patients - does the clavicular fracture play a role?
Klemens Horst1, Thomas Dienstknecht1, Roman Pfeifer1
1Department of Trauma and Reconstructive Surgery, University Hospital RWTH Aachen, Pauwelsstreet 30, 52074 Aachen, Germany.

Background:
Thoracic and extremity injuries are common in polytraumatized patients. The clavicle limits the upper thoracic cage and connects the body and upper extremities. It is easy to examine and is visible on standard emergency room radiographs. We hypothesize that clavicular fracture in polytrauma patients indicates the presence of further injuries of the upper extremities, head, neck and thorax.
Material And Methods:
Retrospective study including patients admitted between 2008 and 2012 to a level-I trauma center.
Inclusion Criteria:
ISS > 16, two or more injured body regions, clavicular fracture.
Control Group:
patients admitted in 2011, ISS > 16, two or more injured body regions, no clavicular fracture. Patient information was obtained from the patients' charts; evaluation of radiographic findings was performed; scoring was based on the Abbreviated Injury Scale (AIS) and Injury Severity Score (ISS) AIS/ISS; data were analyzed using Pearson's correlation and the Mann-Whitney U-test in SPSS (version 11.5.1); graphs were drawn using EXCEL®.
Results:
Thirty-four patients with clavicular fracture (C+) and 40 without (C-) were included; the mean ISS was 25 (range 16-57), m = 70%, f = 30%; age 43.3 years (range 9-88); clavicular fractures were positively correlated with severe thoracic (p = 0.011, OR 4.5: KI 1.3-15.3), external (p < 0.001, OR 9.2: KI 2.7-30.9) and upper extremity injuries (p < 0.001, OR 33.2: KI 6.9-16.04 resp. p = 0.004, OR 12.5: KI 1.5-102.9). C + showed a lower head/neck AIS (p = 0.033), higher thorax AIS (p = 0.04), arm/shoulder AIS (p = 0.001) and external AIS (0.003) than C-. Mean hospital stay and ICU treatment time were longer in the C + group (p = 0.001 and p = 0.025 respectively).
Conclusion:
A clavicular fracture can be diagnosed easily and may be used as a pointer for further thoracic and upper extremity injuries in polytrauma patients that might have been otherwise missed. Special attention should be paid on second and tertiary survey.
More Related Videos
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015
 11:21
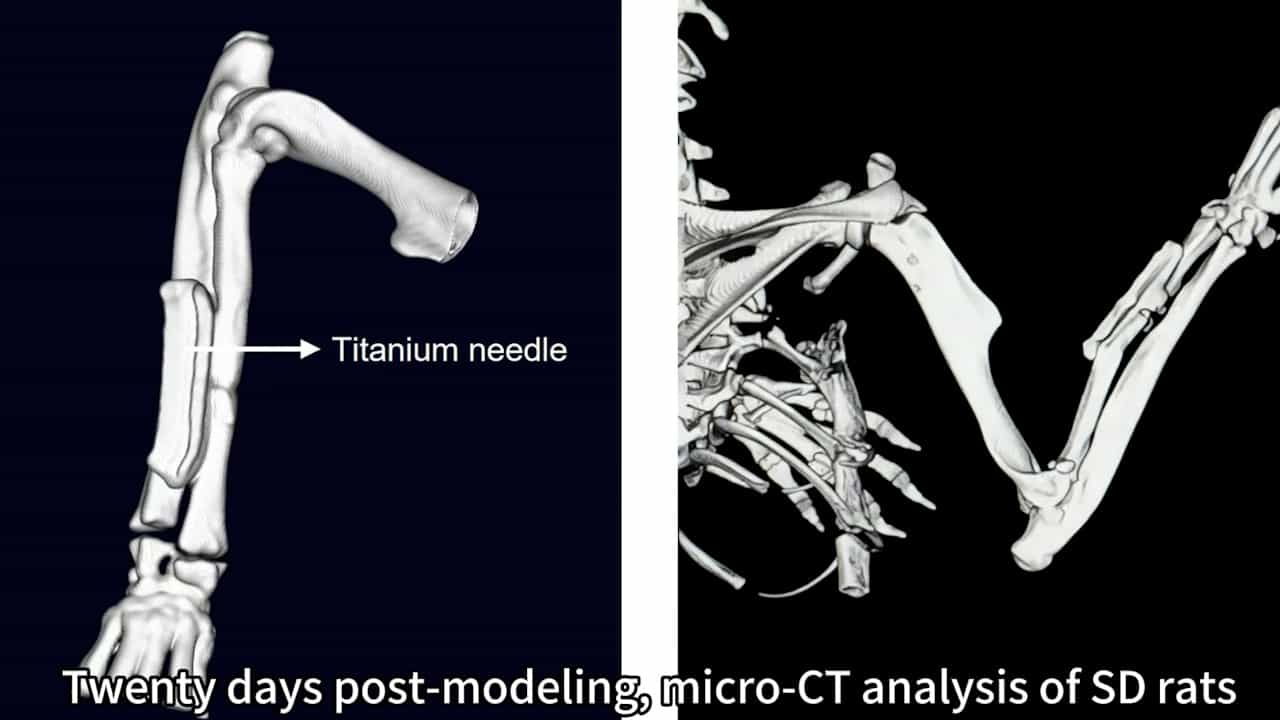
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:21
Cellular Injury II: Classification
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology