Related Experiment Video
Updated: May 9, 2026
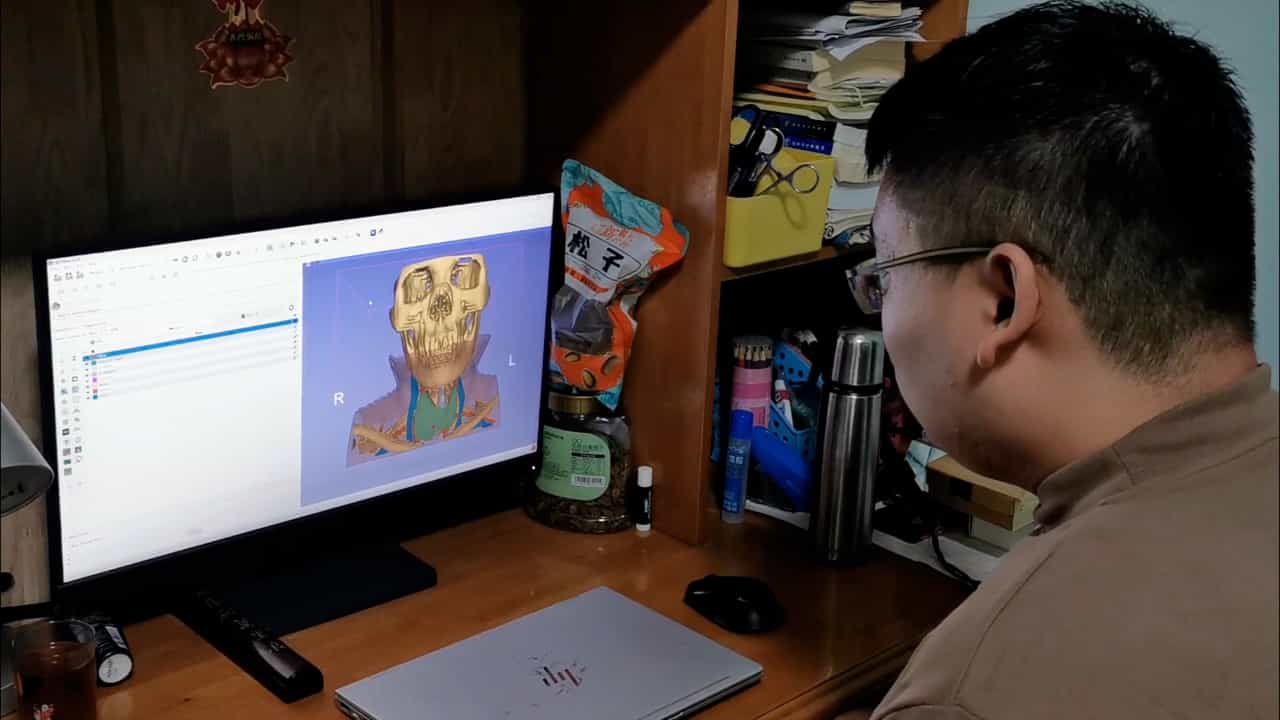

Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
Management of subclinical hyperthyroidism
Silvia Santos Palacios1, Eider Pascual-Corrales, Juan Carlos Galofre
1Department of Endocrinology and Nutrition, University Clinic of Navarra, University of Navarra, Pamplona, Spain.

The ideal approach for adequate management of subclinical hyperthyroidism (low levels of thyroid-stimulating hormone [TSH] and normal thyroid hormone level) is a matter of intense debate among endocrinologists. The prevalence of low serum TSH levels ranges between 0.5% in children and 15% in the elderly population. Mild subclinical hyperthyroidism is more common than severe subclinical hyperthyroidism. Transient suppression of TSH secretion may occur because of several reasons; thus, corroboration of results from different assessments is essential in such cases. During differential diagnosis of hyperthyroidism, pituitary or hypothalamic disease, euthyroid sick syndrome, and drug-mediated suppression of TSH must be ruled out. A low plasma TSH value is also typically seen in the first trimester of gestation. Factitial or iatrogenic TSH inhibition caused by excessive intake of levothyroxine should be excluded by checking the patient's medication history. If these nonthyroidal causes are ruled out during differential diagnosis, either transient or long-term endogenous thyroid hormone excess, usually caused by Graves' disease or nodular goiter, should be considered as the cause of low circulating TSH levels. We recommend the following 6-step process for the assessment and treatment of this common hormonal disorder: 1) confirmation, 2) evaluation of severity, 3) investigation of the cause, 4) assessment of potential complications, 5) evaluation of the necessity of treatment, and 6) if necessary, selection of the most appropriate treatment. In conclusion, management of subclinical hyperthyroidism merits careful monitoring through regular assessment of thyroid function. Treatment is mandatory in older patients (> 65 years) or in presence of comorbidities (such as osteoporosis and atrial fibrillation).
The ideal approach for adequate management of subclinical hyperthyroidism (low levels of thyroid-stimulating hormone [TSH] and normal thyroid hormone level) is a matter of intense debate among endocrinologists. The prevalence of low serum TSH levels ranges between 0.5% in children and 15% in the elderly population. Mild subclinical hyperthyroidism is more common than severe subclinical hyperthyroidism. Transient suppression of TSH secretion may occur because of several reasons; thus, corroboration of results from different assessments is essential in such cases. During differential diagnosis of hyperthyroidism, pituitary or hypothalamic disease, euthyroid sick syndrome, and drug-mediated suppression of TSH must be ruled out. A low plasma TSH value is also typically seen in the first trimester of gestation. Factitial or iatrogenic TSH inhibition caused by excessive intake of levothyroxine should be excluded by checking the patient's medication history. If these nonthyroidal causes are ruled out during differential diagnosis, either transient or long-term endogenous thyroid hormone excess, usually caused by Graves' disease or nodular goiter, should be considered as the cause of low circulating TSH levels. We recommend the following 6-step process for the assessment and treatment of this common hormonal disorder: 1) confirmation, 2) evaluation of severity, 3) investigation of the cause, 4) assessment of potential complications, 5) evaluation of the necessity of treatment, and 6) if necessary, selection of the most appropriate treatment. In conclusion, management of subclinical hyperthyroidism merits careful monitoring through regular assessment of thyroid function. Treatment is mandatory in older patients (> 65 years) or in presence of comorbidities (such as osteoporosis and atrial fibrillation).
Related Concept Videos
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...