Related Experiment Video
Updated: May 9, 2026

Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Pleural pressure and optimal positive end-expiratory pressure based on esophageal pressure versus chest wall
Gaurav Gulati1, Aileen Novero, Stephen H Loring
1Department of Anesthesia, Critical Care and Pain Medicine, Beth Israel Deaconess Medical Center and Harvard Medical School, Boston, MA, USA.

Objectives:
1) To compare two published methods for estimating pleural pressure, one based on directly measured esophageal pressure and the other based on chest wall elastance. 2) To evaluate the agreement between two published positive end-expiratory pressure optimization strategies based on these methods, one targeting an end-expiratory esophageal pressure-based transpulmonary pressure of 0 cm H2O and the other targeting an end-inspiratory elastance-based transpulmonary pressure of 26 cm H2O.
Design:
Retrospective study using clinical data.
Setting:
Medical and surgical ICUs.
Patients:
Sixty-four patients mechanically ventilated for acute respiratory failure with esophageal balloons placed for clinical management.
Methods:
Esophageal pressure and chest wall elastance-based methods for estimating pleural pressure and setting positive end-expiratory pressure were retrospectively applied to each of the 64 patients. In patients who were ventilated at two positive end-expiratory pressure levels, chest wall and respiratory system elastances were calculated at each positive end-expiratory pressure level.
Measurements And Main Results:
The pleural pressure estimates using both methods were discordant and differed by as much as 10 cm H2O for a given patient. The two positive end-expiratory pressure optimization strategies recommended positive end-expiratory pressure changes in opposite directions in 33% of patients. The ideal positive end-expiratory pressure levels recommended by the two methods for each patient were discordant and uncorrelated (R = 0.05). Chest wall and respiratory system elastances grew with increases in positive end-expiratory pressure in patients with positive end-expiratory esophageal pressure-based transpulmonary pressures (p < 0.05).
Conclusions:
Esophageal pressure and chest wall elastance-based methods for estimating pleural pressure do not yield similar results. The strategies of targeting an end-expiratory esophageal pressure-based transpulmonary pressure of 0 cm H2O and targeting an end-inspiratory elastance-based transpulmonary pressure of 26 cm H2O cannot be considered interchangeable. Finally, chest wall and respiratory system elastances may vary unpredictably with changes in positive end-expiratory pressure.
Related Concept Videos
 01:24
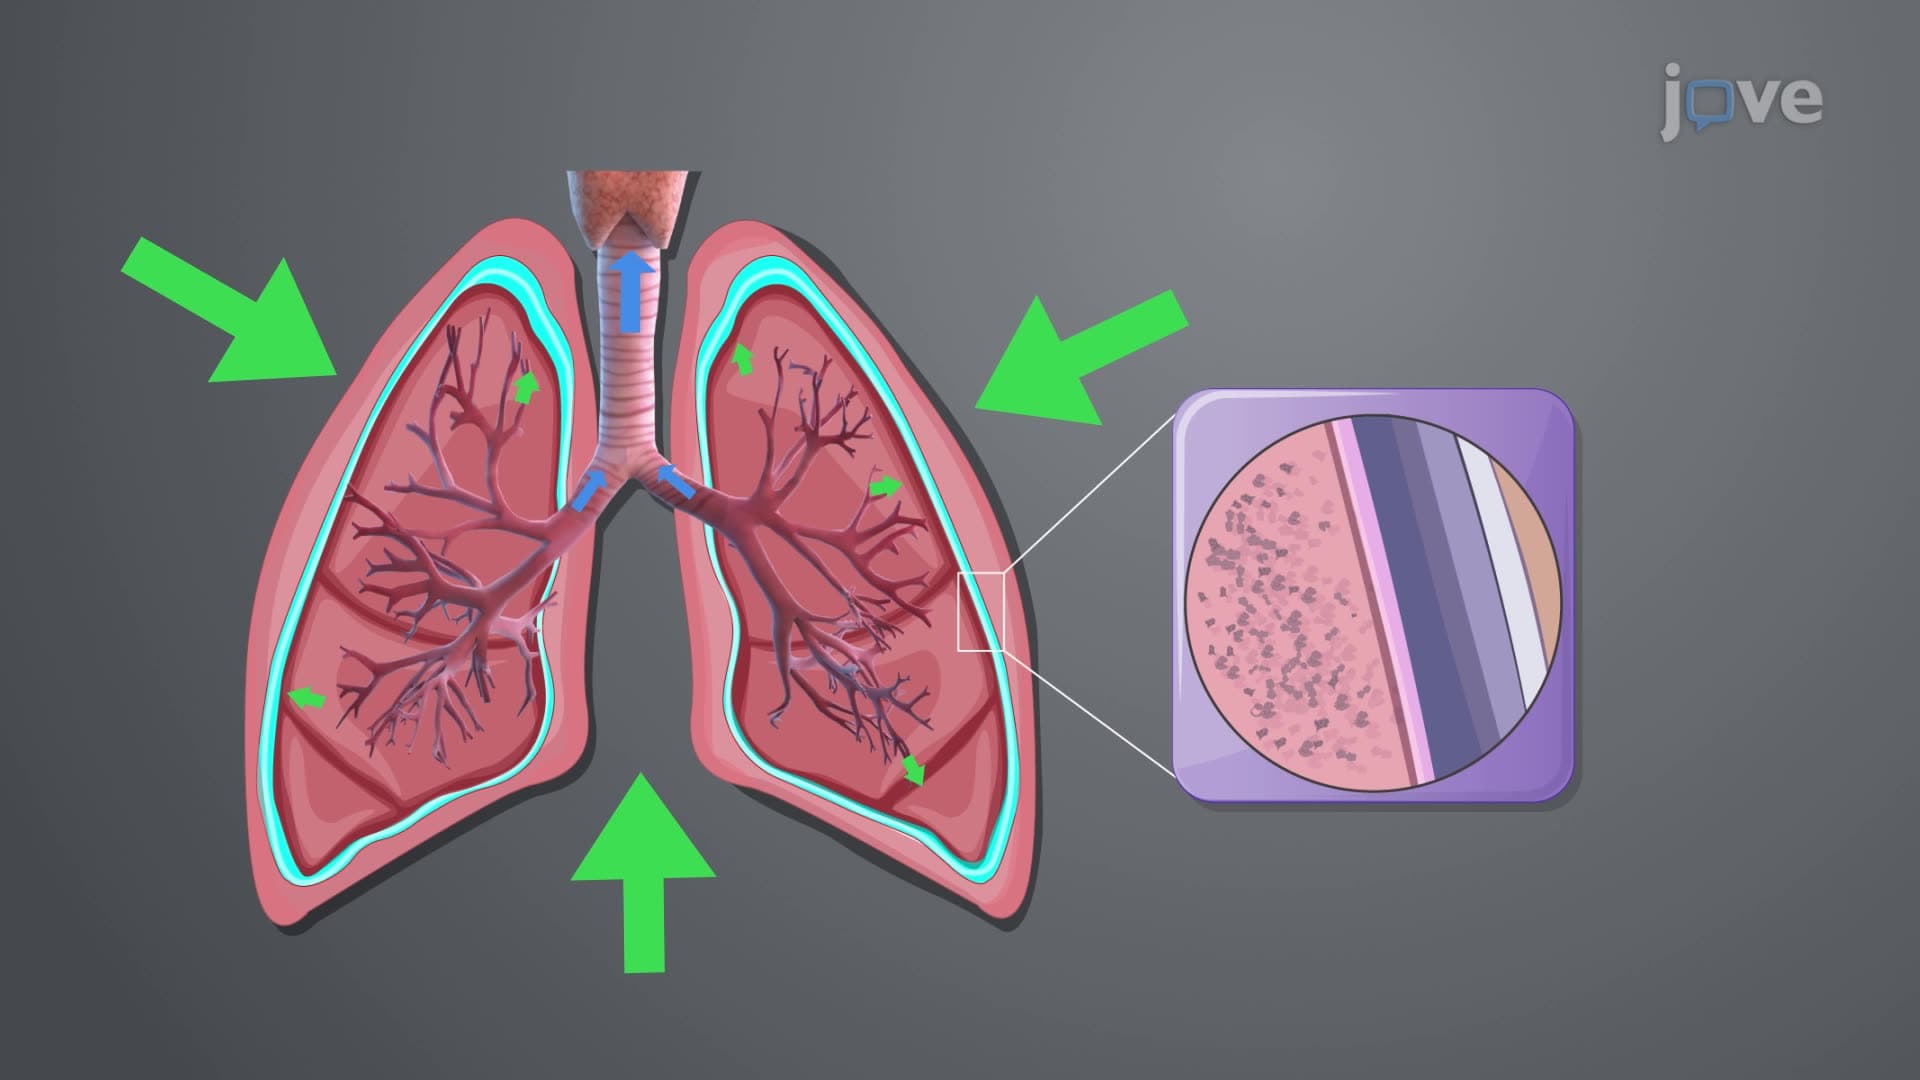
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:08
Pneumothorax II: Pathophysiology
 01:24
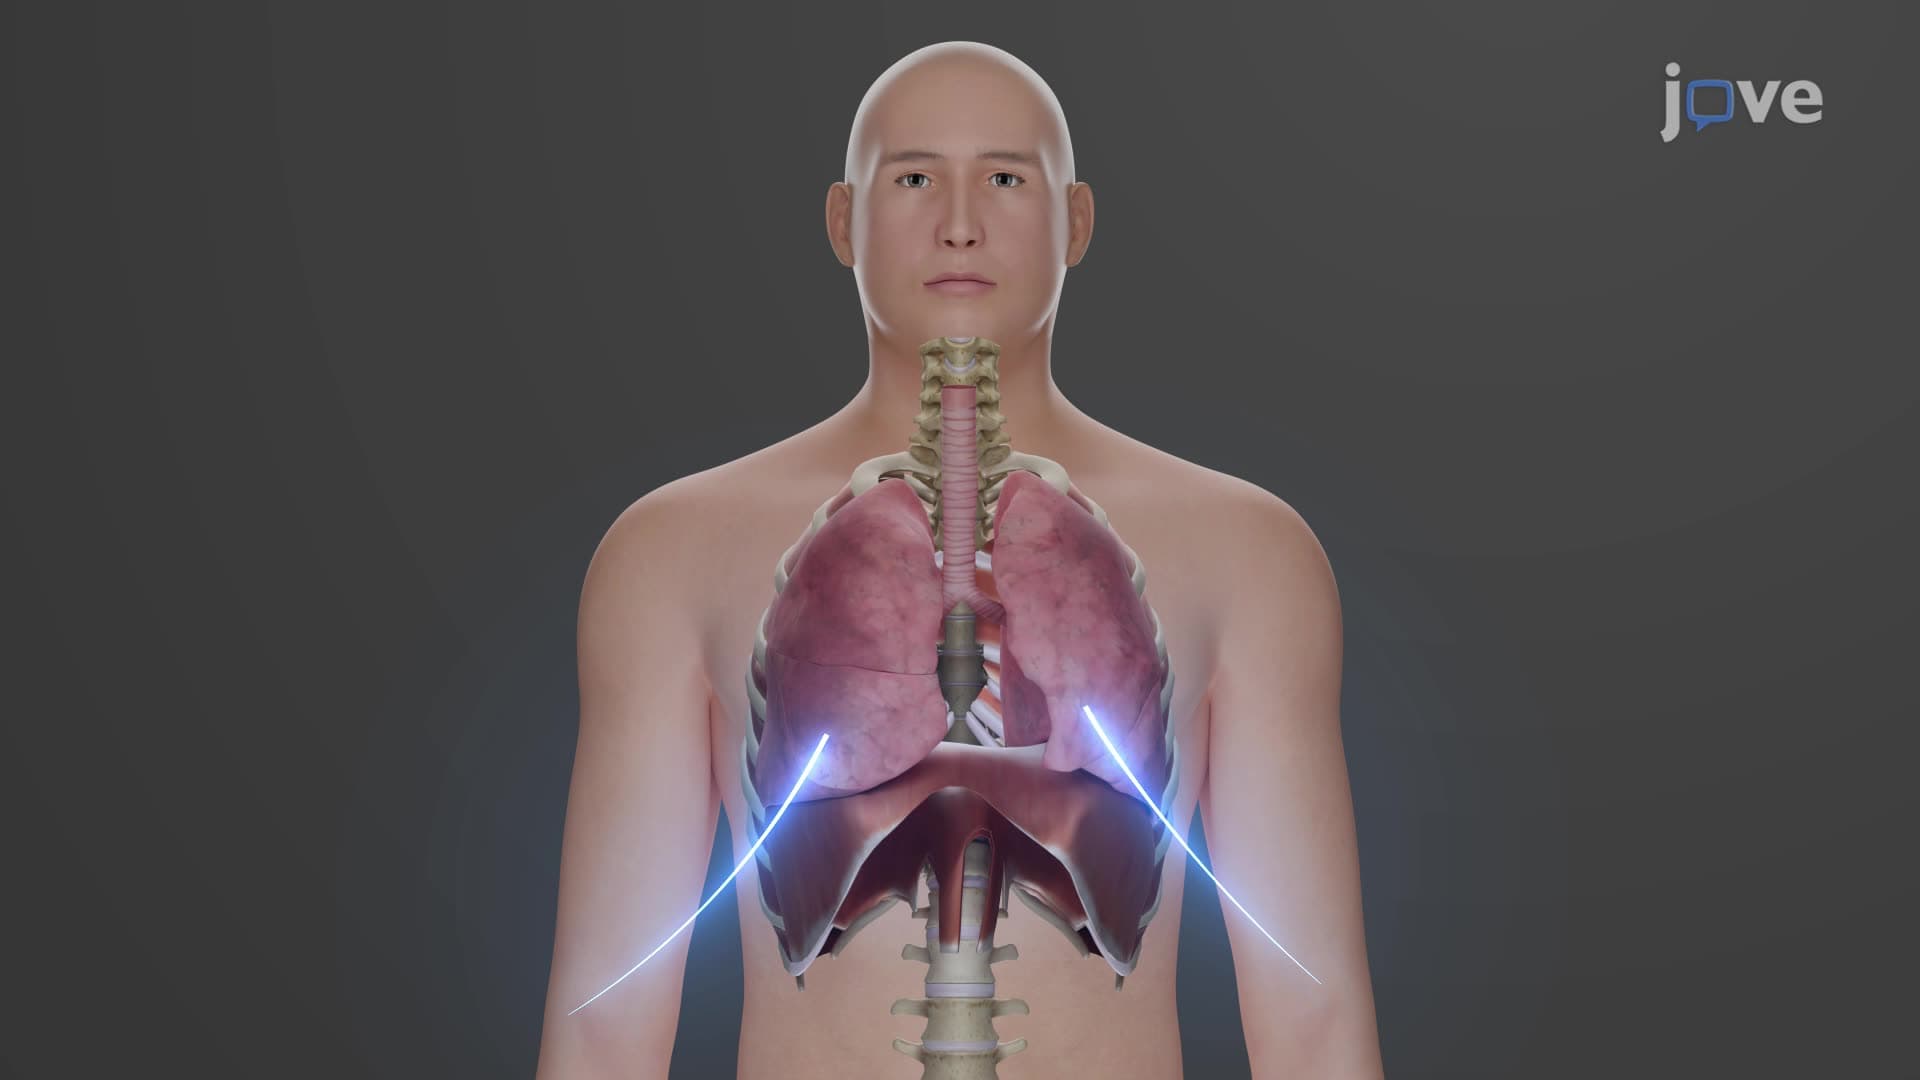
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:10
Atelectasis II: Pathophysiology