Implementation of an evidence-based extubation readiness bundle in 499 brain-injured patients. a before-after evaluation of a quality improvement project
Related Experiment Video
Updated: May 9, 2026

Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Antoine Roquilly1, Raphaël Cinotti, Samir Jaber
11 Intensive Care Unit, Anesthesia and Critical Care Department, Hôtel Dieu-HME, University Hospital of Nantes, Nantes, France.

Rationale:
Mechanical ventilation is associated with morbidity in patients with brain injury.
Objectives:
This study aims to assess the effectiveness of an extubation readiness bundle to decrease ventilator time in patients with brain injury.
Methods:
Before-after design in two intensive care units (ICUs) in one university hospital. Brain-injured patients ventilated more than 24 hours were evaluated during two phases (a 3-yr control phase followed by a 22-mo intervention phase). Bundle components were protective ventilation, early enteral nutrition, standardization of antibiotherapy for hospital-acquired pneumonia, and systematic approach to extubation. The primary endpoint was the duration of mechanical ventilation.
Measurements And Main Results:
A total of 299 and 200 patients, respectively, were analyzed in the control and the intervention phases of this before-after study. The intervention phase was associated with lower tidal volume (P < 0.01), higher positive end-expiratory pressure (P < 0.01), and higher enteral intake in the first 7 days (P = 0.01). The duration of mechanical ventilation was 14.9 ± 11.7 days in the control phase and 12.6 ± 10.3 days in the intervention phase (P = 0.02). The hazard ratio for extubation was 1.28 (95% confidence interval [CI], 1.04-1.57; P = 0.02) in the intervention phase. Adjusted hazard ratio was 1.40 (95% CI, 1.12-1.76; P < 0.01) in multivariate analysis and 1.34 (95% CI, 1.03-1.74; P = 0.02) in propensity score-adjusted analysis. ICU-free days at Day 90 increased from 50 ± 33 in the control phase to 57 ± 29 in the intervention phase (P < 0.01). Mortality at Day 90 was 28.4% in the control phase and 23.5% in the intervention phase (P = 0.22).
Conclusions:
The implementation of an evidence-based extubation readiness bundle was associated with a reduction in the duration of ventilation in patients with brain injury.


Related Concept Videos
 01:17
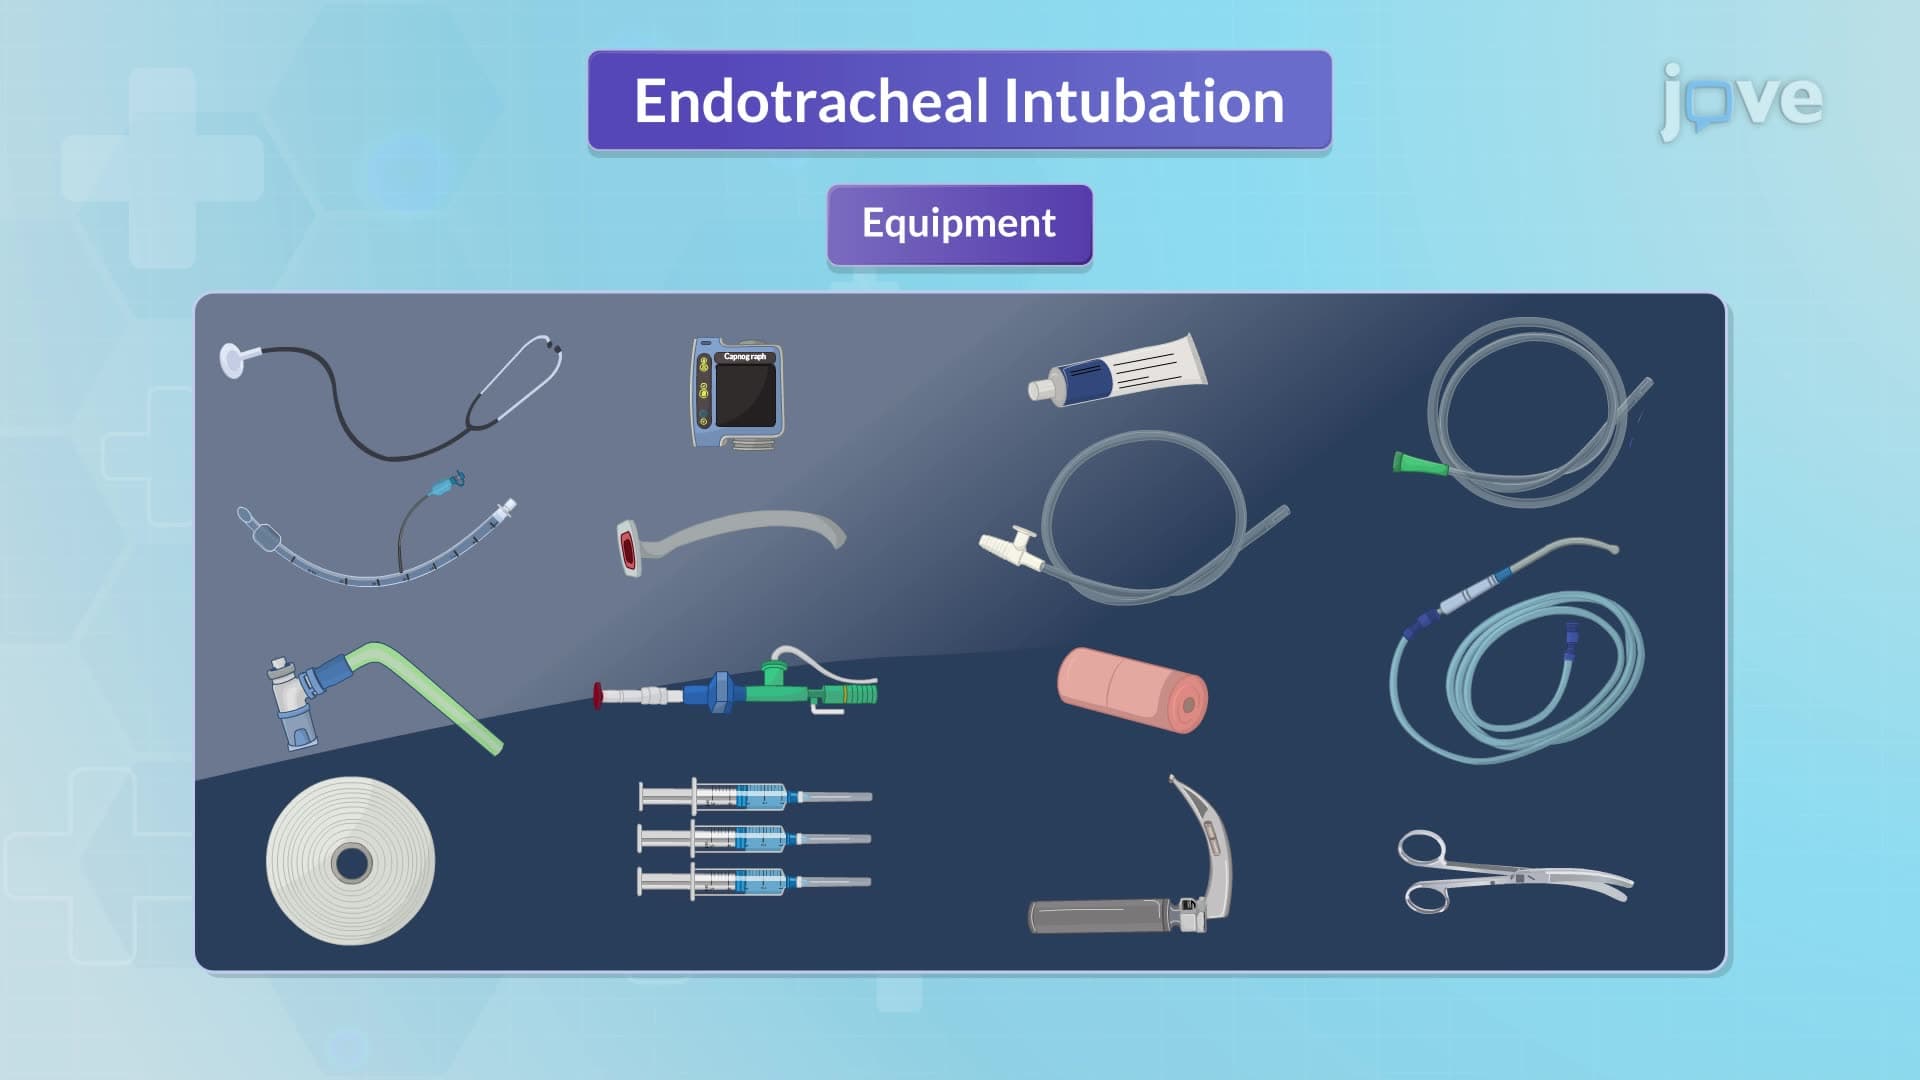
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
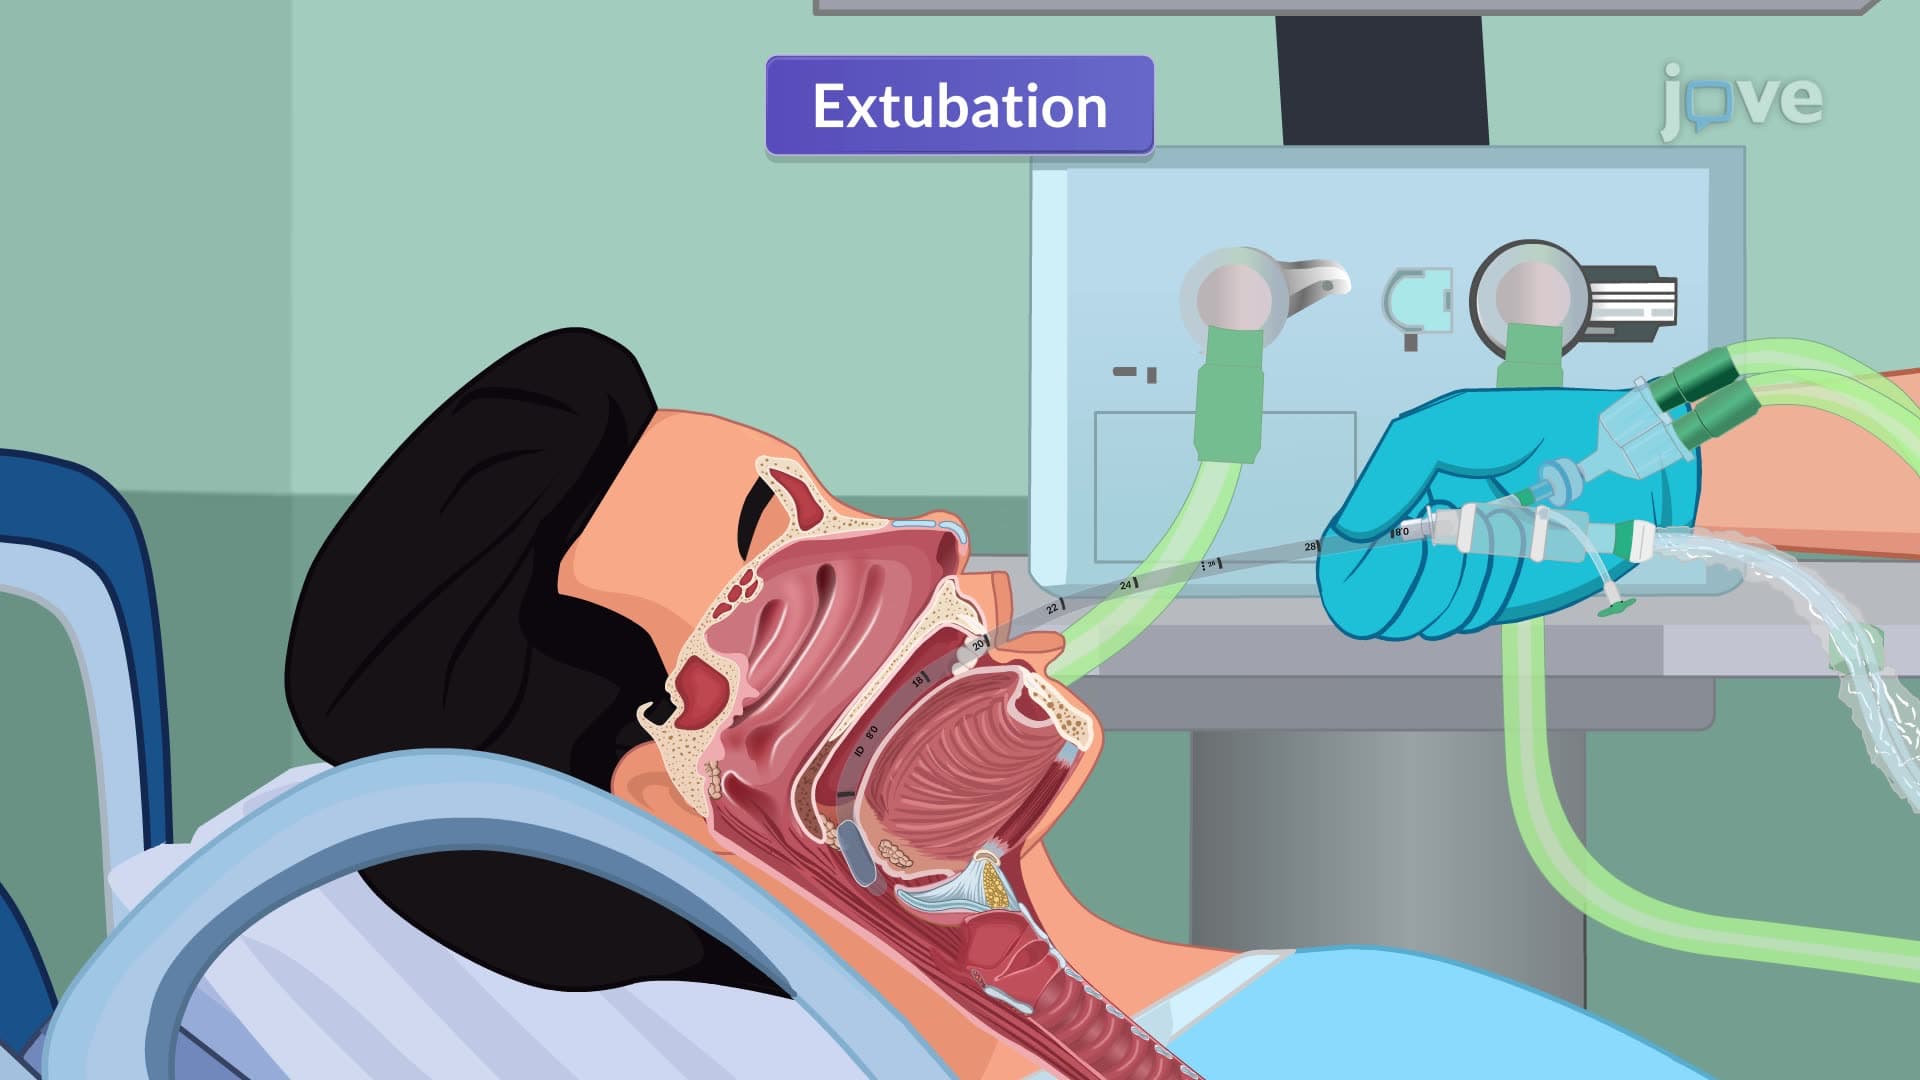
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:15
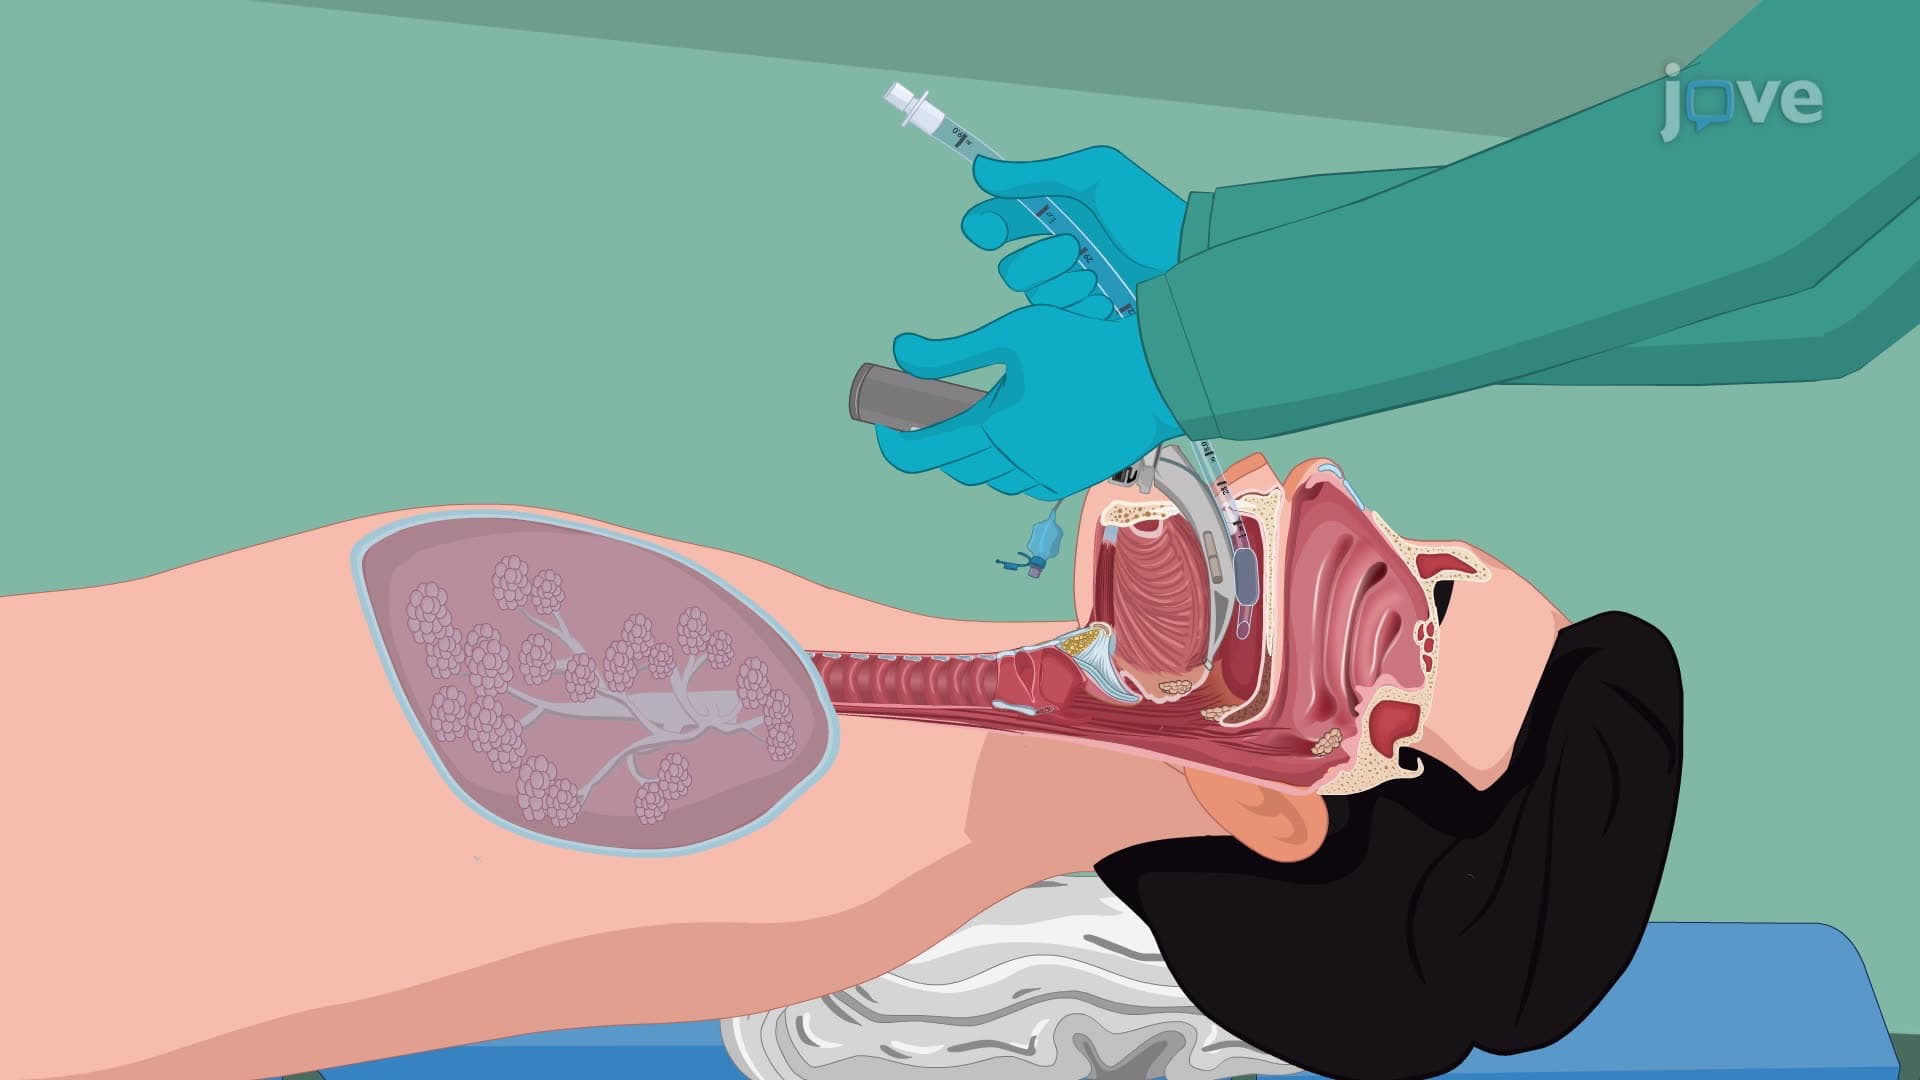
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...