Surgical treatment of hypermotor seizures originating from the temporal lobe
Related Experiment Video
Updated: May 9, 2026
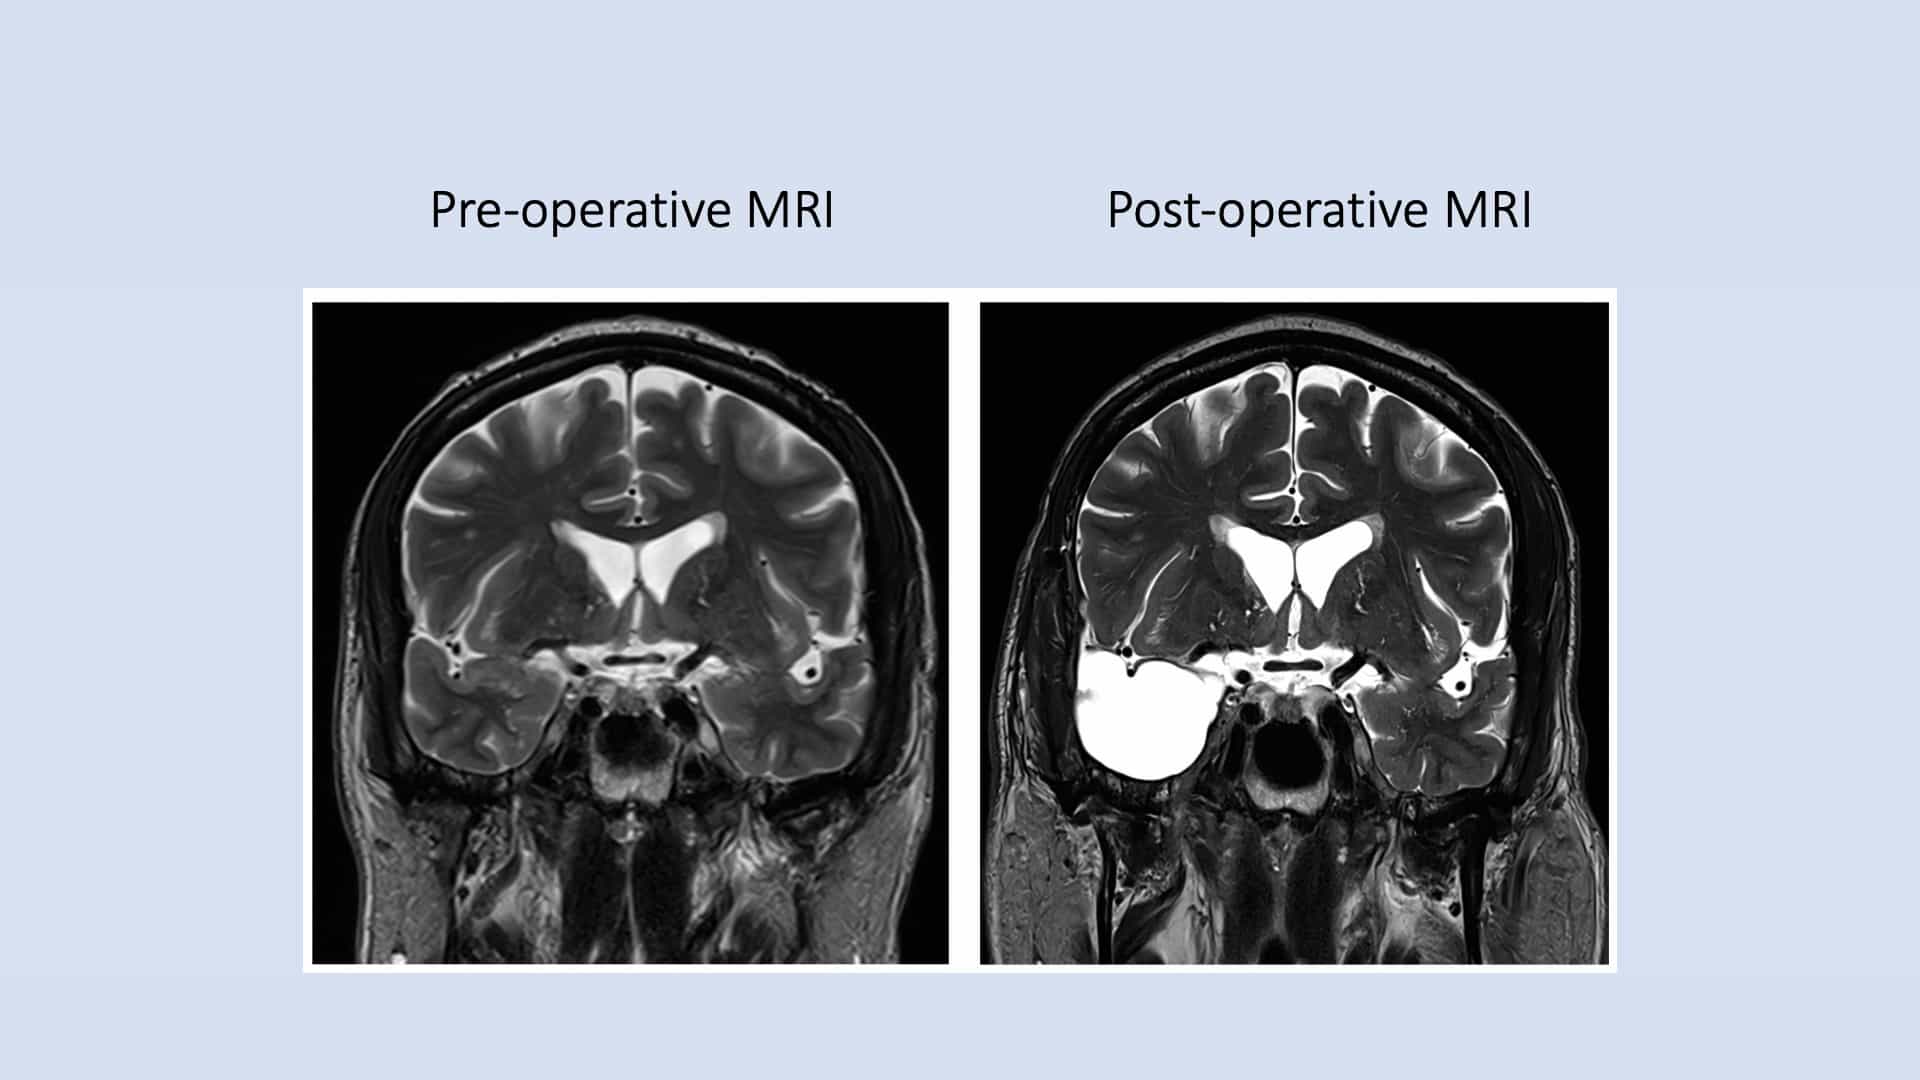
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Tao Yu1, Guojun Zhang, Yuping Wang
1Beijing Institute of Functional Neurosurgery, Xuanwu Hospital, Capital Medical University, China.

Purpose:
To describe the characteristics of electroclinical manifestations in patients with hypermotor seizures (HMSs) originating from the temporal lobe.
Methods:
We retrospectively reviewed the data of patients who underwent surgical treatments for seizure to identify patients with HMSs of temporal origin. We systematically reviewed patient seizure histories, imaging reports, video-EEG monitoring data, operative records and pathological findings.
Results:
Eight of the 9 patients reported auras. The ictal behavior included marked agitation in 5 patients and mild agitation in 4 patients. All of the 9 patients exhibited stiffness or dystonia of the upper limb or contralateral limbs during ictus. Seven of the 9 patients completed intracranial recording and at least 3 seizures were recorded for each patient. The intracranial recordings showed ictal activity originating from mesial temporal lobe in 6 patients and the lateral temporal lobe in 1 patient. The time interval of ictal propagation from the temporal to frontal lobe was 15.0 ± 8.3 s. While the time interval from EEG origination to the beginning of hypermotor behavior was 21.0 ± 8.1 s. Brain MRIs revealed hippocampal sclerosis in 3, neoplastic lesion in 1, and normal images in the remaining 5 patients. Patients were followed for 1-5 years after the anterior temporal lobectomy; 7 patients remained seizure-free throughout follow-up.
Conclusion:
Some HMSs can originate from the temporal lobe. In carefully selected patients, surgical resection may lead to good outcomes.