Related Experiment Video
Updated: May 8, 2026

Contractility Measurements on Isolated Papillary Muscles for the Investigation of Cardiac Inotropy in Mice
Published on: September 17, 2015
Adenosine prevents isoprenaline-induced cardiac contractile and electrophysiological dysfunction
Yangzhen Shao1, Björn Redfors, Lillemor Mattson-Hultén
1Department of Molecular and Clinical Medicine, Sahlgrenska Academy at University of Gothenburg, Gothenburg, Sweden.

Insights
Adenosine prevents cardiac dysfunction and reduces lipid accumulation in a mouse model of stress-induced cardiomyopathy. This study highlights adenosine
Area of Science:
- Cardiology
- Pharmacology
- Biochemistry
Background:
- Excessive catecholamines contribute to cardiac dysfunction in various diseases.
- Stress-induced cardiomyopathy, linked to high morbidity and mortality, involves catecholamine excess.
- Previous research showed isoprenaline induces reversible left ventricular dysfunction in mice.
Purpose of the Study:
- To investigate the potential of adenosine in preventing cardiac dysfunction in a mouse model of stress-induced cardiomyopathy.
- To evaluate the effects of adenosine on myocardial fibrosis and intracellular lipid accumulation.
- To assess adenosine's impact on electrophysiological parameters in cardiomyocytes.
Main Methods:
- Male C57BL/6 mice were injected with isoprenaline and randomized to adenosine or saline treatment.
- Cardiac function was assessed using echocardiography at multiple time points post-injection.
- Myocardial fibrosis and intracellular lipid accumulation were quantified, along with electrophysiological studies in HL1 cells.
Main Results:
- Adenosine treatment significantly improved global and regional cardiac function compared to saline.
- Adenosine-treated mice showed reduced intracellular lipid accumulation and no significant myocardial fibrosis.
- Adenosine-treated HL1 cells maintained electrophysiological function and exhibited less lipid accumulation.
Conclusions:
- Adenosine effectively attenuates isoprenaline-induced cardiac dysfunction in a mouse model.
- Adenosine demonstrates protective effects against myocardial fibrosis and lipid accumulation.
- Adenosine shows promise as a therapeutic agent for stress-induced cardiomyopathy.
Abstract:
Excessive levels of catecholamines are believed to contribute to cardiac dysfunction in a variety of disease states, including myocardial infarction and heart failure, and are particularly implicated in stress-induced cardiomyopathy, an increasingly recognized cardiomyopathy associated with significant morbidity and mortality. We have previously shown that a high dose of isoprenaline induces reversible regional dysfunction of the left ventricle in mice. We now hypothesize that adenosine can prevent cardiac dysfunction in this mouse model of stress-induced cardiomyopathy. Hundred male C57BL/6 mice were injected with 400mg/kg isoprenaline and then randomized to either 400mg/kg adenosine or saline. Cardiac function was evaluated by echocardiography at baseline and 2, 24, 48, 72, 96 and 120 min post isoprenaline. Myocardial fibrosis was quantified after 10 days. Intracellular lipid accumulation was quantified after 2 and 24h. Electrophysiological parameters and degree of lipid accumulation were evaluated in cultured HL1 cardiomyocytes. Two hours post isoprenaline treatment, echocardiographic parameters of global and posterior wall regional function were significantly better in adenosine-treated mice (P<0.05). This difference persisted at 24h, but saline-treated mice gradually recovered over the next 96 h. Intracellular lipid accumulation was also significantly lower in adenosine mice. We found no sign of fibrosis in the adenosine mice, whereas the extent of fibrosis in isoprenaline mice was 1.3% (P<0.05). Furthermore, adenosine-treated HL1 cells showed preserved electrophysiological function and displayed less severe intracellular lipid accumulation in response to isoprenaline. In conclusion, adenosine attenuates isoprenaline-induced cardiac dysfunction in mice and cells.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
Heart Failure Drugs: Inotropic Agents
 01:26
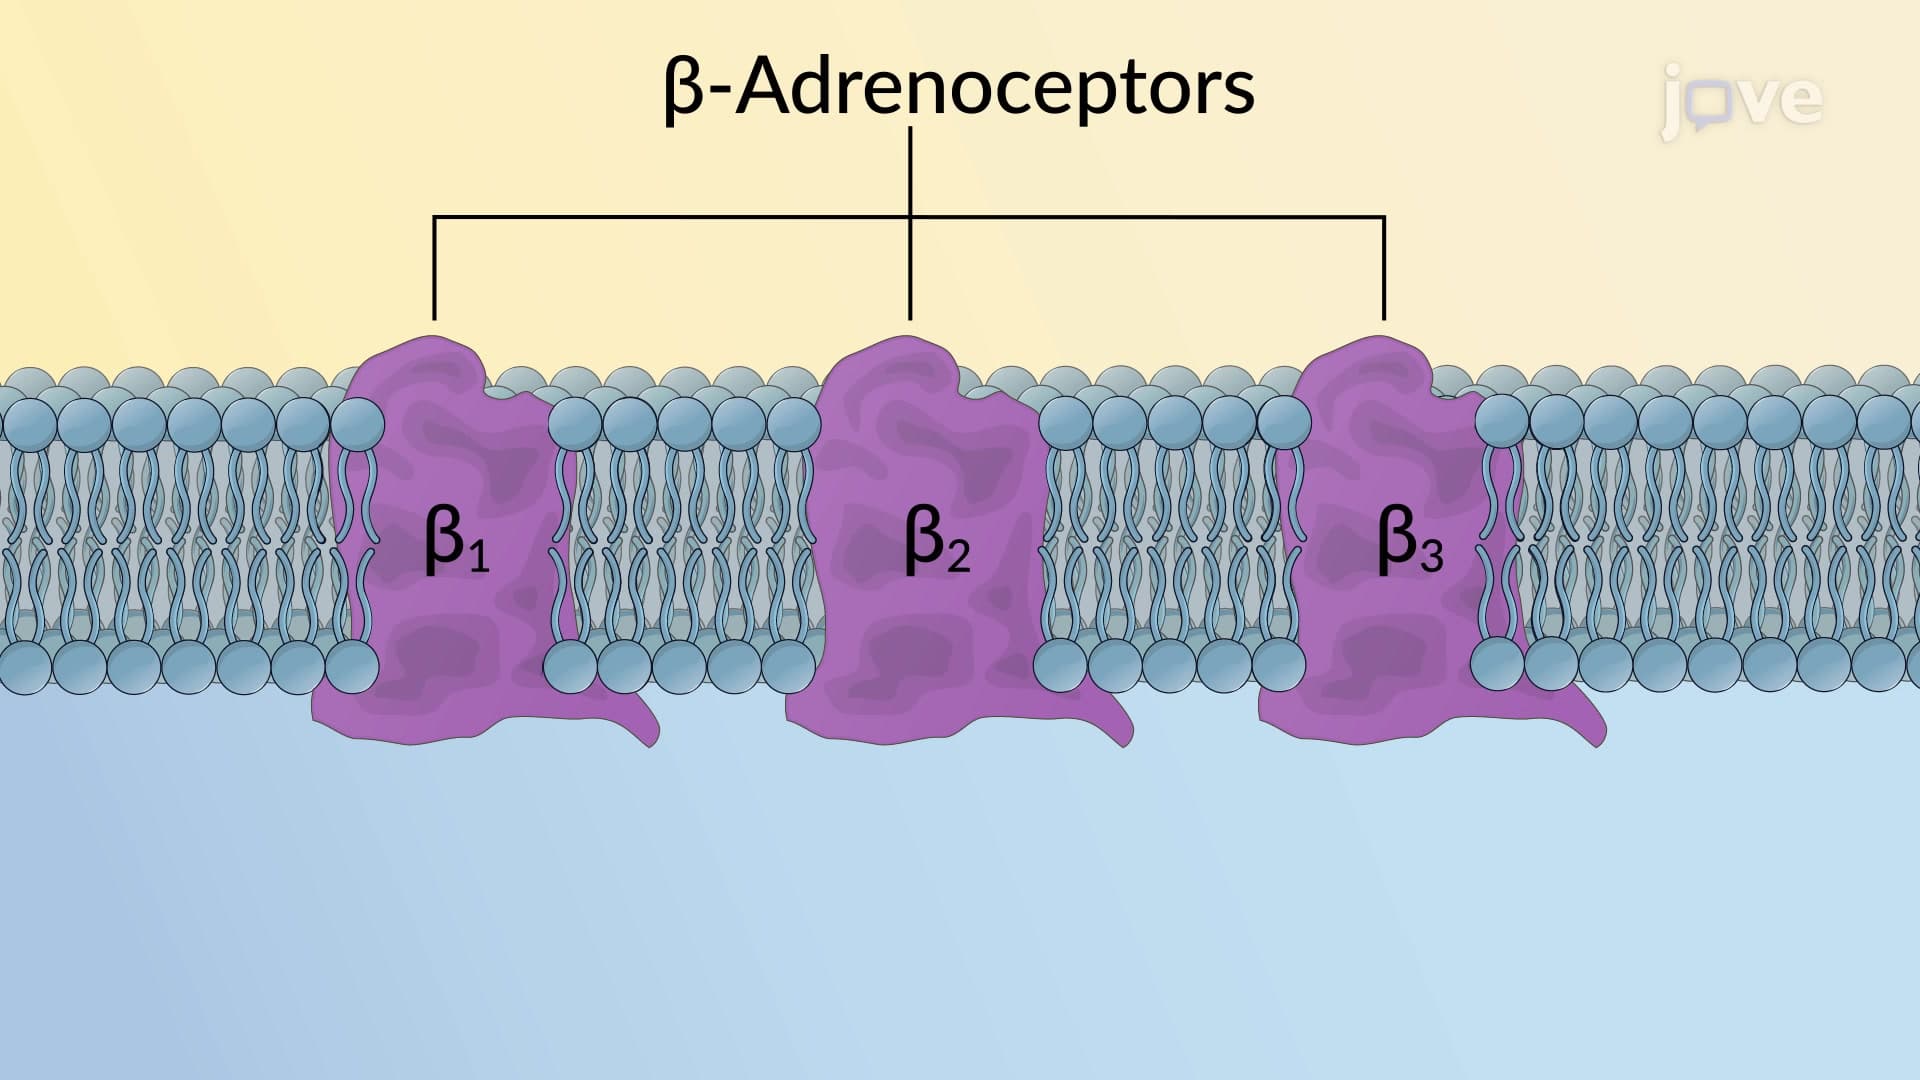
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:31
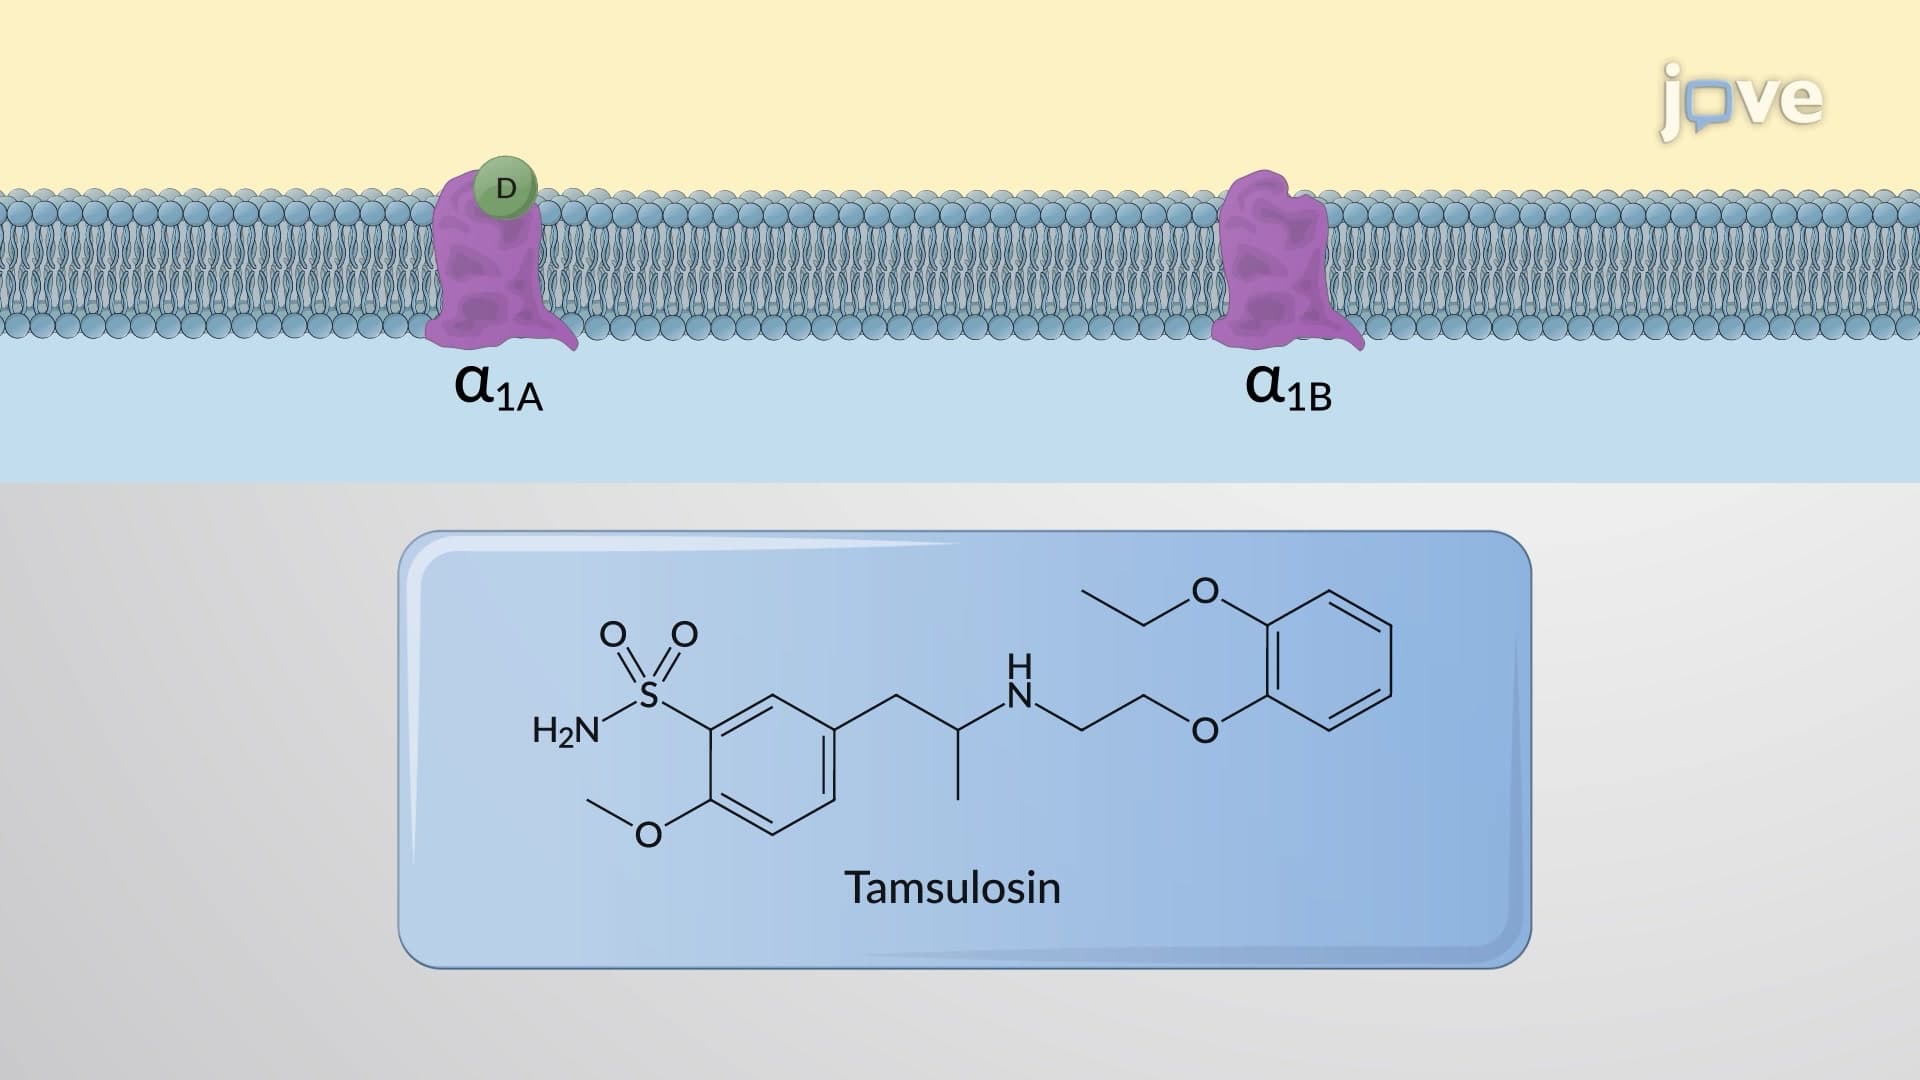
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...