Related Experiment Video
Updated: May 8, 2026
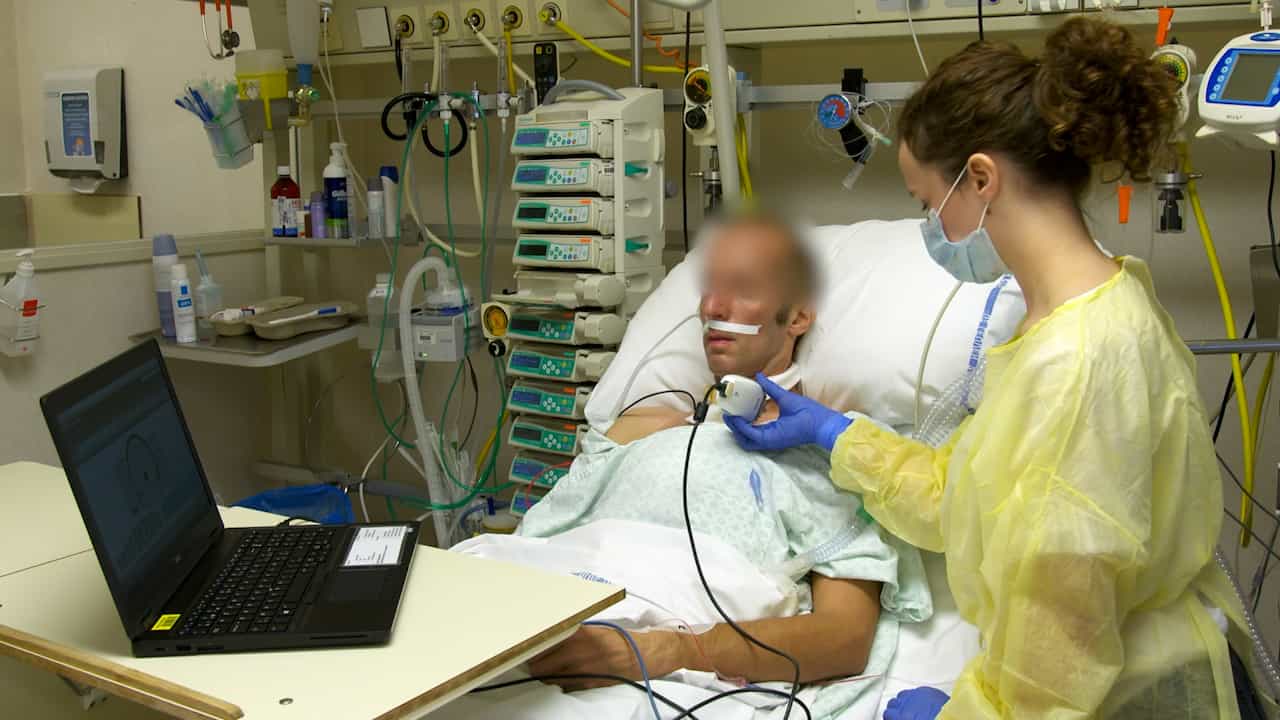

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Neuro-ventilatory efficiency during weaning from mechanical ventilation using neurally adjusted ventilatory assist
H Rozé1, B Repusseau, V Perrier
1CHU de Bordeaux, Service d'Anesthésie-Réanimation II, F-33600 Pessac, France.

Background:
Neuro-ventilatory efficiency (NVE), defined as the tidal volume to electrical diaphragm-activity ratio (VT/EAdi) at the beginning and end of the weaning process after acute hypoxaemic respiratory failure, may provide valuable information about patient recovery.
Methods:
This observational study included 12 patients breathing with neurally adjusted ventilatory assist (NAVA). When a spontaneous breathing trial (SBT) with pressure support of 7 cm H2O and PEEP was unsuccessful, NAVA was used and the level was adjusted to obtain an EAdi of ∼60% of maximal EAdi during SBT. VT and EAdi were recorded continuously. We compared changes in NVE between NAVA and SBT at the first failed and first successful SBT.
Results:
When patients were switched from NAVA to SBT, NVE was significantly reduced during both unsuccessful and successful SBT (-56 and -38%, respectively); however, this reduction was significantly lower when SBT was successful (P=0.01). Between the first and last day of weaning, we observed that NVE decreased with NAVA [40.6 (27.7-89.5) vs 28.8 (18.6-46.7); P=0.002] with a significant decrease in NAVA level, whereas it remained unchanged during SBT [15.4 (10.7-39.1) vs 19.5 (11.6-29.6); P=0.50] with significant increases in both EAdi and VT and no difference in respiratory rhythm.
Conclusions:
These results suggest that in patients after respiratory failure and prolonged mechanical ventilation, changes in VT and NVE, between SBTs are indicative of patient recovery. Larger clinical trials are needed to clarify whether changes in NVE reliably predict weaning in patients ventilated with NAVA.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: